Related Experiment Video
Updated: Dec 8, 2025


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Effect of sacubitril/valsartan on renal function: a systematic review and meta-analysis of randomized controlled
Francesco Spannella1,2, Federico Giulietti1,2, Andrea Filipponi1,2
1Internal Medicine and Geriatrics, IRCCS INRCA, Via della Montagnola 81, Ancona, Italy.

Insights
Sacubitril/valsartan reduces the risk of renal dysfunction compared to renin-angiotensin system inhibitors in heart failure patients. This benefit is more pronounced in older individuals and those with preserved ejection fraction, but requires further study in non-heart failure populations.
Area of Science:
- Cardiology
- Nephrology
- Pharmacology
Background:
- Worsening renal function is common in cardiovascular disease, particularly heart failure (HF).
- Sacubitril/valsartan shows promise in preserving renal function and slowing chronic kidney disease (CKD) progression in HF patients compared to traditional renin-angiotensin system (RAS) inhibitors.
- The renal benefits of sacubitril/valsartan beyond HF patients remain under investigation.
Purpose of the Study:
- To systematically review and meta-analyze randomized controlled trials (RCTs).
- To assess the renal outcomes of sacubitril/valsartan compared to RAS inhibitors across diverse patient populations, including those with and without HF.
- To evaluate the consistency of sacubitril/valsartan's effect size on renal outcomes.
Main Methods:
- Systematic literature search of Medline, Scopus, and Thomson Reuters Web of Science databases up to June 2020.
- Inclusion of RCTs comparing sacubitril/valsartan with RAS inhibitors, reporting renal function data.
- Random-effects models used to calculate pooled odds ratios (OR) and confidence intervals (CI) for renal outcomes.
Main Results:
- Sacubitril/valsartan significantly lowered the risk of renal dysfunction compared to RAS inhibitors (pooled OR = 0.70; 95% CI 0.57-0.85).
- A stronger protective effect was observed in older patients and in HF patients with preserved ejection fraction.
- No significant renal benefit was found in studies limited to non-HF patients or those with a high risk of bias.
Conclusions:
- Sacubitril/valsartan demonstrates a role in preserving renal function, particularly in older individuals and HF patients with preserved ejection fraction.
- Current evidence primarily supports its use in HF patients.
- Further research is needed to establish the renal benefits of sacubitril/valsartan in non-HF patient populations.
Abstract:
A worsening renal function is prevalent among patients with cardiovascular disease, especially heart failure (HF). Sacubitril/valsartan appears to prevent worsening of renal function and progression of chronic kidney disease (CKD) as compared with renin-angiotensin system (RAS) inhibitors alone in HF patients. It is unclear whether these advantages are present in HF patients only, or can be extended to other categories of patients, in which this drug was studied. We performed a systematic review and meta-analysis to assess the consistency of effect size regarding renal outcome across randomized controlled trials (RCTs) that compared sacubitril/valsartan with RAS inhibitors in patients with or without HF. We searched Medline (PubMed), Scopus, and Thomson Reuters Web of Science databases until June 2020. We took into account RCTs that compared sacubitril/valsartan with a RAS inhibitor and reported data regarding renal function. We used random-effects models to obtain summary odds ratio (OR) with 95% confidence interval (CI). We extracted hazard ratios for renal outcomes, glomerular filtration rate slopes or rates of renal adverse events. Sensitivity analyses were performed by moderator analysis and random-effects meta-regression. The search revealed 10 RCTs (published between 2012 and 2019) on 16 456 subjects. Sacubitril/valsartan resulted in a lower risk of renal dysfunction as compared with RAS inhibitors alone [k = 10; pooled OR = 0.70 (95% CI 0.57-0.85); P < 0.001], with a moderate inconsistency between studies [Q(9) = 15.18; P = 0.086; I2 = 40.73%]. A stronger association was found in studies including older patients (k = 10; β = -0.047730; P = 0.020) or HF patients with preserved ejection fraction [pooled OR = 0.53 (0.41-0.68) vs. 0.76 (0.57-1.01) for studies on HF patients with reduced ejection fraction; P for comparison = 0.065]. The effect size did not change with different comparators (angiotensin-converting enzyme inhibitors vs. angiotensin II type 1 receptor blockers, P = 0.279). No significant association was found when the analysis was restricted to studies on non-HF patients [k = 3; pooled OR = 0.86 (0.61-1.22); P = 0.403] and studies with high risk of bias [k = 3; pooled OR = 0.34 (0.08-1.44); P = 0.143]. Our findings support the role of sacubitril/valsartan on preservation of renal function, especially in older patients and HF patients with preserved ejection fraction. However, evidence is currently limited to HF patients, while the renal outcome of sacubitril/valsartan therapy outside the HF setting needs to be further investigated.
More Related Videos


Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:30
Heart Failure V: Medical Management
 01:06
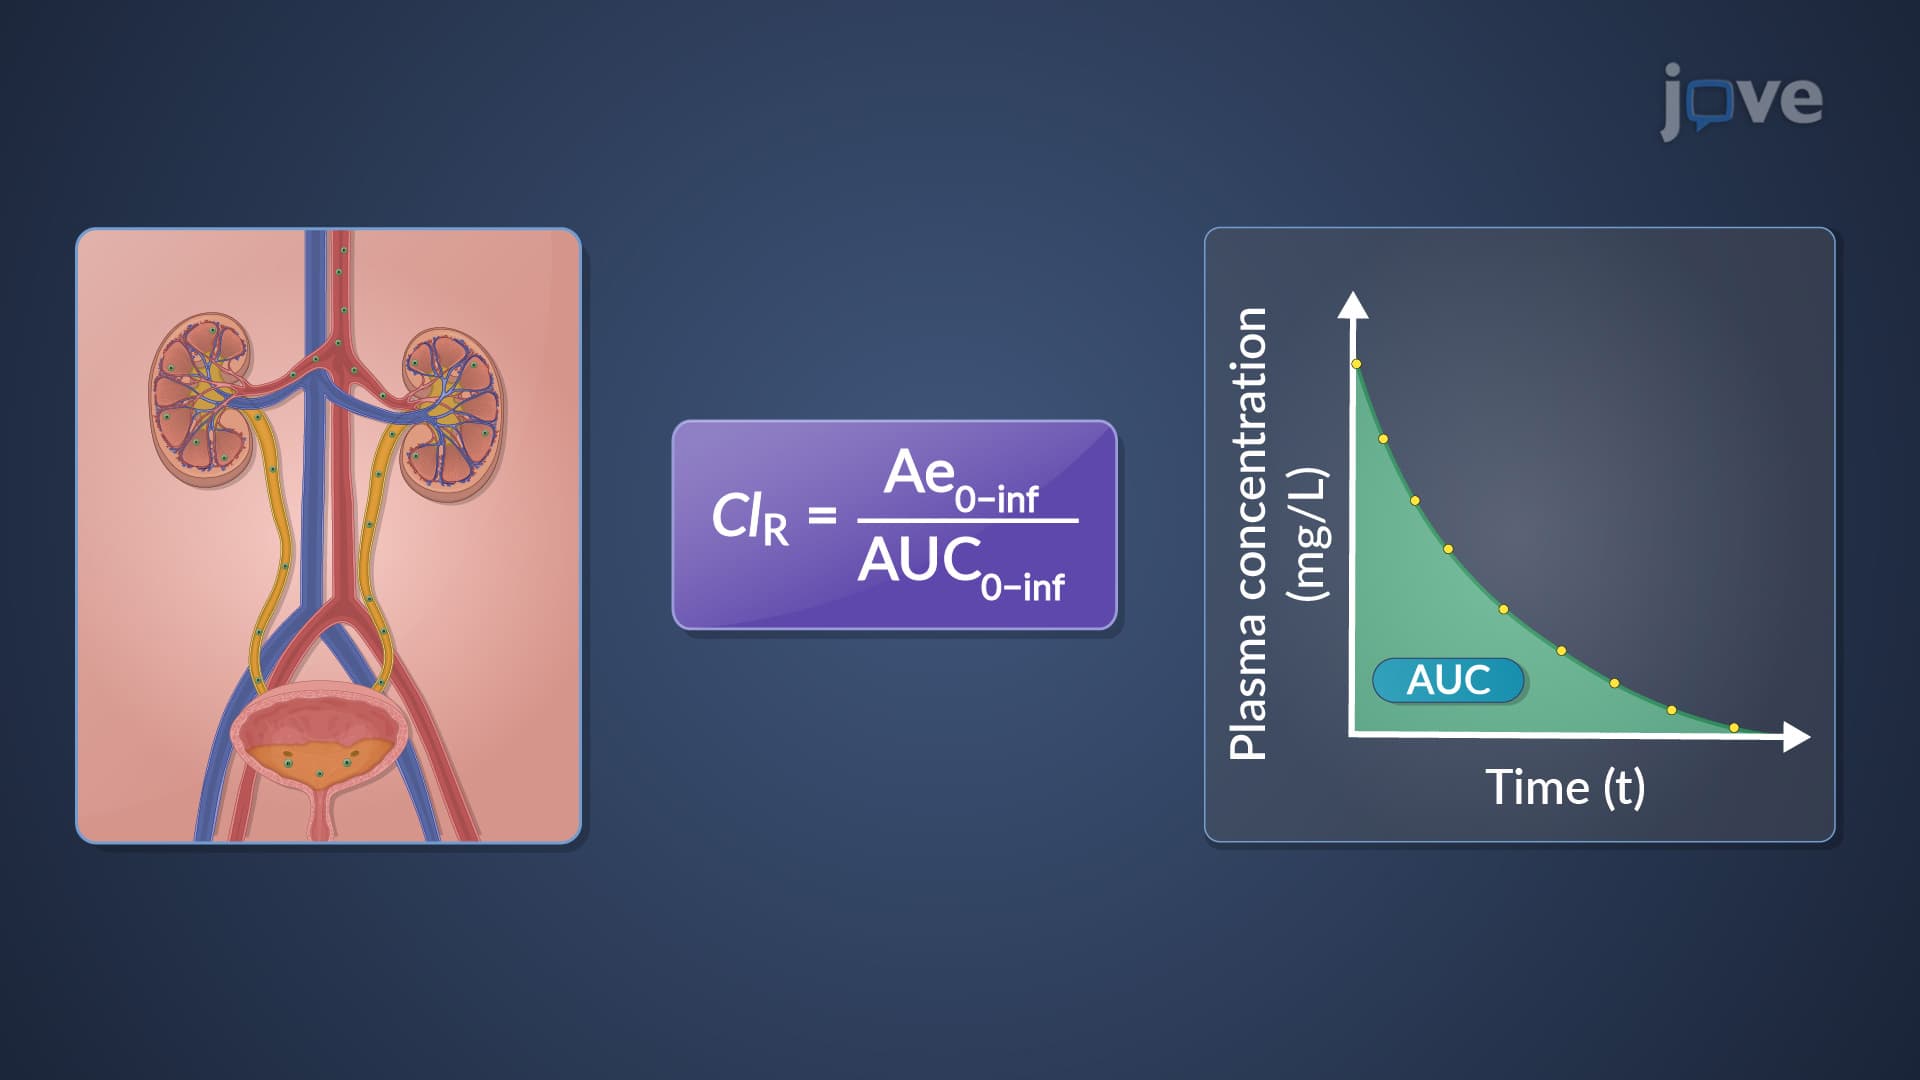
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration