Related Experiment Video
Updated: Dec 8, 2025


Skin Biopsy for Diagnosing Discoid Lupus Erythematosus
Published on: June 10, 2025
Cutaneous vasculitis in SLE
Romy Kallas1, Daniel Goldman2, Michelle A Petri3
1Division of Rheumatology, Johns Hopkins Medicine, Baltimore, Maryland, USA kallasr@mlhs.org.

Objectives:
We determined the temporal association between clinical and serological disease manifestations and development of cutaneous small vessel vasculitis in a large prospective multiethnic cohort.
Methods:
Patients with SLE diagnosed according to the Systemic Lupus International Collaborating Clinics (SLICC) classification criteria or the revised classification criteria as defined by the American College of Rheumatology (ACR) were enrolled in the Hopkins Lupus Cohort. Cutaneous small vessel vasculitis was determined as a component of the Systemic Lupus Erythematosus Disease Activity Index. SLE-associated cutaneous small vessel vasculitis lesions were reported clinically. They presented as punctate lesions, palpable purpura, tender erythematous plaques or macules with or without necrosis. No histopathological diagnosis was pursued to confirm the diagnosis of vasculitis or to differentiate it from other causes of digital lesions in patients with SLE. Disease manifestations that preceded the first occurrence of cutaneous small vessel vasculitis lesions were analysed using Kaplan-Meier. Cox regression analysis was used to assess the relationship between baseline clinical and immunological manifestations and the development of cutaneous small vessel vasculitis. We adjusted for gender, race and age at SLE diagnosis.
Results:
A total of 2580 patients were studied: 52.4% were Caucasian and 39.4% were African-American. The mean age of the cohort was 45.5±14.5 years. The mean years of cohort follow-up was 7.9±7.6. Cutaneous small vessel vasculitis was observed in 449 (17.3%). The mean time to cutaneous vasculitis after SLE diagnosis was 4.78 years (95% CI 3.96 to 5.60). At least 159 (35%) patients had recurrences of cutaneous vasculitis lesions. Discoid rash, Raynaud's phenomenon, myositis, anaemia, Coombs' positivity, leucopenia, anti-Smith and anti-RNP (Ribonucleoprotein) were significantly associated with the development of cutaneous vasculitis. The SLICC/ACR Damage Index score was higher in patients with cutaneous vasculitis compared with those without cutaneous vasculitis.
Conclusions:
Cutaneous vasculitis is frequent (17.3%) and often recurrent (35%). African-Americans are at higher risk of developing cutaneous small vessel vasculitis than Caucasians. Clinical presentations such as myositis and haematological manifestations are predictors of cutaneous vasculitis development. The presence of cutaneous vasculitis is associated with increased organ damage.


Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:23
Skin Diseases and Disorders
Gram-positive Staphylococcus spp. and Streptococcus spp. are responsible for many of the most common skin infections. However, many...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Assessment of the Cardiovascular System II: Inspection
Head and Neck
 01:11
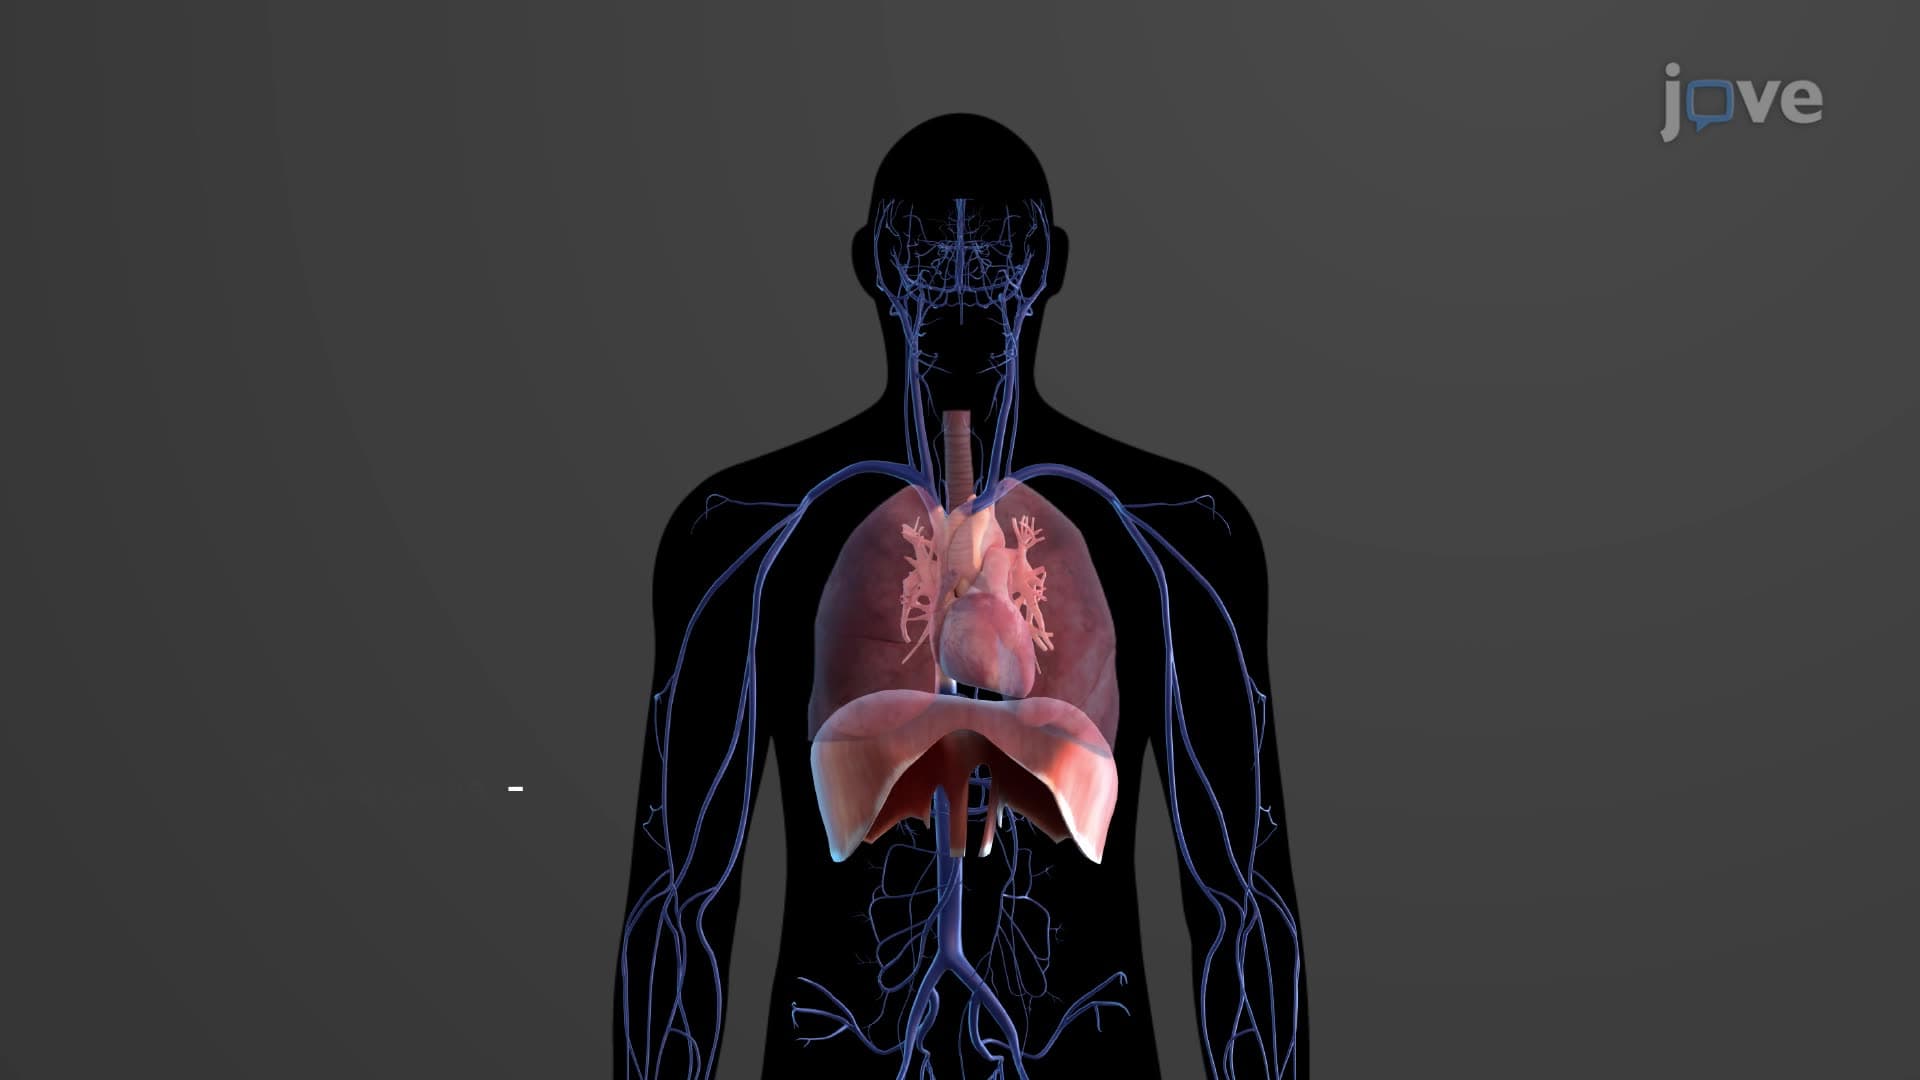
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...