Related Experiment Video
Updated: Dec 7, 2025
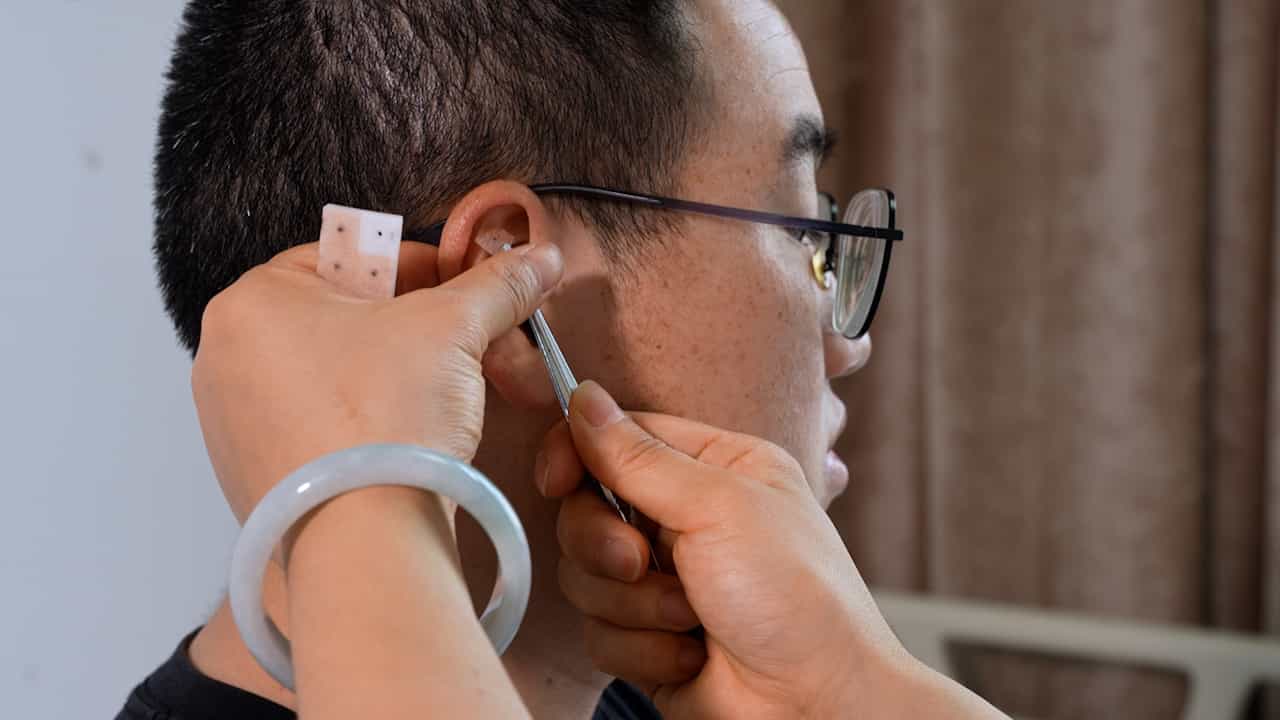

Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Evaluation of Medication Adherence and Rescue Medication Use in Non-Exacerbating Patients with COPD Receiving
Chad Moretz1, Ashley L Cole2, George Mu2
1US Value Evidence & Outcomes, GlaxoSmithKline, Research Triangle Park, Durham, NC, USA.

Background:
Adherence to inhaled maintenance therapy is critical to managing chronic obstructive pulmonary disease (COPD), while increasing rescue medication usage may indicate worsening symptoms. This study evaluated adherence and rescue medication use in patients with COPD without a history of exacerbation who initiated combination therapy with budesonide/formoterol (B/F) or umeclidinium/vilanterol (UMEC/VI).
Methods:
Retrospective observational study of commercially insured and Medicare Advantage with Part D enrollees who initiated UMEC/VI or B/F between January 1, 2014 and December 31, 2017 (earliest fill defined as index date). Eligibility criteria included age ≥40 years, 12 months continuous enrollment pre- and post-index, ≥1 pre-index COPD diagnosis, no pre-index asthma diagnosis, COPD-related exacerbations, or medication fills containing inhaled corticosteroids, long-acting β2-agonists, or long-acting muscarinic antagonists. Inverse probability of treatment weighting (IPTW) was used to balance treatment groups on potential confounders. Medication adherence (primary endpoint) was evaluated by the proportion of days covered (PDC). Rescue medication use (secondary endpoint) was standardized to canister equivalents (1 metered dose inhaler [200 puffs] or ~100 nebulized doses of short-acting β2-agonist- and/or short-acting muscarinic agonist-containing medication).
Results:
After IPTW, covariates were balanced between cohorts (UMEC/VI: N=4082; B/F: N=9529). UMEC/VI initiators had a significantly greater mean PDC (UMEC/VI: 0.47 [0.33]; B/F: 0.38 [0.30]; P<0.001) and significantly higher rates of adherence (PDC≥0.80) than B/F initiators (UMEC/VI: n=1004 [25%], B/F: n=1391 [15%]; relative risk: 1.68, 95% CI: 1.57, 1.81; P<0.001). In the year following initiation, UMEC/VI initiators filled significantly fewer rescue medication canister equivalents than B/F initiators (predicted mean [95% CI]: 1.78 [1.69, 1.88] vs 2.15 [2.08, 2.23]; mean difference [95% CI]: -0.37 [-0.50, -0.24]; P<0.001), corresponding to 17% less (estimated) rescue medication use (incidence rate ratio [95% CI]: 0.83 [0.78, 0.88]).
Conclusion:
Among non-exacerbating patients with COPD initiating dual therapy, UMEC/VI demonstrated improved adherence and reduced rescue medication use compared with B/F.
More Related Videos

Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:23
Inhaled Medications
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes: