Related Experiment Video
Updated: Dec 7, 2025
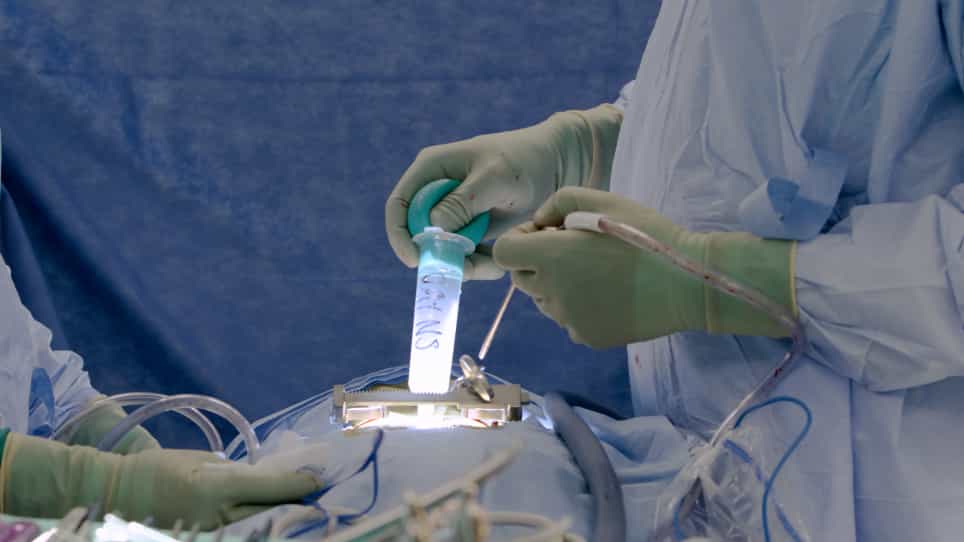

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Neurophysiologic Intraoperative Monitoring for Spine Surgery: A Practical Guide From Past to Present
Lauren K Buhl1,2, Andres Brenes Bastos1, Richard J Pollard1
1Department of Anesthesia, Critical Care, and Pain Medicine, Beth Israel Deaconess Medical Center, Boston, MA, USA.

Intraoperative neuromonitoring was introduced in the second half of the 20th century with the goal of preventing patient morbidity for patients undergoing complex operations of the central and peripheral nervous system. Since its early use for scoliosis surgery, the growth and utilization of IOM techniques expanded dramatically over the past 50 years to include spinal tumor resection and evaluation of cerebral ischemia. The importance of IOM has been broadly acknowledged, and in 1989, the American Academy of Neurology (AAN) released a statement that the use of SSEPs should be standard-of-care during spine surgery. In 2012, both the AAN and the American Clinical Neurophysiology Society (ACNS) recommended that: "Intraoperative monitoring (IOM) using SSEPs and transcranial MEPs be established as an effective means of predicting an increased risk of adverse outcomes, such as paraparesis, paraplegia, and quadriplegia, in spinal surgery." With a multimodal approach that combines SSEPs, MEPs, and sEMG with tEMG and D waves, as appropriate, sensitivity and specificity can be maximized for the diagnosis of reversible insults to the spinal cord, nerve roots, and peripheral nerves. As with most patient safety efforts in the operating room, IOM requires contributions from and communication between a number of different teams. This comprehensive review of neuromonitoring techniques for surgery on the central and peripheral nervous system will highlight the technical, surgical and anesthesia factors required to optimize outcomes. In addition, this review will discuss important trouble shooting measures to be considered when managing ION changes concerning for potential injury.
Intraoperative neuromonitoring was introduced in the second half of the 20th century with the goal of preventing patient morbidity for patients undergoing complex operations of the central and peripheral nervous system. Since its early use for scoliosis surgery, the growth and utilization of IOM techniques expanded dramatically over the past 50 years to include spinal tumor resection and evaluation of cerebral ischemia. The importance of IOM has been broadly acknowledged, and in 1989, the American Academy of Neurology (AAN) released a statement that the use of SSEPs should be standard-of-care during spine surgery. In 2012, both the AAN and the American Clinical Neurophysiology Society (ACNS) recommended that: "Intraoperative monitoring (IOM) using SSEPs and transcranial MEPs be established as an effective means of predicting an increased risk of adverse outcomes, such as paraparesis, paraplegia, and quadriplegia, in spinal surgery." With a multimodal approach that combines SSEPs, MEPs, and sEMG with tEMG and D waves, as appropriate, sensitivity and specificity can be maximized for the diagnosis of reversible insults to the spinal cord, nerve roots, and peripheral nerves. As with most patient safety efforts in the operating room, IOM requires contributions from and communication between a number of different teams. This comprehensive review of neuromonitoring techniques for surgery on the central and peripheral nervous system will highlight the technical, surgical and anesthesia factors required to optimize outcomes. In addition, this review will discuss important trouble shooting measures to be considered when managing ION changes concerning for potential injury.


Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:22
Aneurysm IV: Nursing Management
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...