
Tucatinib Inhibits Renal Transporters OCT2 and MATE Without Impacting Renal Function in Healthy Subjects
Ariel R Topletz-Erickson1, Anthony J Lee2, JoAl G Mayor3
1Clinical Pharmacology, Seattle Genetics, Bothell, Washington, USA.

Abstract:
Tucatinib is a potent tyrosine kinase inhibitor selective for human epidermal growth factor receptor 2 (HER2) approved by the US Food and Drug Administration for the treatment of HER2-positive metastatic breast cancer and in development for other HER2-positive solid tumors. Modest, reversible serum creatinine (SCr) elevations have been observed in tucatinib clinical trials. SCr is conveyed by the renal drug transporters organic cation transporter 2 (OCT2) and multidrug and toxin extrusion protein 1 (MATE1) and 2-K (MATE2-K) and can increase in the presence of inhibitors of these transporters. In vitro, tucatinib inhibited OCT2-, MATE1-, and MATE2-K-mediated transport of metformin, with IC50 values of 14.7, 0.340, and 0.135 µM, respectively. Tucatinib also inhibited OCT2- and MATE1-mediated transport of creatinine, with IC50 values of 0.107 and 0.0855 µM, respectively. A phase 1 study with metformin administered orally in the absence and presence of tucatinib was conducted in 18 healthy subjects. Renal function was assessed by measuring glomerular filtration rate (GFR; based on iohexol plasma clearance) and endogenous markers (SCr, cystatin C-based estimated glomerular filtration rate [eGFR]) with and without tucatinib. Metformin exposure increased (1.4-fold) and renal clearance decreased (29.99-17.64 L/h) with tucatinib, with no effect on metformin maximum concentration. Creatinine clearance transiently decreased 23% with tucatinib. GFR and eGFR, which are unaffected by OCT2 and/or MATE1/2-K transport, were unchanged with tucatinib. These data demonstrate that tucatinib inhibits OCT2- and MATE1/2-K-mediated tubular secretion of creatinine, which may manifest as mild SCr elevations that are not indicative of renal impairment.
Insights
Tucatinib, a HER2-positive cancer drug, can cause mild serum creatinine elevations by inhibiting renal transporters OCT2 and MATE1/2-K. These elevations do not indicate actual kidney impairment.
Area of Science:
- Pharmacology
- Nephrology
- Oncology
Background:
- Tucatinib is a selective HER2 tyrosine kinase inhibitor used for HER2-positive cancers.
- Mild, reversible serum creatinine elevations are noted in tucatinib trials.
- Serum creatinine is transported by renal organic cation transporter 2 (OCT2) and multidrug and toxin extrusion 1 and 2-K (MATE1/2-K).
Purpose of the Study:
- To investigate the mechanism behind tucatinib-induced serum creatinine elevations.
- To assess the impact of tucatinib on renal transporters OCT2 and MATE1/2-K.
- To determine if tucatinib affects true renal function.
Main Methods:
- In vitro inhibition assays of metformin and creatinine transport by tucatinib using OCT2, MATE1, and MATE2-K.
- Phase 1 clinical study in healthy subjects administering metformin with and without tucatinib.
- Assessment of renal function using iohexol plasma clearance (GFR), serum creatinine (SCr), and cystatin C-based estimated glomerular filtration rate (eGFR).
Main Results:
- Tucatinib inhibited OCT2, MATE1, and MATE2-K mediated transport of metformin and creatinine in vitro.
- In vivo, tucatinib increased metformin exposure and decreased its renal clearance but did not affect maximum concentration.
- Tucatinib caused a transient 23% decrease in creatinine clearance, but GFR and eGFR remained unchanged.
Conclusions:
- Tucatinib inhibits OCT2- and MATE1/2-K-mediated tubular secretion of creatinine.
- The observed serum creatinine elevations are a result of transporter inhibition, not a decline in glomerular filtration rate.
- Tucatinib-induced SCr elevations are not indicative of actual renal impairment.


Related Concept Videos
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:15
Renal Drug Excretion: Overview
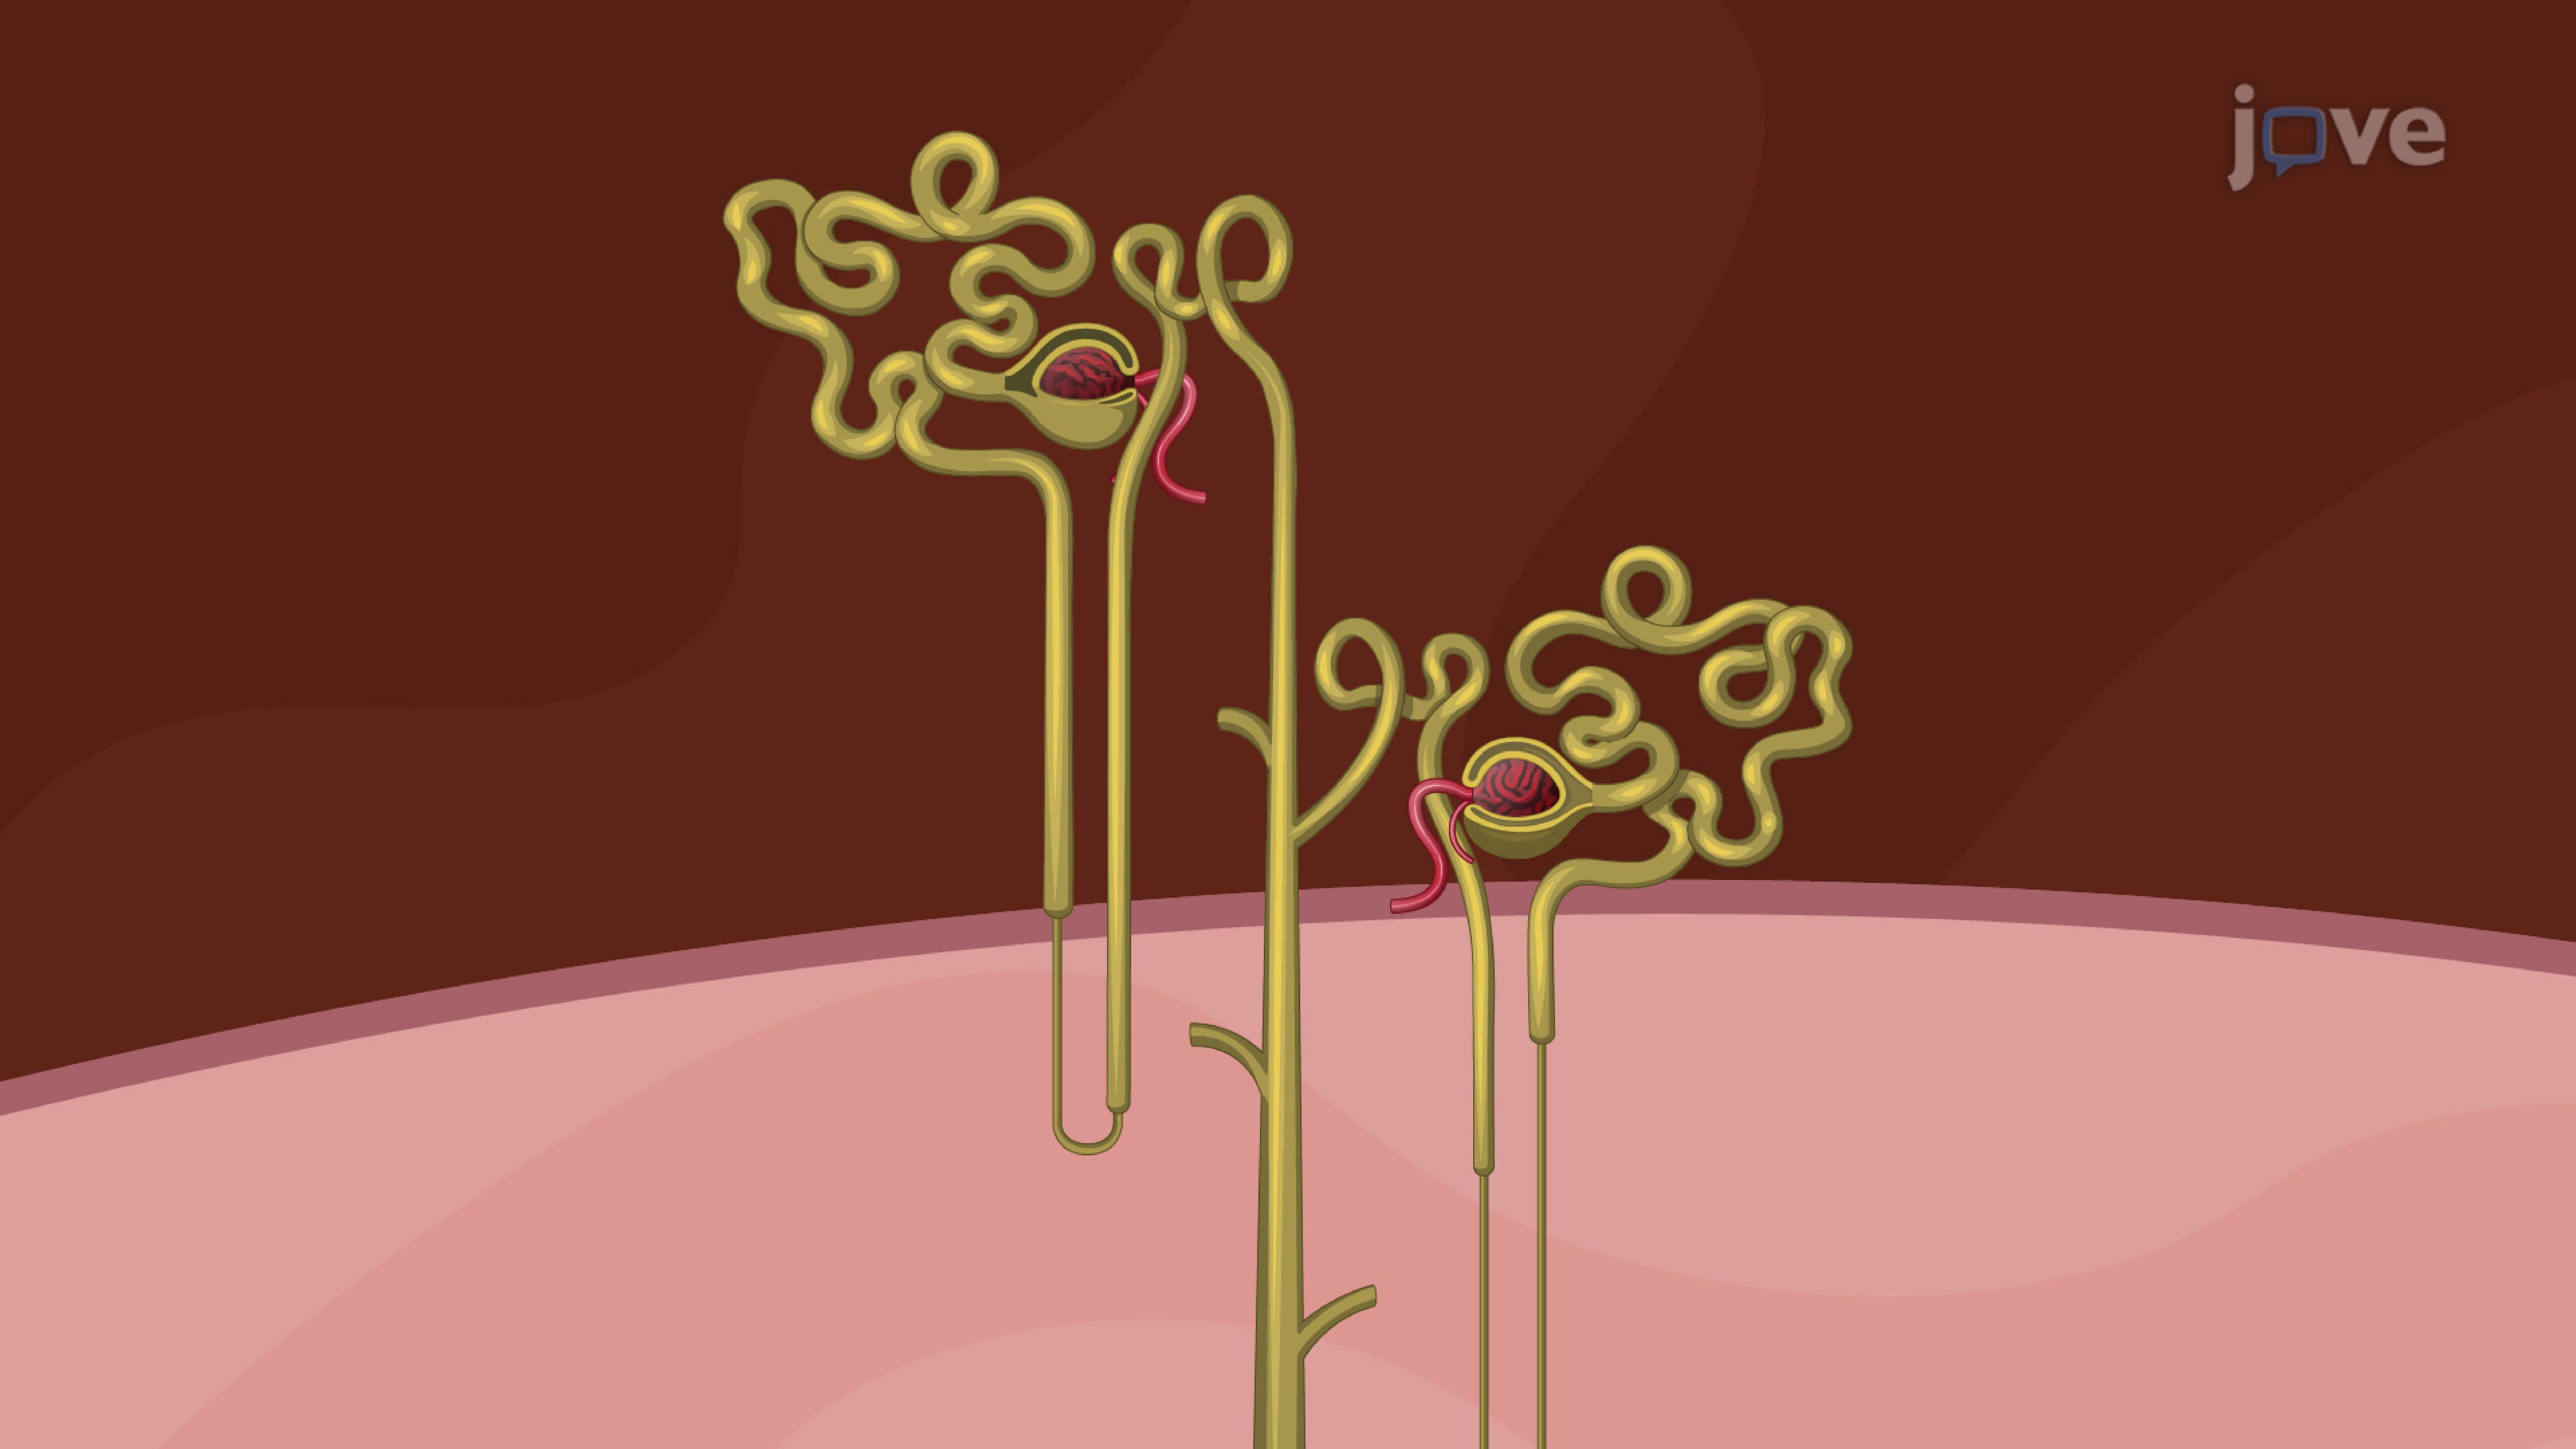
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
Renal Drug Clearance: Overview
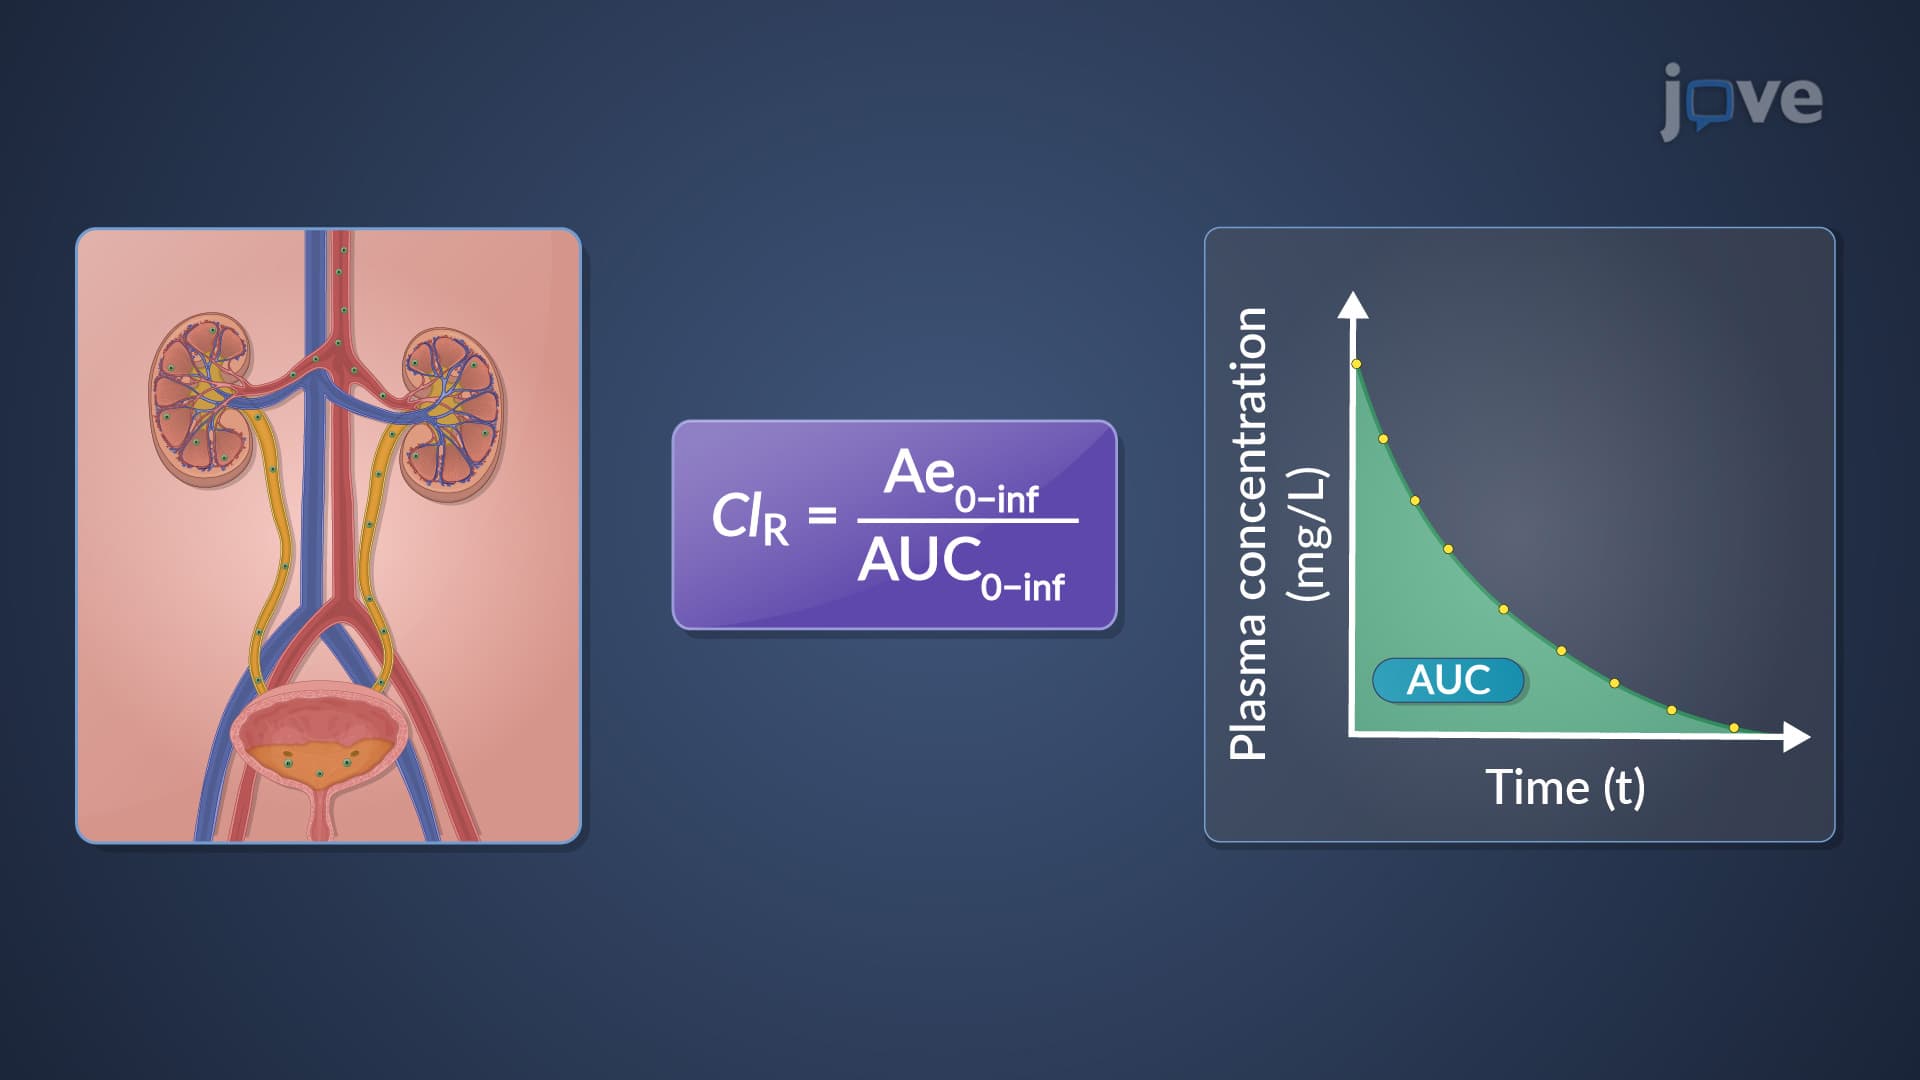
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...