Related Experiment Video
Updated: Dec 7, 2025

Development of a Uterosacral Ligament Suspension Rat Model
Published on: August 17, 2022
Rectal Prolapse Concomitant with Uterovaginal Prolapse Protects the Ileum from Necrosis in Transanal Ileum
Vicky Sumarki Budipramana1, Deddy Aryanda Putra1
1Department of Surgery, Faculty of Medicine, Universitas Airlangga/Dr. Soetomo General Hospital, Surabaya, Indonesia.

Eviscerated ileum passing through a traumatic tear on the sigmoid wall is a rare case and all the cases reported previously showed that the eviscerated intestines were necrotic. However, in this case, although the huge size of eviscerated intestine had already exceeded the intestinal ischemic time, the small intestine outside the anus was not necrotic. Here we report the case of a 73-year-old female who presented with evisceration of the small intestine out of her anus as long as 200 cm 7 h before. The eviscerated small intestine (ileum) appeared still viable and there were no signs of pain, obstruction, or peritonitis. An intermittent rectal concomitant with uterovaginal prolapse had been experienced by the patient before. On surgery, the ileum was not necrotic and pulled back out of the sigmoid wall tear. The cardinal uterosacral ligament may have an important role in maintaining the uterovagina in place. When this ligament loses its ability to anchor the uterovagina to the sacrum, both the uterovagina and the rectum will lose their fixation to the sacrum and prolapse will occur. Hence, the rectum located posterior to the uterovagina also relieves its squeeze pressure so that it will not disrupt the blood supply of the ileum when the ileum enters through the rectal lumen. Rectal concomitant with uterovaginal prolapse is an important factor to maintain the viability of the eviscerated intestine. Therefore, surgeons are still able to make better preparation before performing surgery.
Eviscerated ileum passing through a traumatic tear on the sigmoid wall is a rare case and all the cases reported previously showed that the eviscerated intestines were necrotic. However, in this case, although the huge size of eviscerated intestine had already exceeded the intestinal ischemic time, the small intestine outside the anus was not necrotic. Here we report the case of a 73-year-old female who presented with evisceration of the small intestine out of her anus as long as 200 cm 7 h before. The eviscerated small intestine (ileum) appeared still viable and there were no signs of pain, obstruction, or peritonitis. An intermittent rectal concomitant with uterovaginal prolapse had been experienced by the patient before. On surgery, the ileum was not necrotic and pulled back out of the sigmoid wall tear. The cardinal uterosacral ligament may have an important role in maintaining the uterovagina in place. When this ligament loses its ability to anchor the uterovagina to the sacrum, both the uterovagina and the rectum will lose their fixation to the sacrum and prolapse will occur. Hence, the rectum located posterior to the uterovagina also relieves its squeeze pressure so that it will not disrupt the blood supply of the ileum when the ileum enters through the rectal lumen. Rectal concomitant with uterovaginal prolapse is an important factor to maintain the viability of the eviscerated intestine. Therefore, surgeons are still able to make better preparation before performing surgery.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
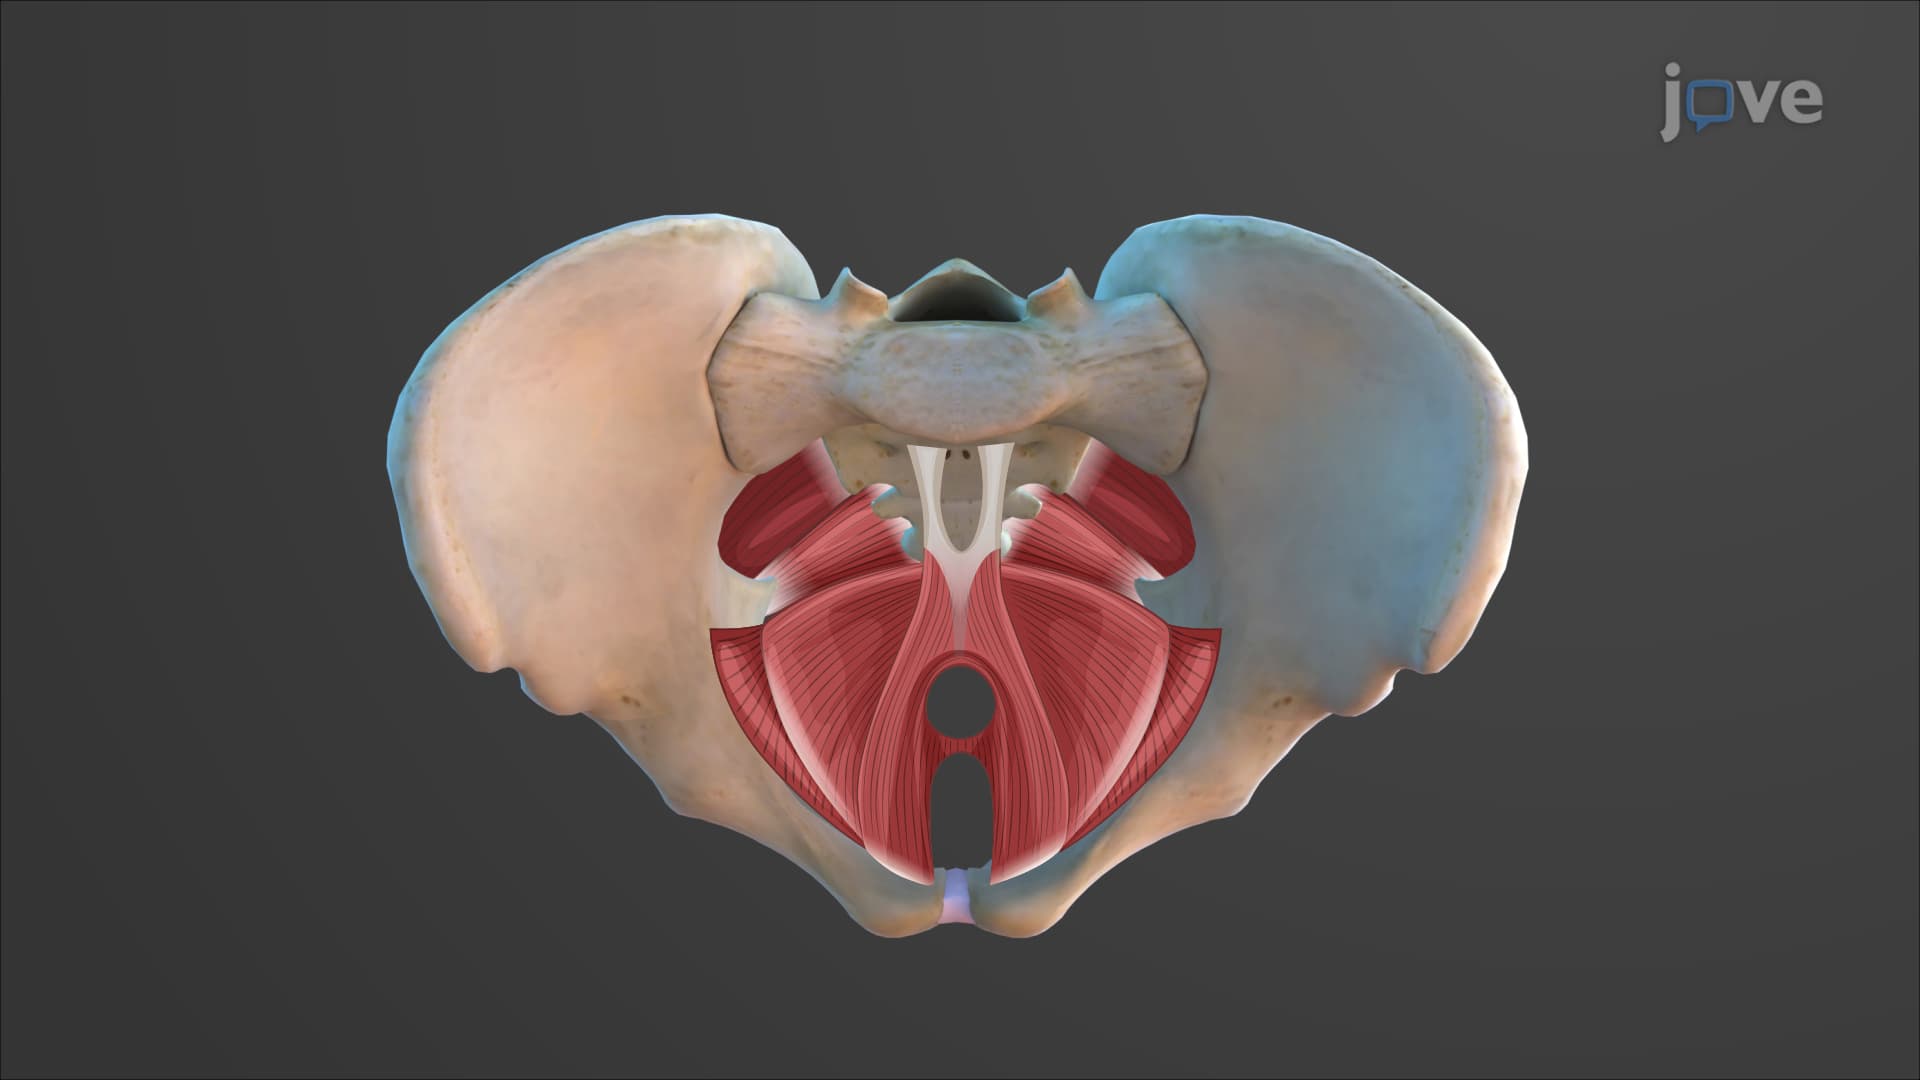
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
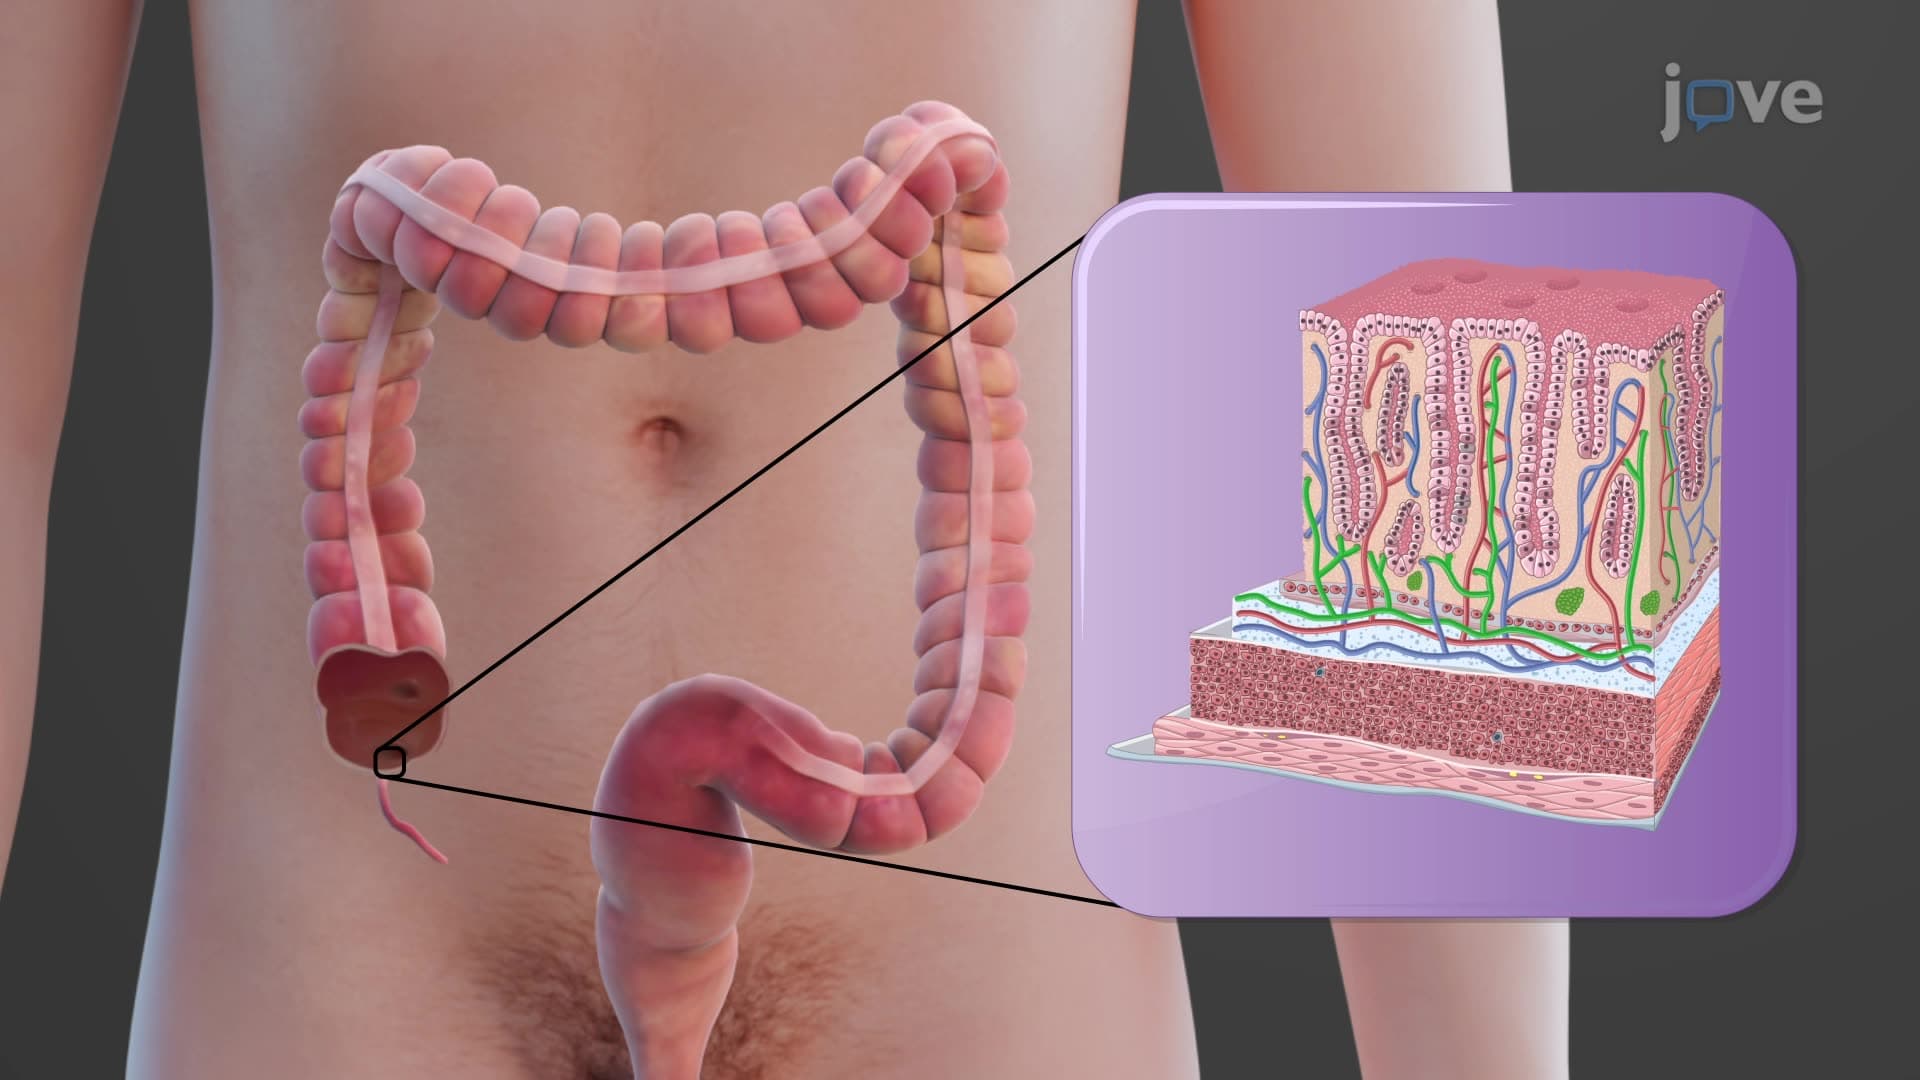
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...