Related Experiment Video
Updated: Dec 7, 2025


Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
Neuromuscular Blockade Monitoring in Acute Respiratory Distress Syndrome: Randomized Controlled Trial of Clinical
Saïda Rezaiguia-Delclaux1, Florent Laverdure1, Thibaut Genty1
1From the Cardiothoracic Intensive Care Unit.

Background:
Whether train-of-four (TOF) monitoring is more effective than clinical monitoring to guide neuromuscular blockade (NMB) in patients with acute respiratory distress syndrome (ARDS) is unclear. We compared clinical monitoring alone or with TOF monitoring to guide atracurium dosage adjustment with respect to drug dose and respiratory parameters.
Methods:
From 2015 to 2016, we conducted a randomized controlled trial comparing clinical assessments every 2 hours with or without corrugator supercilii TOF monitoring every 4 hours in patients who developed ARDS (Pao2/Fio2 <150 mm Hg) in a cardiothoracic intensive care unit. The primary outcome was the cumulative atracurium dose (mg/kg/h). Secondary outcomes included respiratory parameters during the neuromuscular blockade.
Results:
A total of 38 patients in the clinical + TOF (C + TOF) group and 39 patients in the clinical (C) group were included in an intention-to-treat (ITT) analysis. The cumulative atracurium dose was higher in the C + TOF group (1.06 [0.75-1.30] vs 0.65 [0.60-0.89] mg/kg/h in the C group; P < .001) compared to C group, as well as the atracurium daily dose (C + TOF - C group mean difference = 0.256 mg/kg/h [95% confidence interval {CI}, 0.099-0.416], P = .026). Driving pressures during neuromuscular blocking agent (NMBA) administration did not differ between groups (P = .653). Intensive care unit (ICU) mortality was 22% in the C group and 27% in the C + TOF group (P = .786). Days on ventilation were 17 (8-26) in the C group and 16 (10-35) in the C + TOF group.
Conclusions:
In patients with ARDS, adding TOF to clinical monitoring of neuromuscular blockade did not change ICU mortality or days on mechanical ventilation (MV) but did increase atracurium consumption when compared to clinical assessment alone. TOF monitoring may not be needed in all patients who receive neuromuscular blockade for ARDS.
More Related Videos
 07:53
Assessment of Neuromuscular Function Using Percutaneous Electrical Nerve Stimulation
Published on: September 13, 2015
 09:37
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:28
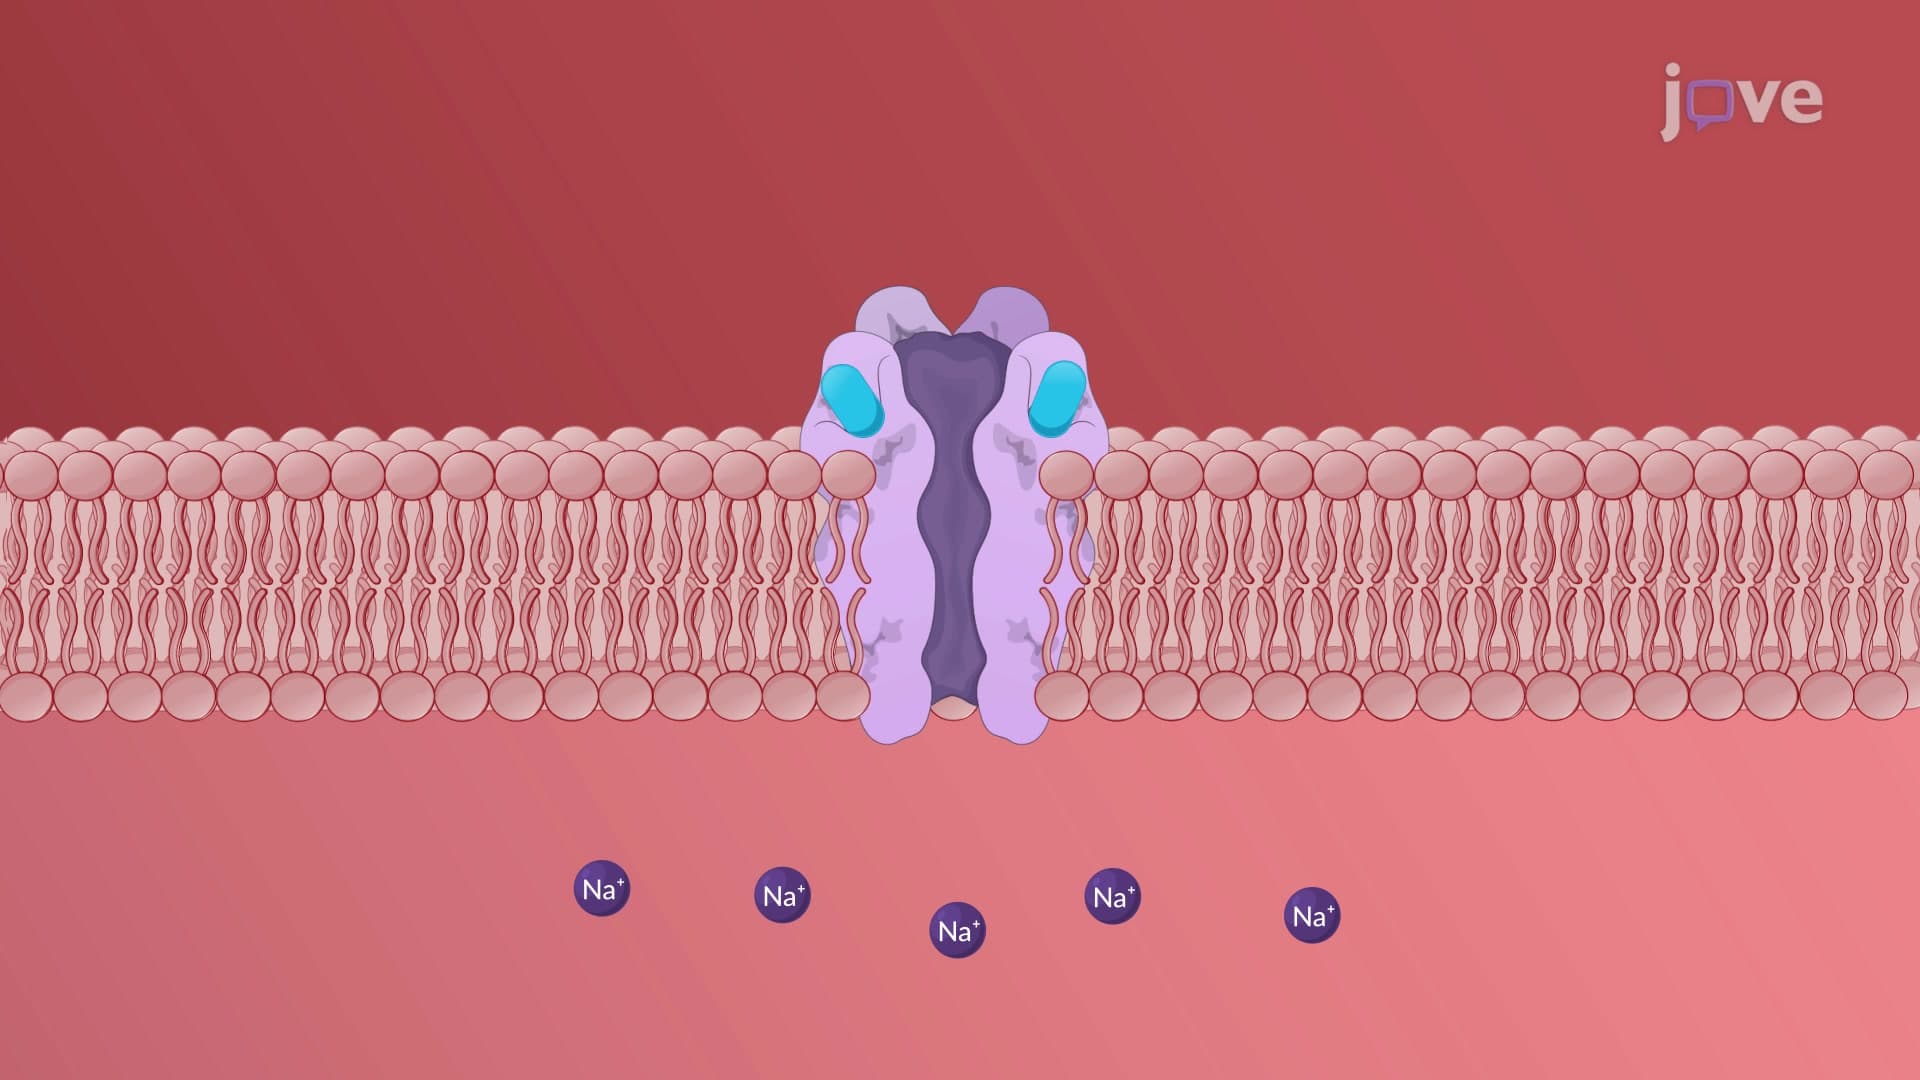
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because...
 01:17
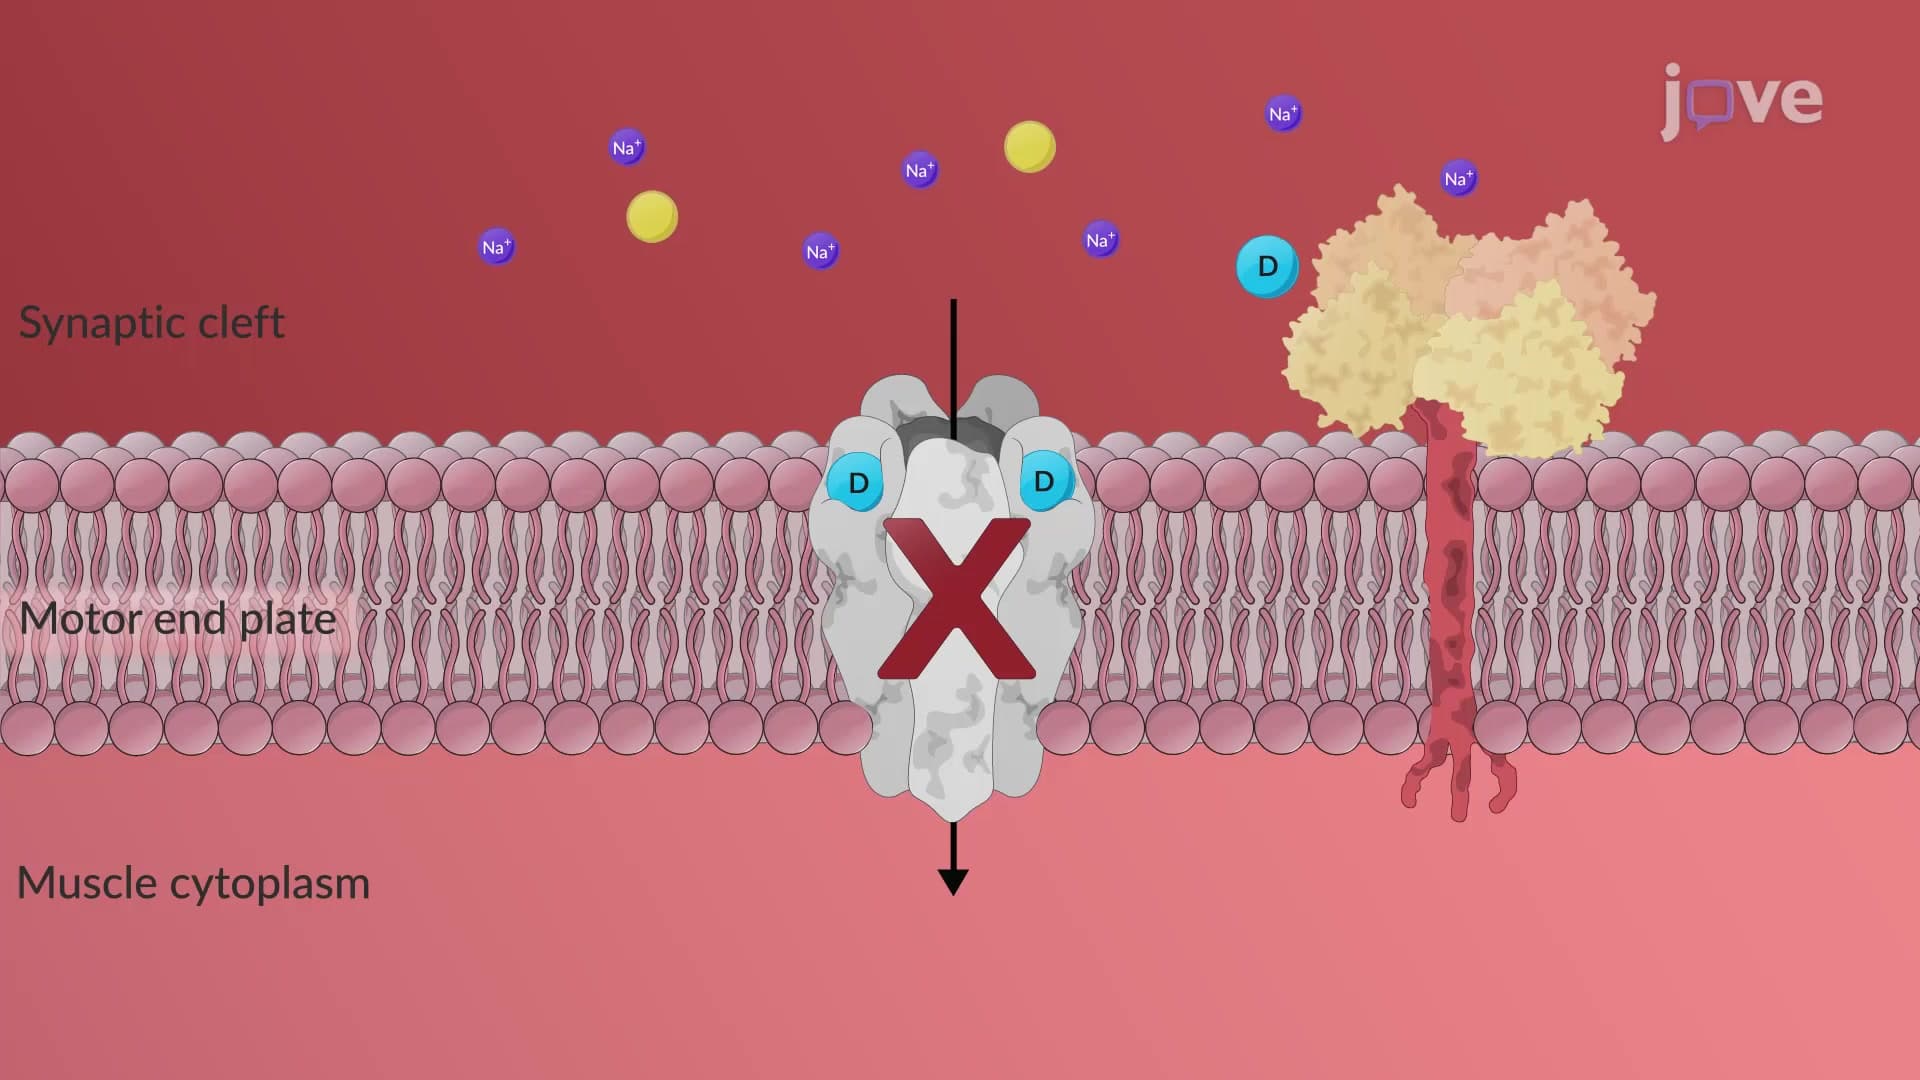
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...