Related Experiment Video
Updated: Dec 6, 2025


Dynamic Imaging of Chimeric Antigen Receptor T Cells with [18F]Tetrafluoroborate Positron Emission Tomography/Computed Tomography
Published on: February 17, 2022
Rituximab Hypersensitivity: From Clinical Presentation to Management
1Allergy and Immunology Center, Al-Azhar University, Cairo, Egypt.

Rituximab is a chimeric monoclonal antibody (mAb) against CD20 molecule which is expressed on human B cells. It has been used for the treatment of various lymphoid malignancies, lymphoproliferative diseases, and rheumatologic disorders. Rituximab is generally well tolerated. However, increased use of rituximab has been associated with hypersensitivity reactions (HSRs), which can be classified as infusion-related, cytokine-release, type I (IgE/non-IgE), mixed, type III, and type IV reactions. Immediate infusion-related reactions to rituximab are quite common and decrease in frequency with subsequent infusions. However, in about 10% of patients, severe infusion-related reactions develop, which prevent its use. Some of the immediate infusion reactions are due to a cytokine-release but some reactions raise concerns for type I (IgE/non-IgE) hypersensitivity. Recent studies have shown the presence of serum anti-rituximab antibodies, either represented by the IgG or IgE isotype. In some cases, clinical manifestations of IgE-mediated reactions and cytokine-release reactions partially overlap, which is called a mixed reaction. Classified as Type III reaction, rituximab-induced serum sickness reactions have been reported in patients with autoimmune diseases and hematological malignancies. The classic serum sickness triad (fever, rash, and arthralgia) has been observed in patients mainly with an underlying rheumatologic condition. Severe delayed type IV hypersensitivity reactions including non-severe maculopapular rash to severe reactions such as Stevens-Johnson syndrome and toxic epidermal necrolysis have been rarely reported following rituximab injection. Comprehensive reviews focused on rituximab-induced HSRs are scarce. We aimed to review clinical presentations, underlying mechanisms of rituximab hypersensitivity, as well as management including rapid drug desensitization.
Rituximab is a chimeric monoclonal antibody (mAb) against CD20 molecule which is expressed on human B cells. It has been used for the treatment of various lymphoid malignancies, lymphoproliferative diseases, and rheumatologic disorders. Rituximab is generally well tolerated. However, increased use of rituximab has been associated with hypersensitivity reactions (HSRs), which can be classified as infusion-related, cytokine-release, type I (IgE/non-IgE), mixed, type III, and type IV reactions. Immediate infusion-related reactions to rituximab are quite common and decrease in frequency with subsequent infusions. However, in about 10% of patients, severe infusion-related reactions develop, which prevent its use. Some of the immediate infusion reactions are due to a cytokine-release but some reactions raise concerns for type I (IgE/non-IgE) hypersensitivity. Recent studies have shown the presence of serum anti-rituximab antibodies, either represented by the IgG or IgE isotype. In some cases, clinical manifestations of IgE-mediated reactions and cytokine-release reactions partially overlap, which is called a mixed reaction. Classified as Type III reaction, rituximab-induced serum sickness reactions have been reported in patients with autoimmune diseases and hematological malignancies. The classic serum sickness triad (fever, rash, and arthralgia) has been observed in patients mainly with an underlying rheumatologic condition. Severe delayed type IV hypersensitivity reactions including non-severe maculopapular rash to severe reactions such as Stevens-Johnson syndrome and toxic epidermal necrolysis have been rarely reported following rituximab injection. Comprehensive reviews focused on rituximab-induced HSRs are scarce. We aimed to review clinical presentations, underlying mechanisms of rituximab hypersensitivity, as well as management including rapid drug desensitization.
More Related Videos
 06:08
Assessment of Chimeric Antigen Receptor T Cell-Associated Toxicities Using an Acute Lymphoblastic Leukemia Patient-Derived Xenograft Mouse Model
Published on: February 10, 2023
 07:25
In Vitro Methods for Comparing Target Binding and CDC Induction Between Therapeutic Antibodies: Applications in Biosimilarity Analysis
Published on: May 4, 2017
Related Concept Videos
 01:30
Hypersensitivities
Types of Hypersensitivities
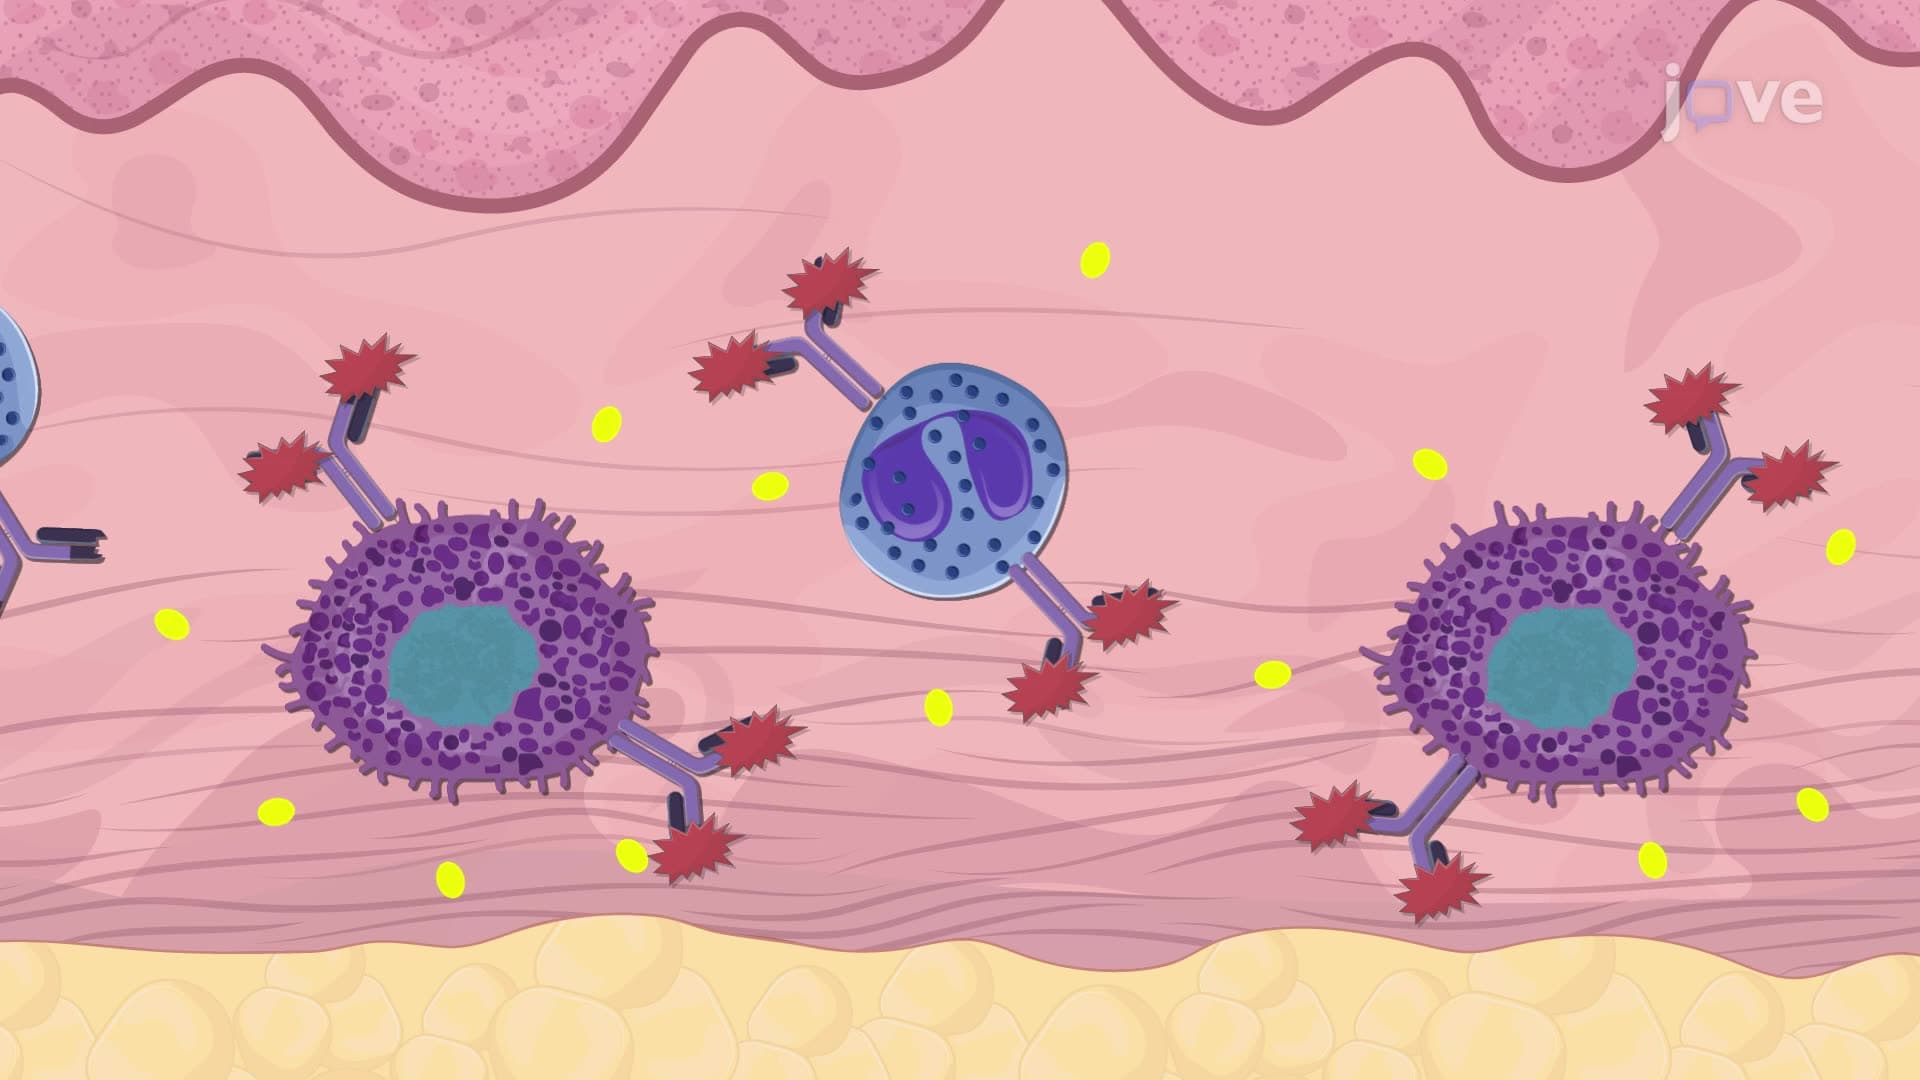
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:21
Rheumatic Heart Disease III: Medical Management
 01:20
Rheumatic Heart Disease IV: Nursing Management
 01:27
Allergic Drug Reactions
 00:42
Cross-reactivity