Related Experiment Video
Updated: Aug 14, 2026

Isolation of Brain-infiltrating Leukocytes
Published on: June 13, 2011
Cerebrospinal fluid and peripheral blood leukocyte subsets in acute inflammation of the CNS

Abstract:
Leukocyte subsets in CSF and peripheral blood (PB) were determined in 21 patients with acute inflammation of the CNS using the monoclonal antibodies OKT3, OKT4, OKT8, Leu12, and OKM1 in an immunoperoxidase slide assay. There was a predominance of OKT3-positive cells in nearly all samples. Significant differences between acute aseptic and bacterial meningitis only were found in CSF and represented by a higher Leu12 and a lower OKT3 percentage in aseptic inflammation and a higher absolute amount of OKT4-, OKM1- and Leu12-positive cells in bacterial meningitis. Comparison between CSF and PB showed significant differences only in aseptic meningitis with a higher percentage of Leu12-positive cells and a lower percentage of OKT8-positive cells in CSF. The OKT4/OKT8 ratio seems to be generally lower in aseptic meningitis but significant differences only were found in comparison with healthy blood donors. In a case of herpes simplex encephalitis the ratio was strongly increased in CSF during the early phase of specific antibody production because of an absolute rise of OKT4-positive cells.
More Related Videos
 12:42
Stereological and Flow Cytometry Characterization of Leukocyte Subpopulations in Models of Transient or Permanent Cerebral Ischemia
Published on: December 28, 2014
 09:35
Isolating Central Nervous System Tissues and Associated Meninges for the Downstream Analysis of Immune cells
Published on: May 19, 2020
Related Concept Videos
 01:15
Differentiation of Common Myeloid Progenitor Cells
 01:21
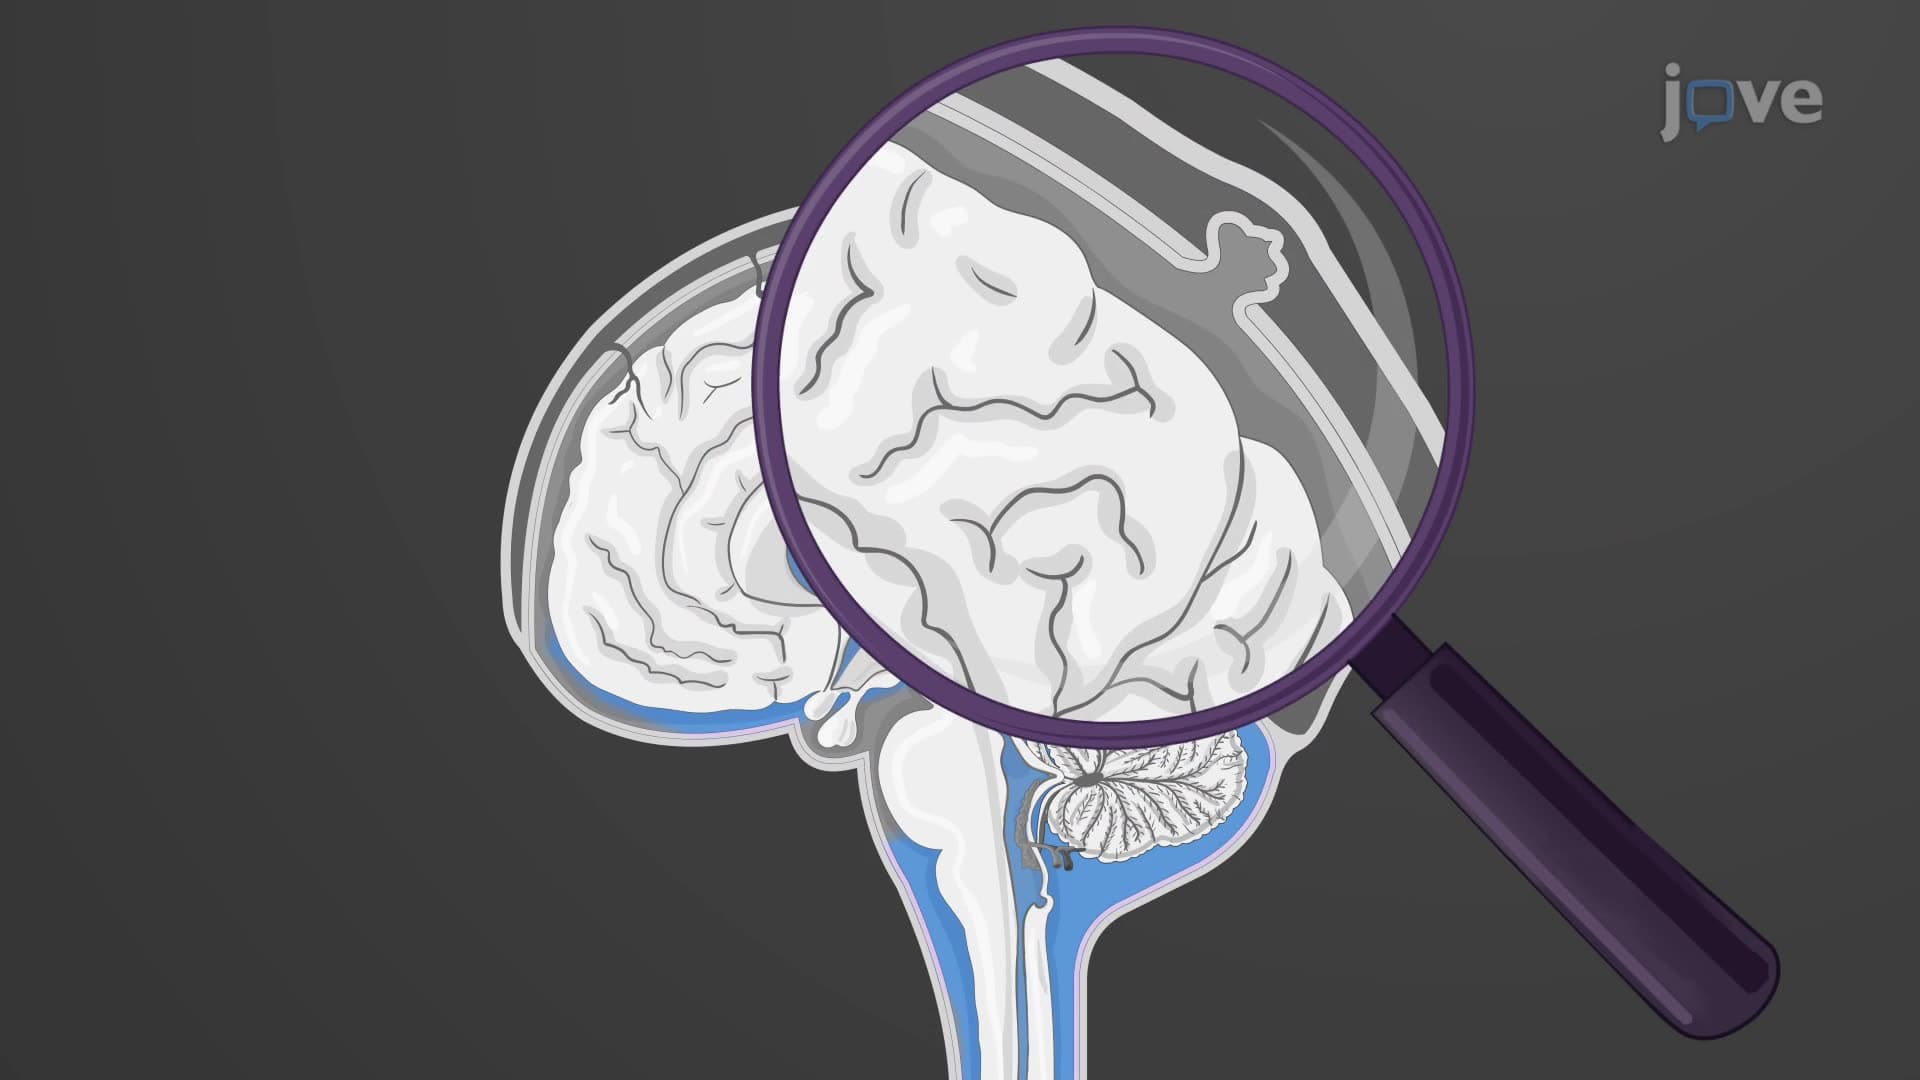
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain.
 01:26
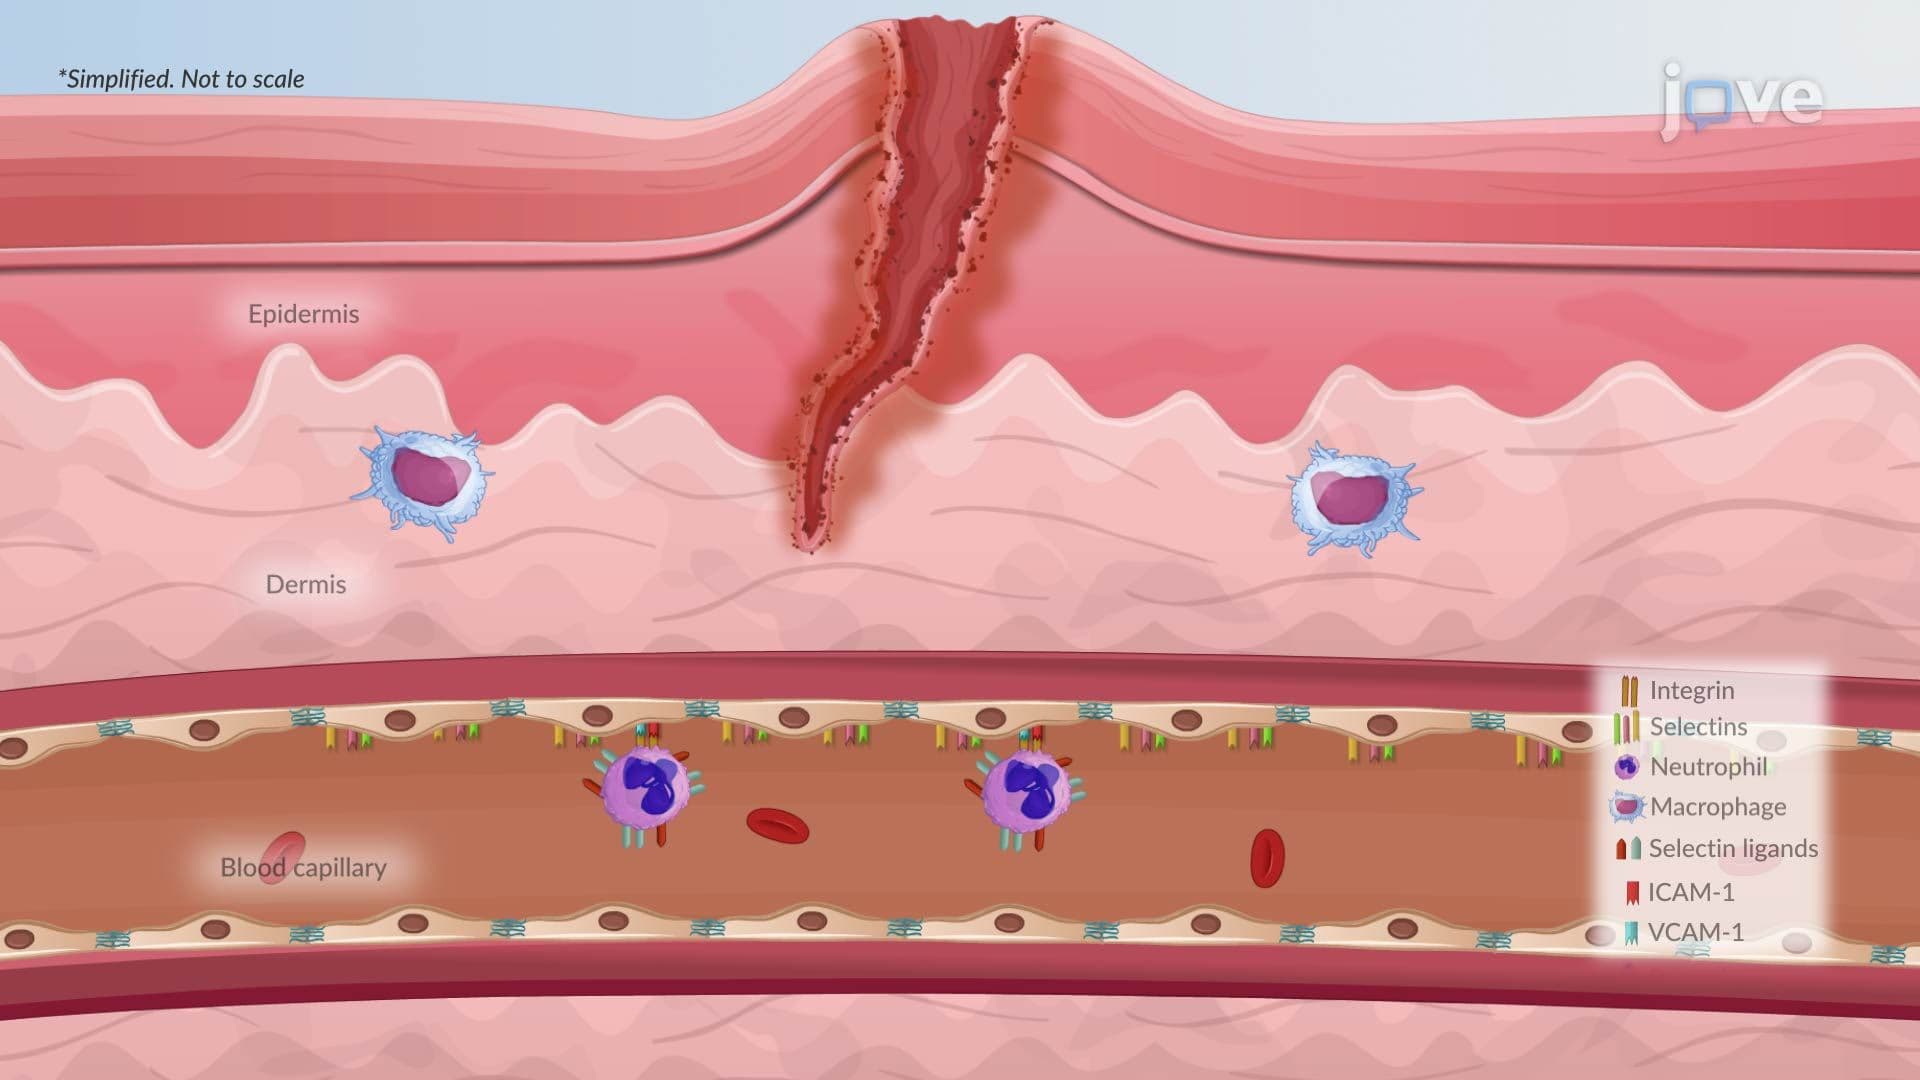
Acute Inflammation I: Inflammatory Response
 01:26
Acute Inflammation II: Cellular Phase
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:26
Bacterial Meningitis II: Pathophysiology