Related Experiment Video
Updated: Dec 6, 2025
Dural Stimulation and Periorbital von Frey Testing in Mice As a Preclinical Model of Headache
Published on: July 29, 2021
Incidences and risk factors for post--dural puncture headache after neuraxial anaesthesia: A national inpatient
Kanako Makito1, Hiroki Matsui1, Kiyohide Fushimi2
1Department of Clinical Epidemiology and Health Economics, School of Public Health, The University of Tokyo, Tokyo, Japan.

The reported incidence of post--dural puncture headache (PDPH) after neuraxial anaesthesia varies widely, depending on patient and procedural risk factors. Most previous studies have had small sample sizes and focused on obstetric patients. This study aimed to investigate the incidence of PDPH and factors associated with PDPH in non-obstetric and obstetric patients after neuraxial anaesthesia. We identified patients who underwent surgery with neuraxial anaesthesia between July 2010 and December 2017 from a Japanese nationwide inpatient administrative claims and discharge database. Factors associated with PDPH (body mass index (BMI), depression, spinal abnormalities, academic hospital and location of epidural anaesthesia) were examined using multivariable logistic analyses. The incidence of PDPH in non-obstetric patients after spinal anaesthesia, epidural anaesthesia and combined spinal epidural anaesthesia was 0.16%, 0.13% and 0.23% and in obstetric patients was 1.16%, 0.99% and 1.05%, respectively. Higher BMI was associated with decreased incidence of PDPH in non-obstetric patients receiving spinal anaesthesia and obstetric patients receiving epidural anaesthesia. In female patients receiving spinal anaesthesia, a history of depression was associated with increased incidence of PDPH. Being in an academic hospital was associated with decreased incidence of PDPH in male patients receiving spinal anaesthesia and female patients receiving spinal or epidural anaesthesia, but increased incidence of PDPH in male patients receiving epidural anaesthesia. Lumbar epidural anaesthesia was associated with increased incidence of PDPH in male patients, but decreased incidence of PDPH in obstetric patients compared with thoracic epidural anaesthesia. The present study identified several potential new risk factors for PDPH, and revealed that the incidence of PDPH in non-obstetric patients after neuraxial anaesthesia was lower than in obstetric patients.
The reported incidence of post--dural puncture headache (PDPH) after neuraxial anaesthesia varies widely, depending on patient and procedural risk factors. Most previous studies have had small sample sizes and focused on obstetric patients. This study aimed to investigate the incidence of PDPH and factors associated with PDPH in non-obstetric and obstetric patients after neuraxial anaesthesia. We identified patients who underwent surgery with neuraxial anaesthesia between July 2010 and December 2017 from a Japanese nationwide inpatient administrative claims and discharge database. Factors associated with PDPH (body mass index (BMI), depression, spinal abnormalities, academic hospital and location of epidural anaesthesia) were examined using multivariable logistic analyses. The incidence of PDPH in non-obstetric patients after spinal anaesthesia, epidural anaesthesia and combined spinal epidural anaesthesia was 0.16%, 0.13% and 0.23% and in obstetric patients was 1.16%, 0.99% and 1.05%, respectively. Higher BMI was associated with decreased incidence of PDPH in non-obstetric patients receiving spinal anaesthesia and obstetric patients receiving epidural anaesthesia. In female patients receiving spinal anaesthesia, a history of depression was associated with increased incidence of PDPH. Being in an academic hospital was associated with decreased incidence of PDPH in male patients receiving spinal anaesthesia and female patients receiving spinal or epidural anaesthesia, but increased incidence of PDPH in male patients receiving epidural anaesthesia. Lumbar epidural anaesthesia was associated with increased incidence of PDPH in male patients, but decreased incidence of PDPH in obstetric patients compared with thoracic epidural anaesthesia. The present study identified several potential new risk factors for PDPH, and revealed that the incidence of PDPH in non-obstetric patients after neuraxial anaesthesia was lower than in obstetric patients.
More Related Videos
 03:14
Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024
Related Concept Videos
 01:29
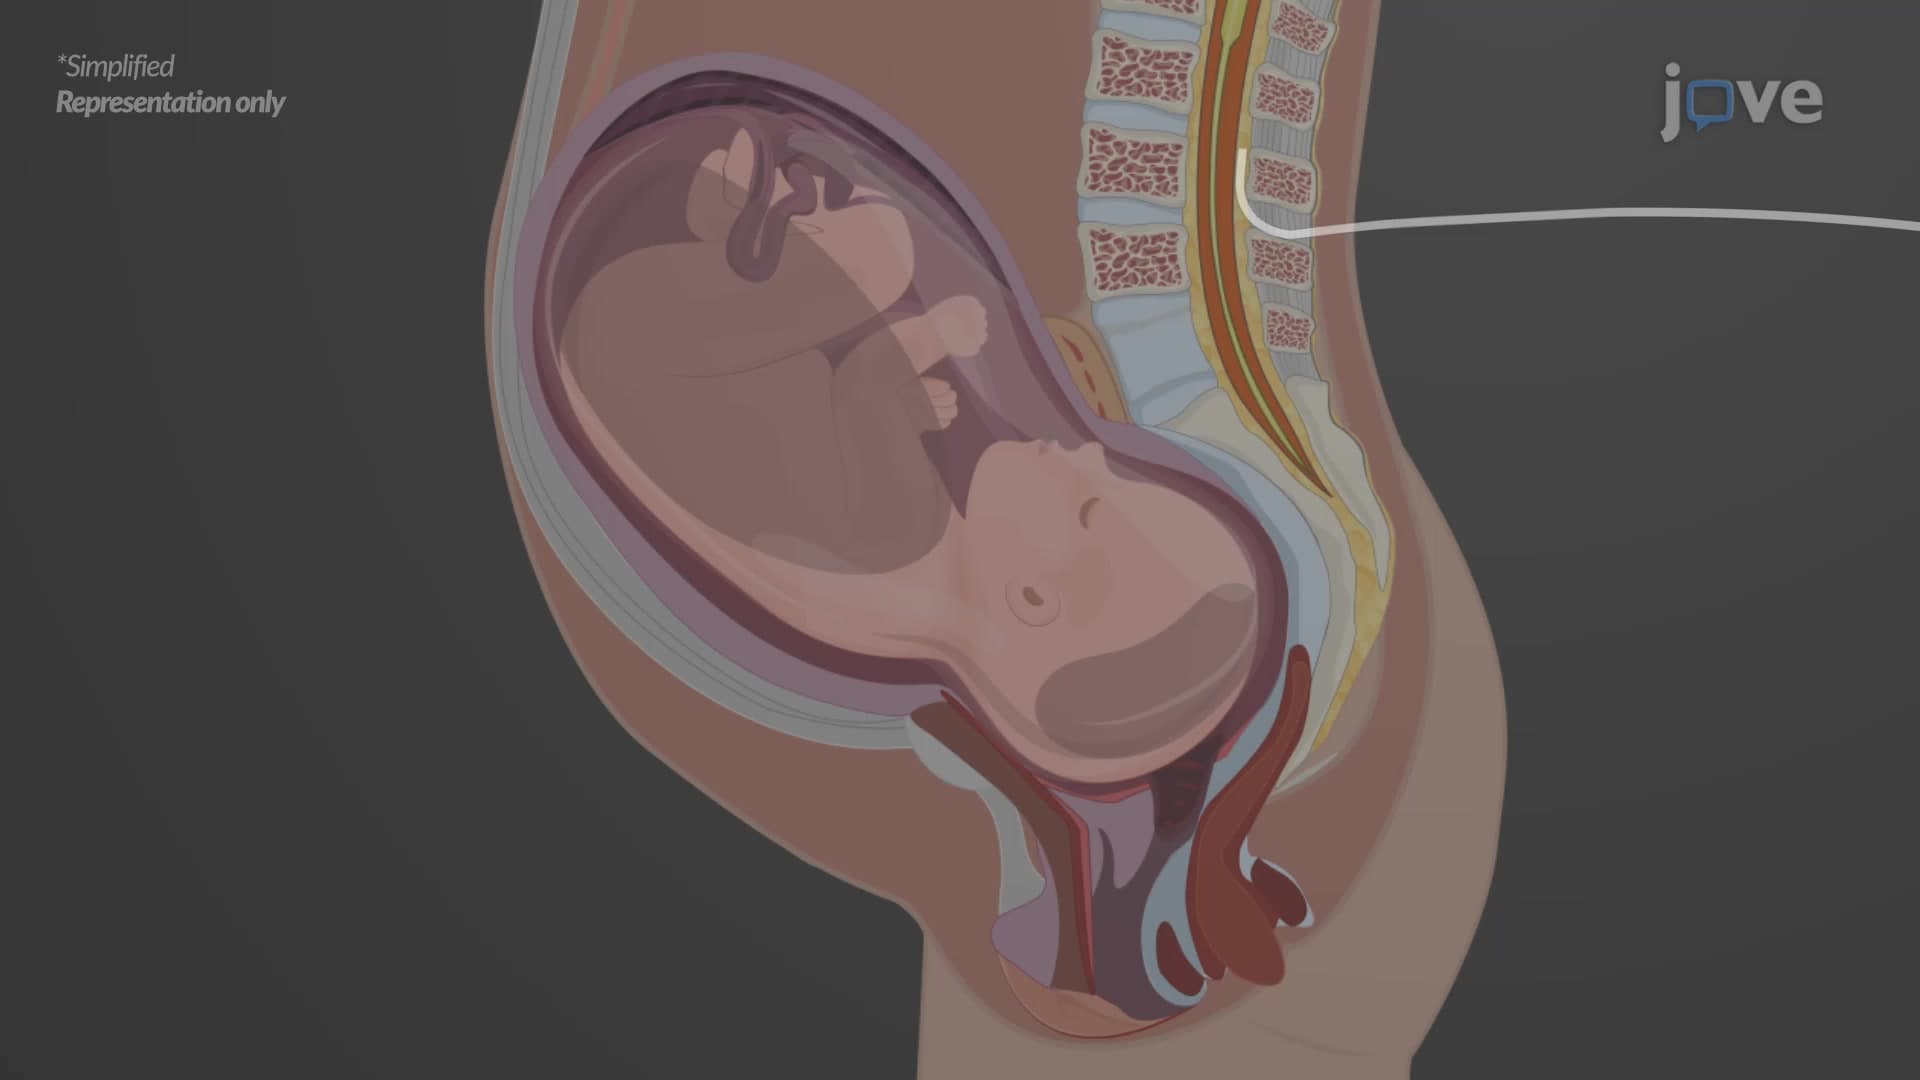
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:12
Local Anesthetics: Adverse Effects
Once absorbed into the systemic circulation, local anesthetics can affect the organs that depend on the functioning of sodium...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:22
Aneurysm IV: Nursing Management