Related Experiment Video
Updated: Dec 6, 2025


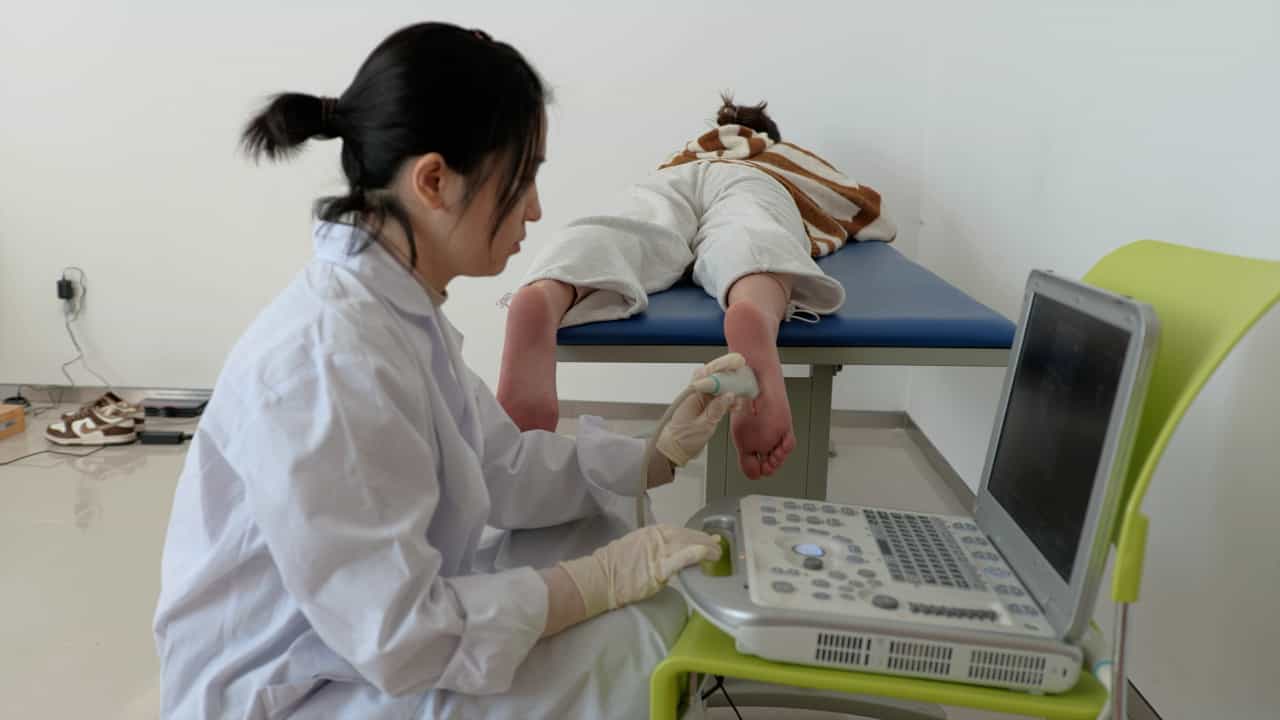
Predictive Measurement for Windlass Change in Length and Selected Treatment Outcomes in Chronic Plantar Fasciitis
Published on: March 1, 2024
[Etiology, pathogenesis, clinical features, diagnostics and conservative treatment of adult flatfoot]
N Gutteck1, S Schilde2, K S Delank2
1Department für Orthopädie, Unfall- und Wiederherstellungschirurgie, Martin-Luther-Universität Halle-Wittenberg, Ernst-Grube Str. 40, 06120, Halle (Saale), Deutschland. Natalia.gutteck@uk-halle.de.

Background:
On average, one in six adults is affected by an acquired flatfoot. This foot deformity is characterized by its progression of stages and in 10% of cases causes complaints that require treatment. Untreated, the loss of walking ability may result in the final stage. Correct staging is crucial to being able to offer a specific course of therapy including a wide spectrum of conservative and operative treatments.
Material And Methods:
This review is based on pertinent publications retrieved from a selective search in PubMed and Medline and on the authors' clinical experience.
Diagnostics:
The loss of function of static (spring ligament complex) and dynamic (tibialis posterior tendon) stabilizers causes the characteristic deformity with loss of the medial arch, hind foot valgus and forefoot abduction. In the late stage, severe secondary osteoarthritis in upper and lower ankle joints occurs and impedes walking ability. The essential physical examination is supplemented by weight-bearing dorsoplantar and lateral radiographs, which provide further information about axial malalignment (Meary's angle, Kite's angle). The long axis hind foot view allows analysis of the hindfoot valgus. MRI provides further information about the integrity of the tibialis posterior tendon, spring ligament complex and cartilage damage.
Therapy:
The therapy aims to reduce pain, regain function and avoid development of secondary osteoarthritis and degenerative tendon disorders. Progress of the deformity should be stopped. Therefore, the main aspects of the deformity-loss of medial arch, hindfoot valgus and forefoot abduction should be addressed and corrected. In the acute phase, tendovaginitis of the tibialis posterior tendon can be treated sufficiently by anti-inflammatory measures, relieving mechanical loads on the tendon and muscle and physiotherapy.

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:10
Ankle Joint
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care