Related Experiment Video
Updated: Dec 5, 2025
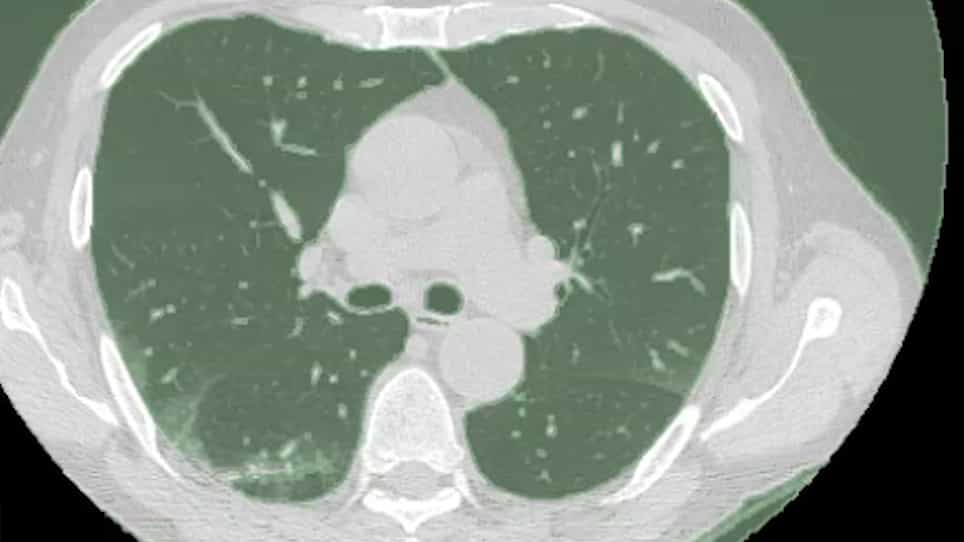

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Delayed Development of Coronary Artery Dilitation in Suspected Severe Acute Respiratory Syndrome Coronavirus 2
William B Orr1, Alexis M Elward2, John C Lin3
1Division of Cardiology, Department of Pediatrics, Washington University in St. Louis, St. Louis, MO.

Insights
Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection can cause multisystem inflammatory syndrome in children (MIS-C). This case highlights immune suppression, not hyperinflammation, and delayed coronary artery dilatation, urging further research into MIS-C pathogenesis.
Area of Science:
- Pediatric infectious diseases
- Immunology
- Cardiology
Background:
- Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection is linked to multisystem inflammatory syndrome in children (MIS-C), a condition previously thought to be driven by hyperinflammation.
- Understanding the immune system's role in MIS-C pathogenesis and its varied clinical presentations, including atypical Kawasaki-like disease, remains incomplete.
Observation:
- A 12-year-old male with SARS-CoV-2 serology (but negative RNA PCR) developed vasodilatory shock and myocardial depression.
- This patient presented with profound lymphopenia and elevated non-specific inflammatory markers (ferritin, C-reactive protein), but without significant elevations in specific inflammatory cytokines.
- Coronary artery dilatation was observed later in the disease course, following the resolution of myocardial depression.
Findings:
- This case of MIS-C demonstrated immune suppression rather than a hyperinflammatory state.
- The delayed onset of coronary artery dilatation contrasts with typical presentations described in other MIS-C case series.
Implications:
- The findings challenge the prevailing hypothesis of hyperinflammation in MIS-C pathogenesis.
- Further research is needed to understand the heterogeneous immune responses in MIS-C and the mechanisms leading to cardiac complications.
- This case underscores the need for a deeper mechanistic understanding to guide the development of targeted therapies for MIS-C and related Kawasaki-like conditions.
Abstract:
Although significant disease burden in the severe acute respiratory syndrome coronavirus 2 pandemic has been relatively uncommon in children, worldwide cases of a postinfectious multisystem inflammatory syndrome in children and possible atypical Kawasaki-like disease attributing to severe acute respiratory syndrome coronavirus 2 infection have arisen. Original thinking for coronavirus disease-19 disease was that an overwhelming proinflammatory response drove disease pathogenesis. Emerging reports suggest that a robust immune suppression may be more relevant and predominant. Recently reported data on children with multisystem inflammatory syndrome in children have demonstrated a heterogeneity of immune phenotypes among these patients, with concern for a strong initial proinflammatory state; however, data are lacking to support this. Likewise, understanding development of certain clinical findings to changes in the immune system is lacking.
Case Summary:
We report a 12-year-old multiracial male with negative coronavirus disease-19 nasopharyngeal RNA polymerase chain reaction testing but positive severe acute respiratory syndrome coronavirus 2 serology, subsequent development of vasodilatory shock with myocardial depression, and subsequent delayed development of coronary artery dilatation after resolution of myocardial depression. Unlike previous reported cases of multisystem inflammatory syndrome in children, he exhibited profound lymphopenia without specific inflammatory cytokines elevations, whereas nonspecific markers (ferritin and C-reactive protein) were increased. He subsequently was discharged on day 12 of hospitalization with complete recovery.
Conclusion:
Our representative case of a patient with coronavirus disease-19-associated multisystem inflammatory syndrome in children without robust hyperinflammation and a delayed finding of coronary artery dilatation compared with reported case series highlights the need for further mechanistic understanding of coronavirus disease-19 disease and subsequent multisystem inflammatory syndrome in children or Kawasaki disease development. This report offers a number of disease mechanisms and clinical evolution considerations for further elucidation to guide development of potential therapies.

Related Concept Videos
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:23
Rheumatic Heart Disease I: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care