Related Experiment Video
Updated: Dec 5, 2025
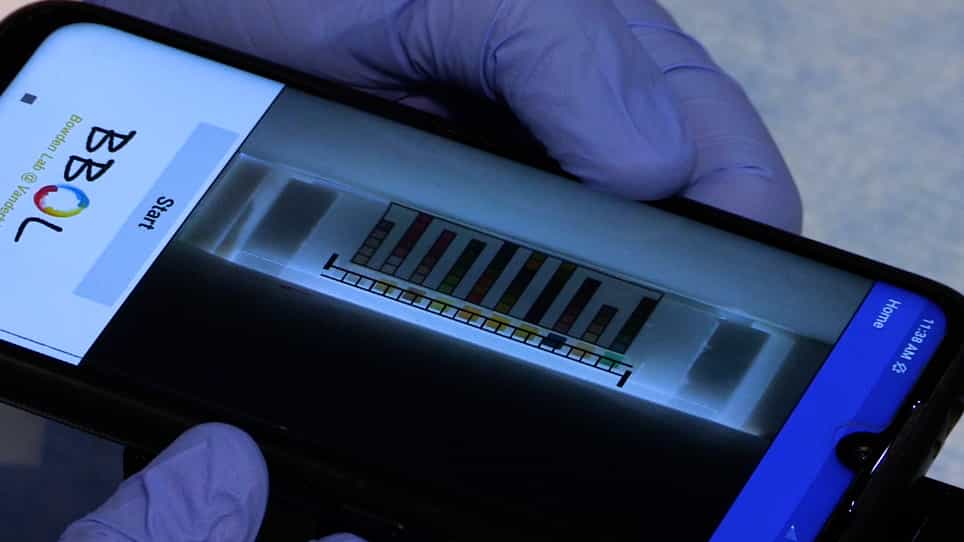

Low-Cost, Volume-Controlled Dipstick Urinalysis for Home-Testing
Published on: May 8, 2021
Urine dipsticks are not accurate for detecting mild ketosis during a severely energy restricted diet
Alice A Gibson1,2, Elif I Eroglu1, Kieron Rooney3
1Boden Collaboration for Obesity, Nutrition, Exercise and Eating Disorders, Faculty of Medicine and Health The University of Sydney Camperdown New South Wales Australia.

Background:
Detection of the mild ketosis induced by severely energy-restricted diets may be a clinically useful way to monitor and promote dietary adherence. Mild ketosis is often assessed using urine dipsticks, but accuracy for this purpose has not been tested.
Objective:
To determine the accuracy of urine dipsticks to detect mild ketosis during adherence to a severely energy-restricted diet.
Methods:
Two hundred and sixty three (263) fasting urine and 263 fasting blood samples were taken from 50 women (mean [standard deviation, SD] age 58.0 [4.3] years and body mass index 34.3 [2.4] kg/m2) before and at six time points during or for up to 10 weeks after 16 weeks of severe energy restriction, achieved with a total meal replacement diet. The amount of ketones (acetoacetate) in the urine was classified as '0 (Negative)', '+/- (Trace)', '+ (Weak)' or '++ (Medium)' by urine dipsticks (Ketostix, Bayer). The concentration of ketones (β-hydroxybutyrate) in the blood was measured with our reference method, a portable ketone monitor (FreeStyle Optium, Abbott). The diagnostic accuracy of the urine dipsticks was assessed from the percent of instances when a person was actually 'in ketosis' (as defined by a blood β-hydroxybutyrate concentration at or above three different thresholds) that were also identified by the urine dipsticks as being from a person in ketosis (the percent 'true positives' or sensitivity), as well as the percent of instances when a person was not in ketosis (as defined by the blood monitor result) was correctly identified as such with the urine dipstick (the percent 'true negatives' or specificity). Thresholds of ≥0.3mM, ≥0.5mM or ≥1.0mM were selected, because mean blood concentrations of β-hydroxybutyrate during ketogenic diets are approximately 0.5mM. Sensitivity and specificity were then used to generate receiver operating characteristic curves, with the area under these curves indicating the ability of the dipsticks to correctly identify people in ketosis (1 = perfect results, 0.5 = random results).
Results:
At threshold blood β-hydroxybutyrate concentrations of ≥0.3mM, ≥0.5mM and ≥1.0mM, the sensitivity of the urine dipsticks was 35%, 52% and 76%; the specificity was 100%, 97% and 78%; and the area under the receiver operating characteristic curves was 0.67, 0.74 and 0.77, respectively. These low levels of sensitivity mean that 65%, 48% or 24% of the instances when a person was in ketosis were not detected by the urine dipsticks.
Conclusion:
Urine dipsticks are not an accurate or clinically useful means of detecting mild ketosis in people undergoing a severely energy-restricted diet and should thus not be recommended in clinical treatment protocols. If monitoring of mild ketosis is indicated (eg, to monitor or help promote adherence to a severely energy-restricted diet), then blood monitors should be used instead.

Related Concept Videos
 01:29
Urine Studies I: Urinalysis
 01:26
Urine Studies II: Urine Culture and Sensitivity Test
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:24
Serum Studies: Renal Function Tests
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration