Related Experiment Video
Updated: Dec 5, 2025


Assessment of Glutamine as a Fuel Source for Alveolar Macrophages Exposed to Chronic Ethanol Using an Extracellular Flux Bioanalyzer
Published on: November 15, 2024
Efficacy of Granulocyte Colony Stimulating Factor in Severe Alcoholic Hepatitis: A Systematic Review and
Muhammad Baig1, Saqib Walayat1, Sonu Dhillon1
1Gastroenterology, OSF St. Francis Medical Center/University of Illinois College of Medicine at Peoria, Peoria, USA.

Background Severe alcoholic hepatitis is a condition with a very high mortality rate and there is a paucity of evidence regarding efficacy and safety of most available therapeutic options. The present systematic review and meta-analysis aims to assess the survival benefit of granulocyte colony stimulating factor (G-CSF) in patients with severe alcoholic hepatitis. Methods Studies involving adult patients receiving G-CSF for severe alcoholic hepatitis were searched in MEDLINE, Ovid journals, MEDLINE nonindexed citations, and Cochrane Central Register of Controlled Trials and Database of Systematic Reviews. Pooling was conducted by both fixed and random effects model. Results The initial search identified 543 reference articles; of these 24 relevant articles were selected and reviewed. Data was extracted from four studies (n = 136) which met the inclusion criteria. In the pooled analysis, the 90-day survival in the G-CSF group was 80.03% (95% CI = 69.93-88.49) compared to 40.92% (95% CI = 29.76-52.58) in the Standard Medical Therapy (SMT) group. At 28 days, the Model for End-Stage Liver Disease (MELD) score lowered by 4.89 (95% CI = 4.13-5.64) in the G-CSF group compared to 4.00 (95% CI = 3.25-4.75) in the SMT group. Child-Turcotte-Pugh score declined by 2.26 (95% CI = 1.90-2.63) in the G-CSF group after 28 days compared to 0.91 (95% CI = 0.59-1.23) in the SMT group. At 28 days, Maddrey Discriminant Function score lowered by 39.79 (95% CI = 34.22-45.36) in the G-CSF group compared to 12.39 (95% CI = 6.90-17.88) in the SMT group. Conclusions In patients with severe alcoholic hepatitis, G-CSF therapy resulted in significantly improved 90-day survival compared to SMT. It also demonstrated significant reduction in severity indices (Child-Turcotte-Pugh, MELD, and Maddrey discriminant function) after 28 days of treatment. There certainly is a need for further studies, including development of personalized therapeutic dosing schedules, for G-CSF administration.
Background Severe alcoholic hepatitis is a condition with a very high mortality rate and there is a paucity of evidence regarding efficacy and safety of most available therapeutic options. The present systematic review and meta-analysis aims to assess the survival benefit of granulocyte colony stimulating factor (G-CSF) in patients with severe alcoholic hepatitis. Methods Studies involving adult patients receiving G-CSF for severe alcoholic hepatitis were searched in MEDLINE, Ovid journals, MEDLINE nonindexed citations, and Cochrane Central Register of Controlled Trials and Database of Systematic Reviews. Pooling was conducted by both fixed and random effects model. Results The initial search identified 543 reference articles; of these 24 relevant articles were selected and reviewed. Data was extracted from four studies (n = 136) which met the inclusion criteria. In the pooled analysis, the 90-day survival in the G-CSF group was 80.03% (95% CI = 69.93-88.49) compared to 40.92% (95% CI = 29.76-52.58) in the Standard Medical Therapy (SMT) group. At 28 days, the Model for End-Stage Liver Disease (MELD) score lowered by 4.89 (95% CI = 4.13-5.64) in the G-CSF group compared to 4.00 (95% CI = 3.25-4.75) in the SMT group. Child-Turcotte-Pugh score declined by 2.26 (95% CI = 1.90-2.63) in the G-CSF group after 28 days compared to 0.91 (95% CI = 0.59-1.23) in the SMT group. At 28 days, Maddrey Discriminant Function score lowered by 39.79 (95% CI = 34.22-45.36) in the G-CSF group compared to 12.39 (95% CI = 6.90-17.88) in the SMT group. Conclusions In patients with severe alcoholic hepatitis, G-CSF therapy resulted in significantly improved 90-day survival compared to SMT. It also demonstrated significant reduction in severity indices (Child-Turcotte-Pugh, MELD, and Maddrey discriminant function) after 28 days of treatment. There certainly is a need for further studies, including development of personalized therapeutic dosing schedules, for G-CSF administration.


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:01
Regulation of Hematopoietic Stem Cells
 01:14
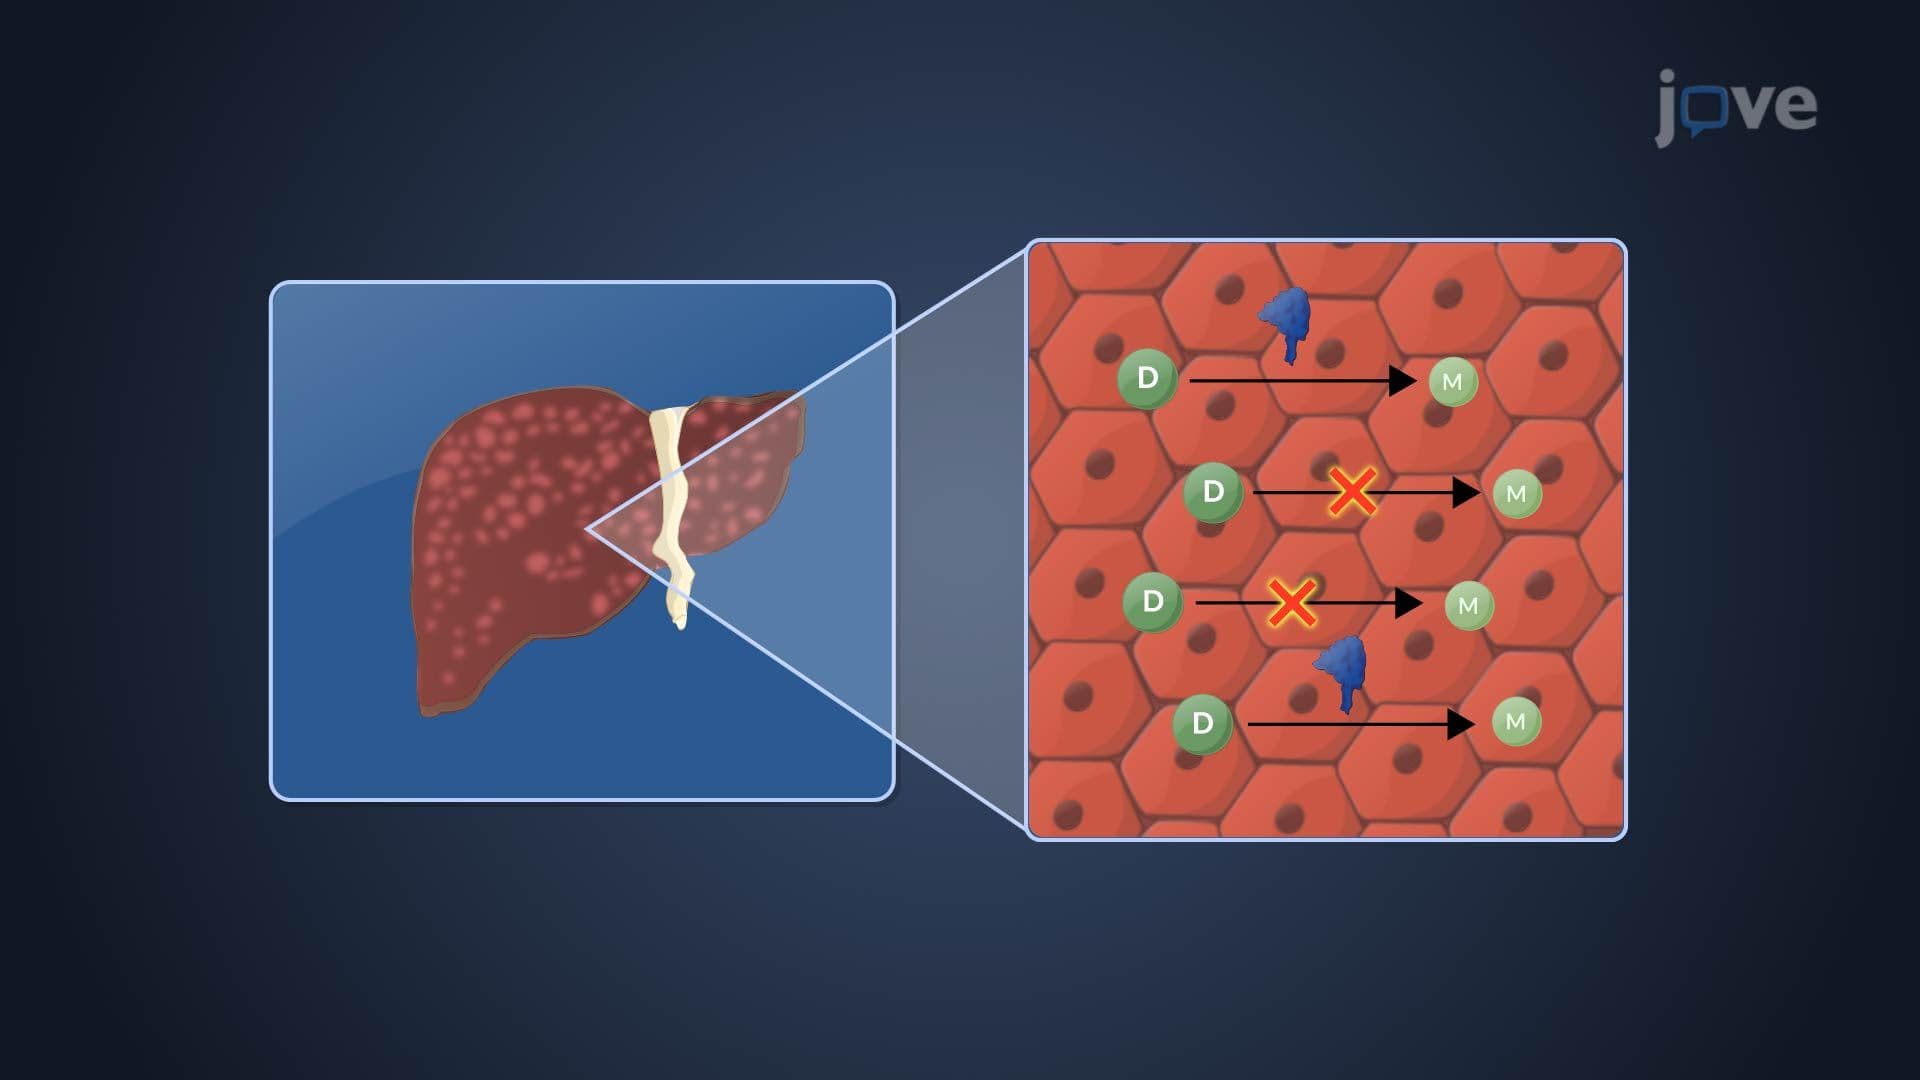
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug