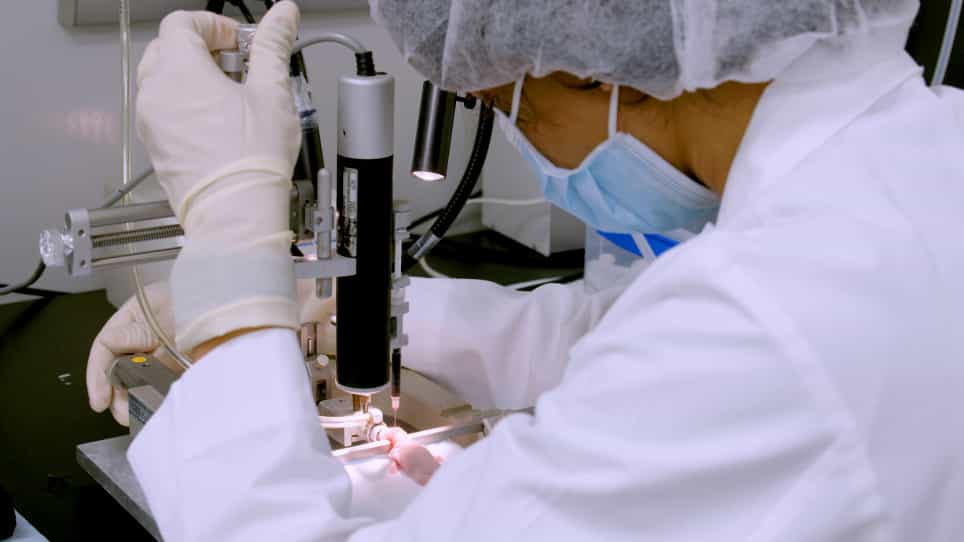
Related Experiment Video
Updated: Dec 4, 2025


Transcutaneous Microcirculatory Imaging in Preterm Neonates
Published on: December 31, 2015
Delayed cord clamping for prevention of intraventricular hemorrhage in preterm neonates: a randomized control trial
Fariba Hemmati1, Deepak Sharma2, Bahia Namavar Jahromi3
1Department of Pediatrics, School of Medicine, Neonatology Research Center, Shiraz University of Medical Sciences, Shiraz, Iran.

Insights
Delayed cord clamping (DCC) did not reduce overall intraventricular hemorrhage (IVH) in preterm neonates but significantly decreased severe IVH (grades II-IV). DCC also improved birth weight, hemoglobin levels, and reduced hospital stay without increasing risks.
Area of Science:
- Neonatal Medicine
- Perinatal Research
- Pediatric Neurology
Background:
- Intraventricular hemorrhage (IVH) is a frequent complication in preterm neonates, leading to significant adverse neurodevelopmental outcomes.
- Preventing IVH is crucial for improving neurological outcomes in this vulnerable population.
Purpose of the Study:
- To investigate if delayed cord clamping (DCC) is more effective than immediate cord clamping (ICC) in preventing IVH in preterm neonates.
- To compare the incidence and severity of IVH between DCC and ICC groups.
Main Methods:
- A prospective, double-blind, randomized controlled trial involving preterm neonates (26-34 weeks gestational age).
- Neonates were randomized to either ICC (10-15s) or DCC (30-45s).
- Cranial ultrasounds were performed on days 3-4 and 7-10 to assess IVH grading and severity.
Main Results:
- No significant difference in the overall incidence of any grade of IVH between ICC and DCC groups (12.8% vs. 14.5%).
- A significantly lower incidence of severe IVH (grades II, III, IV) was observed in the DCC group (1.4% vs. 10.1%).
- DCC was associated with increased birth weight, higher initial hemoglobin levels, and shorter hospital stays.
Conclusions:
- While DCC did not reduce all grades of IVH, it significantly decreased severe IVH in preterm neonates.
- Delayed cord clamping offers benefits including improved neonatal outcomes and reduced hospital stay without increasing risks like hyperbilirubinemia or mortality.
Background:
Intraventricular hemorrhage (IVH) is a common condition in preterm neonates and is responsible for substantial adverse neurodevelopmental outcome in preterm neonates. Prevention of IVH is an important intervention for better neurological outcome in these preterm neonates.
Aims And Objective:
This study aimed to determine whether delayed cord clamping (DCC) was superior to immediate cord clamping (ICC) for the prevention of IVH in preterm neonates.
Patients And Methods:
In this two centered prospective double-blind randomized controlled trial, eligible neonates with gestational age from 26 to 34 weeks were randomized to receive either ICC (cord clamped in 10-15 s) or DCC (cord clamped in 30-45 s) groups. The grading and severity of IVH were evaluated by cranial ultrasound scan done on the 3-4th and 7-10th days after birth.
Results:
Among the 148 enrolled neonates, 79 were in the ICC group and 69 were in the DCC group. There was no difference in maternal and neonatal baseline characteristics except the neonates in the DCC group weighed more (ICC 1528.77 ± 365.5 g vs. DCC 1658.11 ± 419.52 g; p = .047) at birth. There was no significant difference in the incidence of any grade of IVH in both groups (ICC 12.8% vs. DCC 14.5%; p = .745). There was a significantly higher incidence of grade I IVH (ICC 2.5% vs. DCC 13%; p = .024) in the DCC group. The incidence of grade II IVH (ICC 5.1% vs. DCC 0%; p = .123); grade III IVH (ICC 3.8% vs. DCC 1.4%; p = .623); and grade IV IVH (ICC 1.3% vs. DCC 0%; p>.999) were comparable between the two groups. The incidence of a significant IVH (grades II, III, and IV) was significantly less in the DCC group (ICC 10.1% vs. DCC 1.4%, p = .036). The mean initial hemoglobin levels were significantly higher in neonates enrolled in DCC (15.41 ± 2.1 vs. 16.46 ± 2.45 g/dL; p = .007). There was a significant reduction in the number of days of hospital stay (ICC 18.78 ± 15.42 vs. DCC 13.21 ± 16.16; p = .002). There was no difference in initial hematocrit, platelet count, maximum bilirubin level, and Apgar score (p>.05).
Conclusions:
Although there was no reduction in any grade of IVH, the incidence of significant IVH (grades II, III, and IV) was significantly decreased with the use of DCC in preterm neonates. Delayed cord clamping also resulted in a significant increase in birth weight, higher hemoglobin levels, and shorter hospital stays without any increase in the risks of hyper-bilirubinemia, low Apgar score, and neonatal mortality.
Trial Registry:
IRCT2014031116936N1, https://www.irct.ir/trial/15707.