Related Experiment Video
Updated: Dec 3, 2025


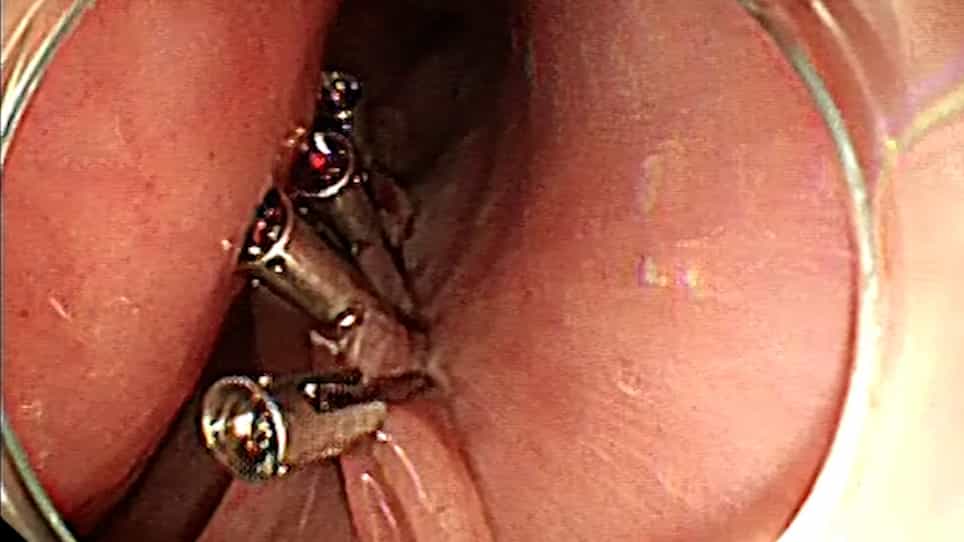
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Variation in exposure to endoscopic haemostasis for acute upper gastrointestinal bleeding during UK gastroenterology
Keith Siau1,2, A John Morris1,3, Aravinth Murugananthan1,4
1Joint Advisory Group on Gastrointestinal Endoscopy, Royal College of Physicians, London, UK.

Introduction:
Gastroenterologists are typically expected to be competent in endoscopic haemostasis for acute upper gastrointestinal bleeding (AUGIB), with the Certificate of Completion of Training (CCT) often heralding the onset of participation in on-call AUGIB rotas. We analysed the volume of haemostasis experience recorded by gastroenterology CCT holders on the Joint Advisory Group on Gastrointestinal Endoscopy Training System (JETS) e-portfolio, the UK electronic portfolio for endoscopy, and assessed for variations in exposure to haemostasis.
Methods:
UK gastroenterologists awarded CCT between April 2014 and April 2017 were retrospectively identified from the specialist register. Credentials were cross-referenced with JETS to retrieve AUGIB haemostasis procedures prior to CCT. Procedures were collated according to variceal versus non-variceal therapies and compared across training deaneries.
Results:
Over the 3-year study period, 241 gastroenterologists were awarded CCT. 232 JETS e-portfolio users were included for analysis. In total, 12 932 haemostasis procedures were recorded, corresponding to a median of 42 (IQR 21-71) per gastroenterologist. Exposure to non-variceal modalities (median 28, IQR 15-52) was more frequent than variceal therapies (median 11, IQR 5-22; p<0.001). By procedure, adrenaline injection (median 12, IQR 6-23) and variceal band ligation (median 10, IQR 5-20) were most commonly recorded, whereas sclerotherapy experience was rare (median 0, IQR 0-1). Exposure to haemostasis did not differ by year of CCT (p=0.130) but varied significantly by deanery (p<0.001), with median procedures ranging from 20-126.
Conclusion:
Exposure to AUGIB haemostasis during UK gastroenterology training varied across deaneries and procedural modalities which should prompt urgent locoregional review of access and delivery of training. Endoscopy departments should ensure the availability of supportive provisions in haemostasis (i.e. training/upskilling, supervision, mentorship) during the early post-CCT period.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:24
Esophageal Varices-I: Introduction
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.