Related Experiment Video
Updated: Dec 3, 2025


Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Clinicopathologic Features and Diagnostic Implications of Pyloric Gland Metaplasia in Intestinal Specimens
Minami Tokuyama1, Sadhna Dhingra, Alexandros D Polydorides
1Department of Pathology, Molecular, and Cell Based Medicine, Icahn School of Medicine at Mount Sinai, New York, NY.

Abstract:
Pyloric gland metaplasia (PGM) is a histopathologic change usually seen after inflammatory injury and, although described in association with inflammatory bowel disease (IBD) and particularly Crohn disease (CD), its significance is still debated. We evaluated long-term correlates of PGM in a large cohort of 601 intestinal specimens, 227 (37.8%) biopsies, and 374 (62.2%) resections, from 567 different patients, 328 (57.8%) male and 239 (42.2%) female, with a mean age of 43.4±15.8 years. During mean clinical follow-up of 83.5±48.1 months, 511 (90.1%) patients were diagnosed with IBD, 457 (89.4%) with CD, and 53 (10.4%) with ulcerative colitis. In multivariate analysis, IBD patients with PGM were younger (P<0.001) and more often had severely active inflammation (P=0.002) compared with non-IBD patients, whereas, among IBD patients, those with ulcerative colitis were more likely to have PGM in a biopsy (P<0.001) or in the colorectum (P=0.009), compared with CD patients. Kaplan-Meier analyses showed that incidental PGM in a biopsy was more likely to predict IBD in patients younger than 50 years (P<0.001) and those without a history of bowel surgery (P<0.001) and also more likely to signify CD in patients younger than 50 years (P=0.004), those without a history of bowel surgery (P=0.020), and when identified in the small intestine (P=0.032). In conclusion, intestinal PGM warrants a high suspicion for IBD and specifically CD, however, it should be interpreted with caution, especially in older patients or those with a history of prior intestinal surgery and in colorectal biopsies or specimens lacking severely active inflammation.
Insights
Pyloric gland metaplasia (PGM) may indicate inflammatory bowel disease (IBD), especially Crohn disease (CD), in younger patients without prior surgery. However, PGM findings require careful interpretation in older patients or those with a history of intestinal surgery.
Area of Science:
- Gastroenterology
- Histopathology
- Inflammatory Bowel Disease Research
Background:
- Pyloric gland metaplasia (PGM) is a recognized histopathologic change following inflammatory injury.
- Its association with inflammatory bowel disease (IBD), particularly Crohn disease (CD), is documented but its clinical significance remains debated.
Purpose of the Study:
- To evaluate the long-term clinical correlates of PGM in a large cohort of intestinal specimens.
- To determine the predictive value of PGM for IBD and specific subtypes like CD and ulcerative colitis (UC).
Main Methods:
- Analysis of 601 intestinal specimens (biopsies and resections) from 567 patients.
- Multivariate analysis and Kaplan-Meier survival analyses were employed.
- Clinical data and follow-up information up to 83.5 months were assessed.
Main Results:
- PGM was associated with younger age and more severe inflammation in IBD patients.
- Ulcerative colitis patients were more likely to have PGM in biopsies or colorectal specimens compared to CD patients.
- Incidental PGM predicted IBD and CD in patients under 50 without prior bowel surgery, and when found in the small intestine.
Conclusions:
- Intestinal PGM should raise suspicion for IBD, particularly CD.
- Interpretation of PGM requires caution in older patients, those with prior intestinal surgery, and in colorectal biopsies or specimens lacking severe inflammation.


Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:27
Histology of the Small Intestine
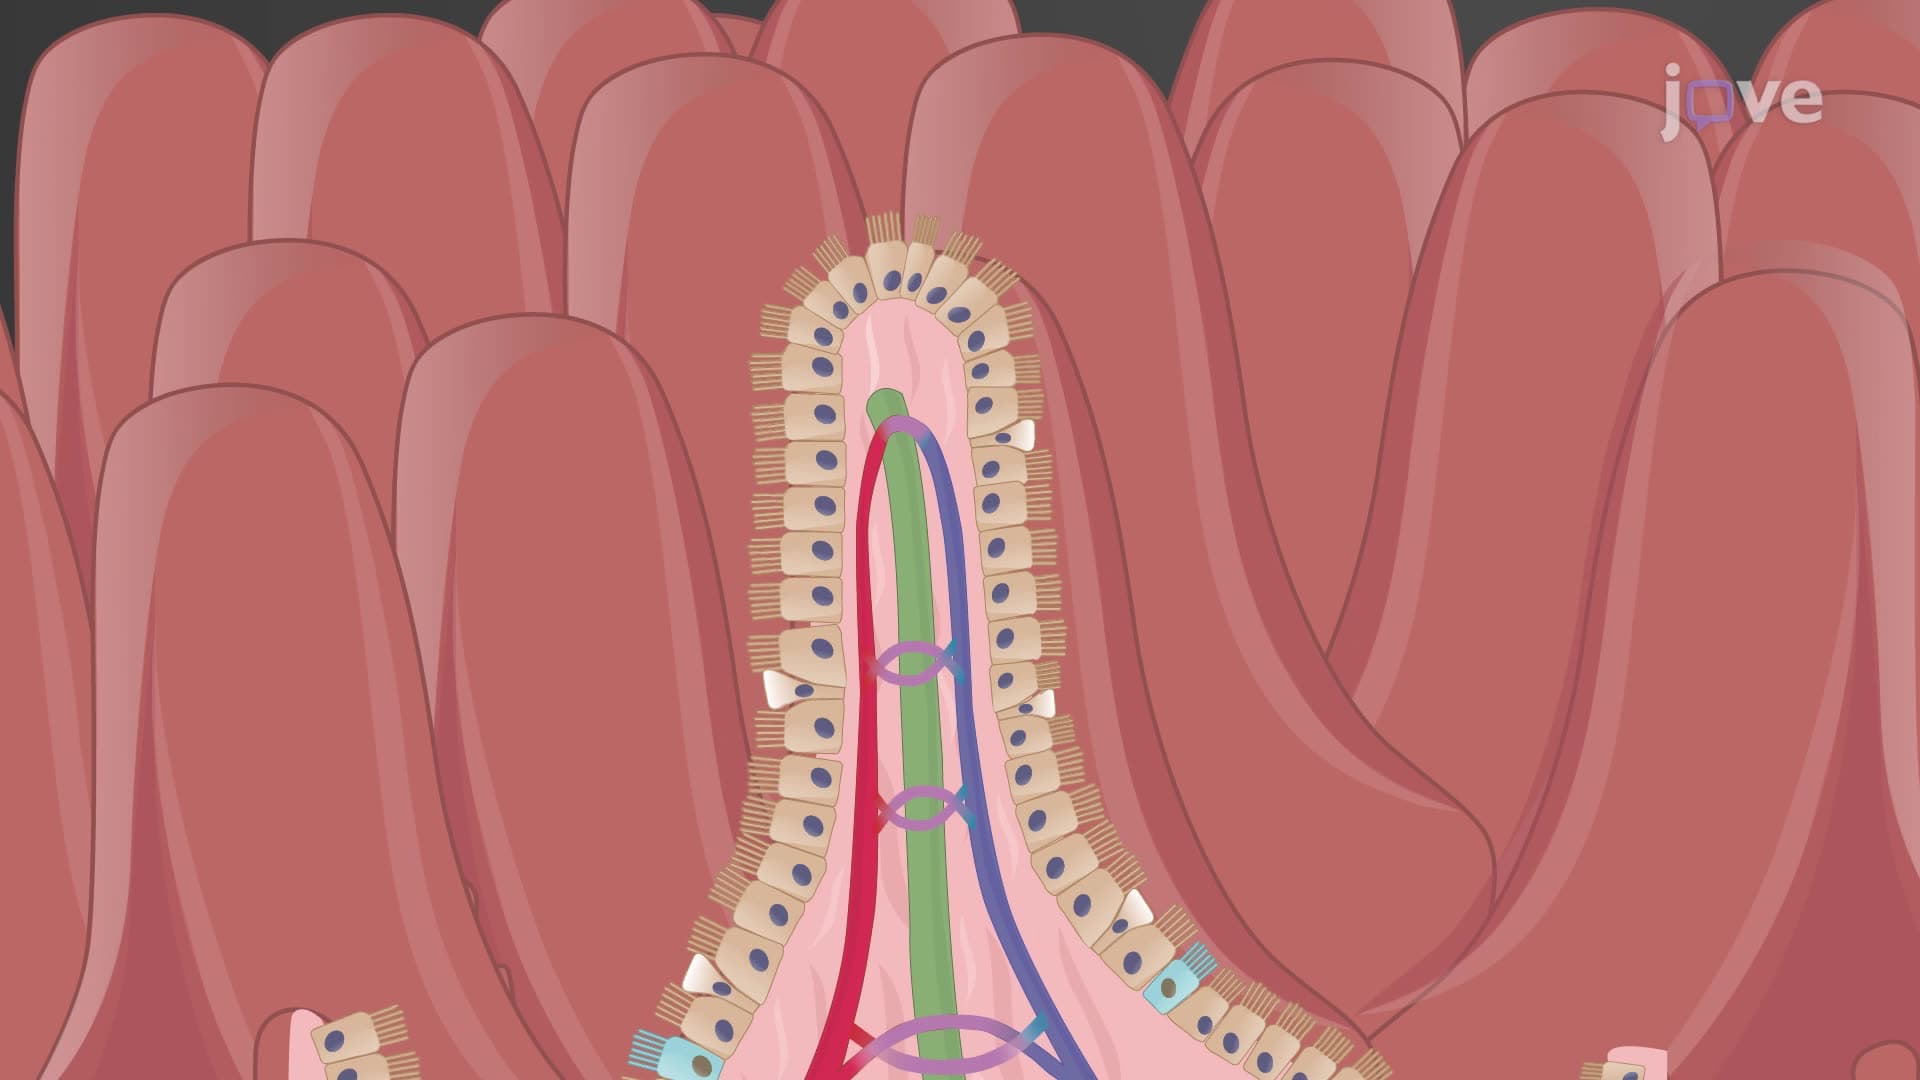
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...