Orthostatic retractor placement reduces operating time and post-operative inflammatory response during the learning
Gert-Jan Opsomer1, Frans-Jozef Vandeputte1, Cigdem Sarac1
1Department of Orthopaedic Surgery, Ziekenhuis Oost-Limburg, Genk, Belgium.

Introduction:
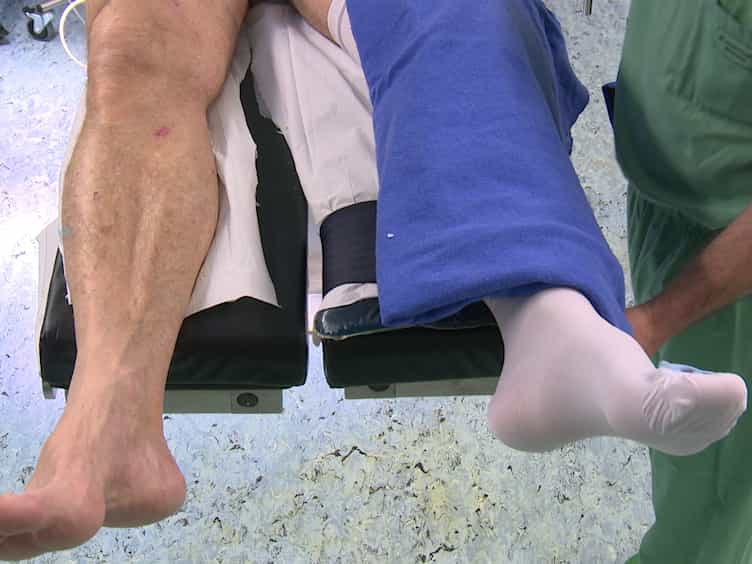
Handheld retractor placement (HHRP) is prone to repetitive repositioning. This could lead to muscle damage especially during a procedure with a steep learning curve. In an attempt to minimize retractor repositioning during the learning curve of direct anterior approach (DAA) total hip arthroplasty (THA), we used a table mounted orthostatic retractor placement (ORP) device.
Purpose:
To investigate whether ORP would reduce the extent of muscle damage, OR-time and post-operative inflammatory response.
Materials And Methods:
29 Patients were operated by 2 surgeons who randomly used HHRP or ORP during their learning curve of DAA THA. There were 14 patients in a control group who were operated by an experienced surgeon. Blood levels of Creatine Kinase (CK), C-Reactive Protein (CRP), Hemoglobin (Hb), Lactate Dehydrogenase (LDH) and Erythrocyte Sedimentation Rate (ESR) were measured at 1 h pre- and 24 and 48 h post-operatively.
Results:
The mean OR-time was 67 and 50 min in the HHRP and ORP cohort, respectively (p < 0,001). Post-operative CRP levels were significantly higher in the HHRP cohort at 24 h (HHRP 60.64 mg/L (25.20-143.20); ORP 34.67 mg/L (9.30-71.20)) (p = 0.003) and 48 h post-operatively (HHRP 154.54 mg/L (65.90-369.00); ORP 81.60 mg/L (21.30-219.40) (p = 0.004). The post-operative Hb-levels were significantly lower in the HHRP cohort at 24 h (HHRP 11.11 g/dL (9.10-12.30); ORP 11.37 g/dL (8.80-14.00)) (p = 0.0008) and 48 h (HHRP 10.86 g/dL (9.50-12.00); ORP 11.25 g/dL (8.60-14.10)) (p = 0.03). Post-operative ESR levels were significantly higher in the HHRP cohort 48 h post-op (HHRP 45.21 mm/h (14.00-83.00); ORP 23.73 mm/h (2.00-73.00)) (p = 0.004). No significant differences were found for the CK and LDH levels at any time postoperatively. There were no complications in any group.
Conclusion:
The use of an orthostatic retractor placement device allows for reducing the OR-time, post-operative blood loss and post-operative inflammatory response during the learning curve of DAA THA.