Related Experiment Video
Updated: Dec 2, 2025


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Type IV RTA in Chronic Adrenal Insufficiency and Concomitant Lisinopril Treatment
1Department of Medicine, University of Pittsburgh Medical Center, 200 Lothrop Street, Suite N715, Pittsburgh, PA 15213, USA.

Abstract:
Type IV renal tubular acidosis (RTA) is the only RTA characterized by hyperkalemia, and it is caused by a true aldosterone deficiency or renal tubular aldosterone hyporesponsiveness. It is frequent among hospitalized patients as it is related to type 2 diabetes mellitus (T2DM) and common medications such as ACE-inhibitors (ACE-is) and trimethoprim-sulfamethoxazole (TMP-SMX). Drug-induced RTA commonly manifests in patients with predisposing conditions such as mild renal insufficiency and certain pharmacological therapies. ACE-i use and chronic adrenal insufficiency (cAI) are other significant risk factors. Chronic ACTH suppression is thought to induce global adrenal atrophy, including the zona glomerulosa, thus affecting aldosterone secretion as well. Furthermore, in the setting of cAI, treatment with ACE-is further suppresses aldosterone production. This case report describes a patient with cAI secondary to corticosteroid use for years who developed type IV RTA in the setting of lisinopril use. Potassium (K) elevation persisted despite removing underlying conditions and metabolic acidosis correction. The patient required long-term treatment with mineralocorticoids in addition to sodium bicarbonate to maintain normal K levels and acid-base status. Mineralocorticoid administration is a second-line treatment for type IV RTA, but it might be necessary for a subgroup of high-risk patients. In fact, it is important to consider patients with chronic adrenal insufficiency and on ACE-is treatment at increased risk for refractory hyperkalemia in the setting of type IV RTA. Indeed, this subgroup of patients can have severe hypoaldosteronism.
More Related Videos


Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
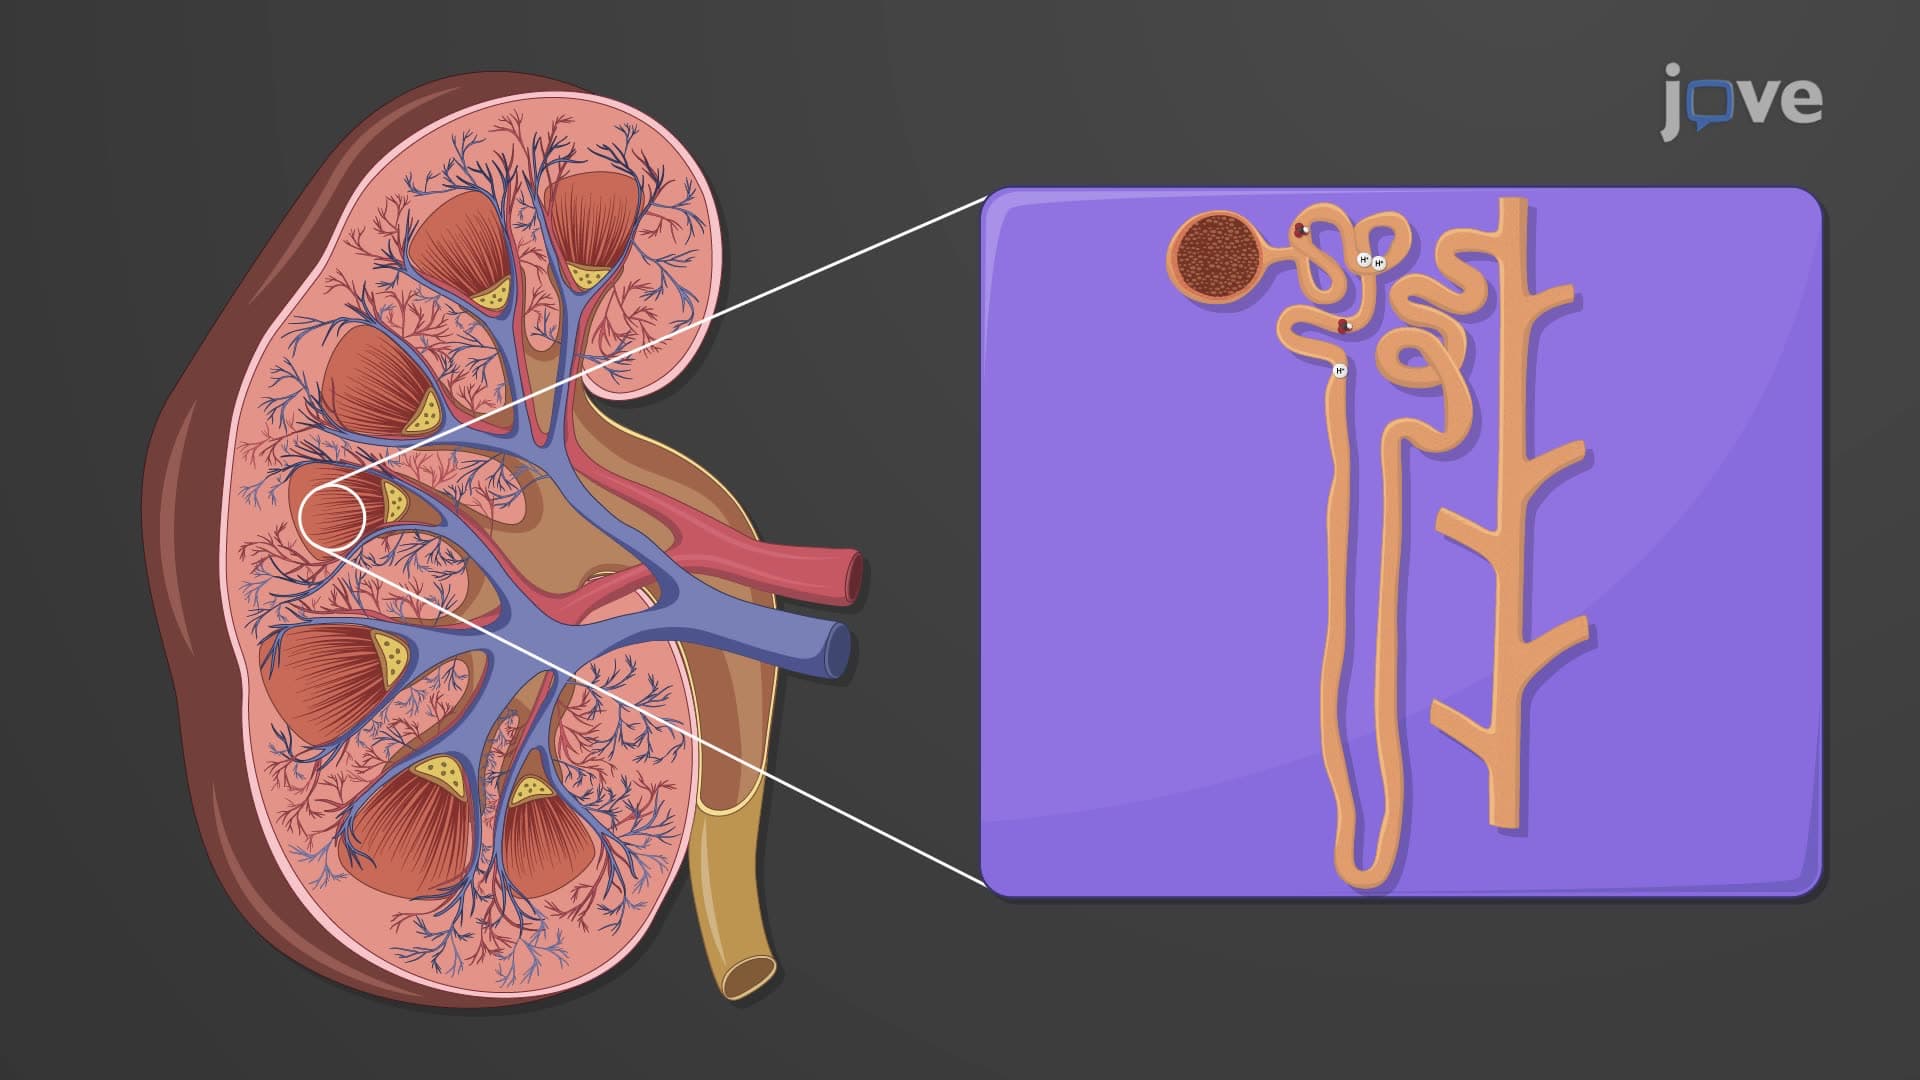
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Acute Kidney Injury II: Pathophysiology