Related Experiment Video
Updated: Dec 2, 2025


A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
Long-term IV access in paediatrics - why, what, where, who and how
Mathias Johansen1, Volker Classen2, Karl Muchantef3
1Department of Paediatric Anaesthesia, Montreal Children's Hospital, Montreal, Canada.

Insights
This review covers central venous access devices (CVADs) for children, detailing risks, complications like infections and thrombosis, and optimal management strategies. It also presents a specific technique for inserting tunnelled, cuffed catheters.
Area of Science:
- Pediatric Medicine
- Vascular Surgery
- Medical Devices
Background:
- Long-term central venous access in children carries risks including procedural complications and catheter-related issues.
- Complications encompass air embolism, pneumothorax, infections, thrombosis, and stenosis, impacting pediatric patient morbidity and mortality.
- Syndromic children often present unique anesthetic challenges for central venous access device (CVAD) placement.
Purpose of the Study:
- To provide a historical and clinical overview of central venous access devices (CVADs) in pediatric long-term use.
- To detail the origin and management of common CVAD complications, including thrombosis, infections, and occlusion.
- To update clinicians on the indications, methods, and patient selection for pediatric long-term central venous access.
Main Methods:
- This narrative review synthesizes existing literature on pediatric central venous access.
- It examines the development, application, and complications of central venous access devices (CVADs).
- A specific clinical method for retrograde insertion of a tunnelled and cuffed catheter via the left brachiocephalic vein is presented.
Main Results:
- Central venous access devices (CVADs) are essential but associated with significant procedural and catheter-related risks.
- Common complications include catheter-related bloodstream infections, thrombosis, and occlusion, requiring careful management.
- The review highlights the importance of appropriate patient selection and technique for successful pediatric CVAD placement.
Conclusions:
- Effective management of pediatric central venous access requires understanding historical context, potential complications, and current best practices.
- The presented technique offers a specific approach for tunnelled and cuffed catheter insertion in pediatric patients.
- Optimizing central venous access in children necessitates a comprehensive approach to minimize risks and ensure device longevity.
Abstract:
Establishment of long-term central venous access imposes the risk of procedural adverse events (air embolism, pneumothorax, accidental arterial cannulation of the great vessels, tricuspid valve damage and cardiac tamponade) as well as the risk of increased morbidity and mortality due to catheter related blood stream infections, vessel stenosis, deep vein thrombosis and the often high risk anaesthetic management of syndromic children. This narrative review aims to provide a historical and clinical background for the development and use of CVADs (central venous access devices), origin and management of the most common complications (catheter related thrombosis, infections and persistent withdrawal occlusion) and present the reader with an update on the "why, what, where, who and how" in paediatric long-term central venous access. Finally, we will present the reader with a clinical method for applying a retrograde inserted tunnelled and cuffed catheter using the left brachiocephalic vein access.
More Related Videos
Related Concept Videos
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:25
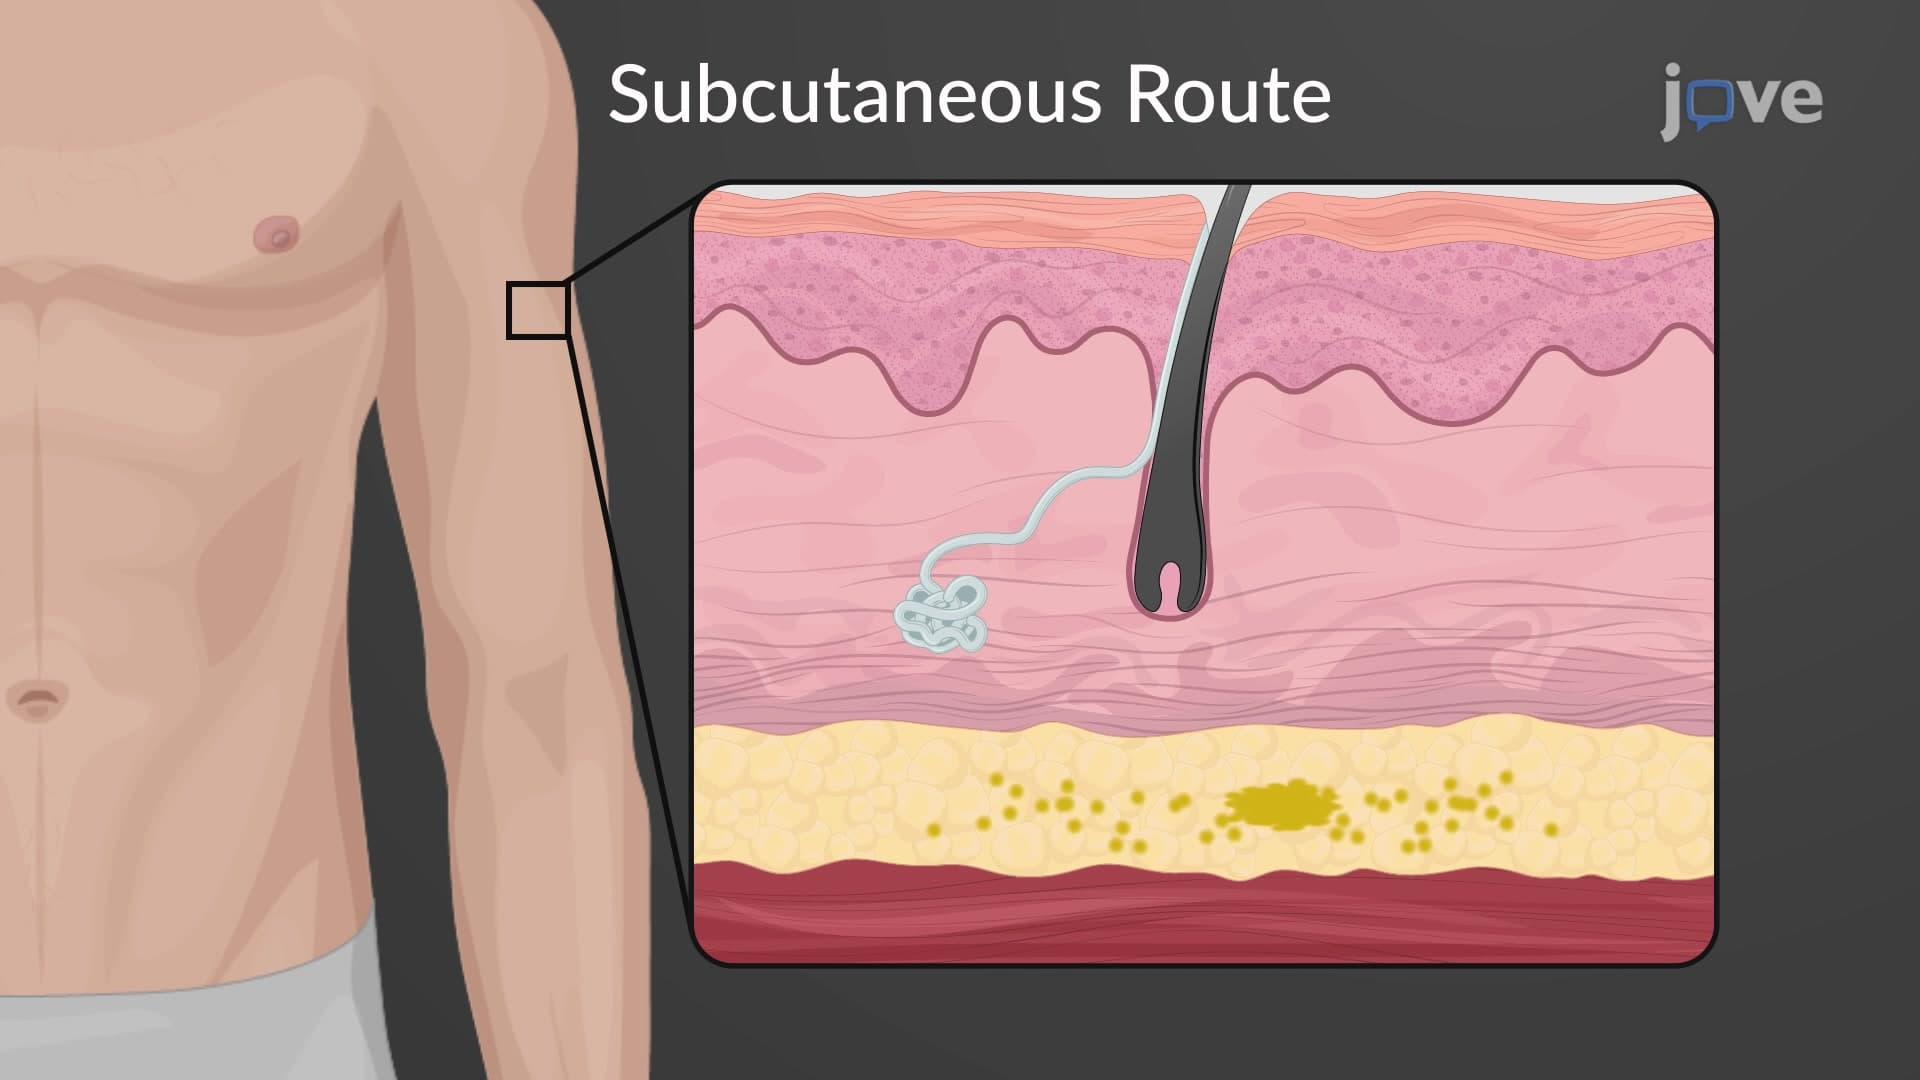
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption