Related Experiment Video
Updated: Dec 1, 2025


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
First-Dose Vancomycin Pharmacokinetics Versus Empiric Dosing on Area-Under-the-Curve Target Attainment in Critically
Alexander H Flannery1,2, Natalie L Delozier1,2, Samuel A Effoe1,2
1Department of Pharmacy Practice and Science, University of Kentucky College of Pharmacy, Lexington, Kentucky, USA.

Background:
Early attainment of target area under the curve (AUC) to minimum inhibitory concentration (MIC) ratios have been associated with clinical success, as well as lower incidence of acute kidney injury (AKI), in patients receiving vancomycin for methicillin-resistant Staphylococcus aureus (MRSA). Critically ill patients are particularly vulnerable to poor outcomes from infection and face multiple risk factors for AKI, thus early precision dosing of vancomycin is vital in this population. We hypothesized that a personalized dosing approach, using vancomycin levels obtained after the first dose to guide further dosing, would be superior to empiric dosing in terms of AUC target attainment assessed at steady state (SS).
Methods:
A retrospective cohort study of 66 critically ill adult patients admitted to the medical intensive care unit without AKI and receiving vancomycin with at least two SS concentrations obtained for AUC calculation was performed. Patients were separated into cohorts based on whether they had two concentrations assessed after the first dose of vancomycin and were subsequently dosed based on personalized pharmacokinetic calculations (first-dose kinetics) or whether they were empirically dosed using population estimates. The primary outcome was AUC target attainment (400-600 mg hour/L) at SS.
Results:
Compared with patients receiving empiric dosing by population estimates, using first-dose kinetics to guide subsequent dosing resulted in significantly greater AUC target attainment at SS (58.6% first-dose vs 32.4% empiric; p=0.033). Patients dosed empirically yielded more variable AUC values across a wide range compared with the first-dose kinetics group (coefficient of variation 40.7% empiric vs 26.1% first-dose). There was no difference in AKI up to 48 hours after SS concentrations between the two dosing schemes.
Conclusions:
A dosing strategy using two vancomycin serum concentrations after the first dose and calculating personalized pharmacokinetic parameters to guide subsequent dosing is associated with greater AUC target attainment at SS compared with empiric dosing of vancomycin in critically ill adults with relatively stable renal function.
Insights
Personalized vancomycin dosing using first-dose levels significantly improved target AUC attainment in critically ill patients compared to standard empiric dosing. This precision approach enhances treatment efficacy for methicillin-resistant Staphylococcus aureus infections.
Area of Science:
- Pharmacokinetics and Pharmacodynamics
- Infectious Diseases
- Critical Care Medicine
Background:
- Early achievement of vancomycin area under the curve (AUC) to minimum inhibitory concentration (MIC) ratios is linked to clinical success and reduced acute kidney injury (AKI) in methicillin-resistant Staphylococcus aureus (MRSA) infections.
- Critically ill patients face higher risks for poor infection outcomes and AKI, necessitating precise vancomycin dosing.
- This study investigated if personalized dosing based on early vancomycin levels improves AUC target attainment at steady state (SS).
Purpose of the Study:
- To evaluate the efficacy of a personalized vancomycin dosing strategy in critically ill adults.
- To compare AUC target attainment between first-dose kinetics-guided dosing and empiric dosing.
- To assess the impact of personalized dosing on clinical outcomes and AKI incidence.
Main Methods:
- A retrospective cohort study involving 66 critically ill adults without AKI receiving vancomycin.
- Patients were divided into two groups: those dosed using first-dose pharmacokinetic calculations and those receiving empiric dosing based on population estimates.
- The primary outcome was achieving target AUC (400-600 mg*hour/L) at steady state, with at least two SS concentrations measured for calculation.
Main Results:
- First-dose kinetics dosing led to significantly higher AUC target attainment at SS (58.6%) compared to empiric dosing (32.4%; p=0.033).
- The empiric dosing group exhibited more variable AUC values (coefficient of variation 40.7%) than the first-dose kinetics group (26.1%).
- No significant difference in AKI incidence was observed between the two dosing strategies within 48 hours of SS concentration assessment.
Conclusions:
- Personalized vancomycin dosing, guided by serum concentrations after the first dose, enhances AUC target attainment at SS in critically ill adults with stable renal function.
- This precision dosing strategy offers a superior alternative to empiric vancomycin dosing for achieving therapeutic targets.
- Early pharmacokinetic assessment can optimize vancomycin therapy in vulnerable patient populations.
Related Concept Videos
 01:20
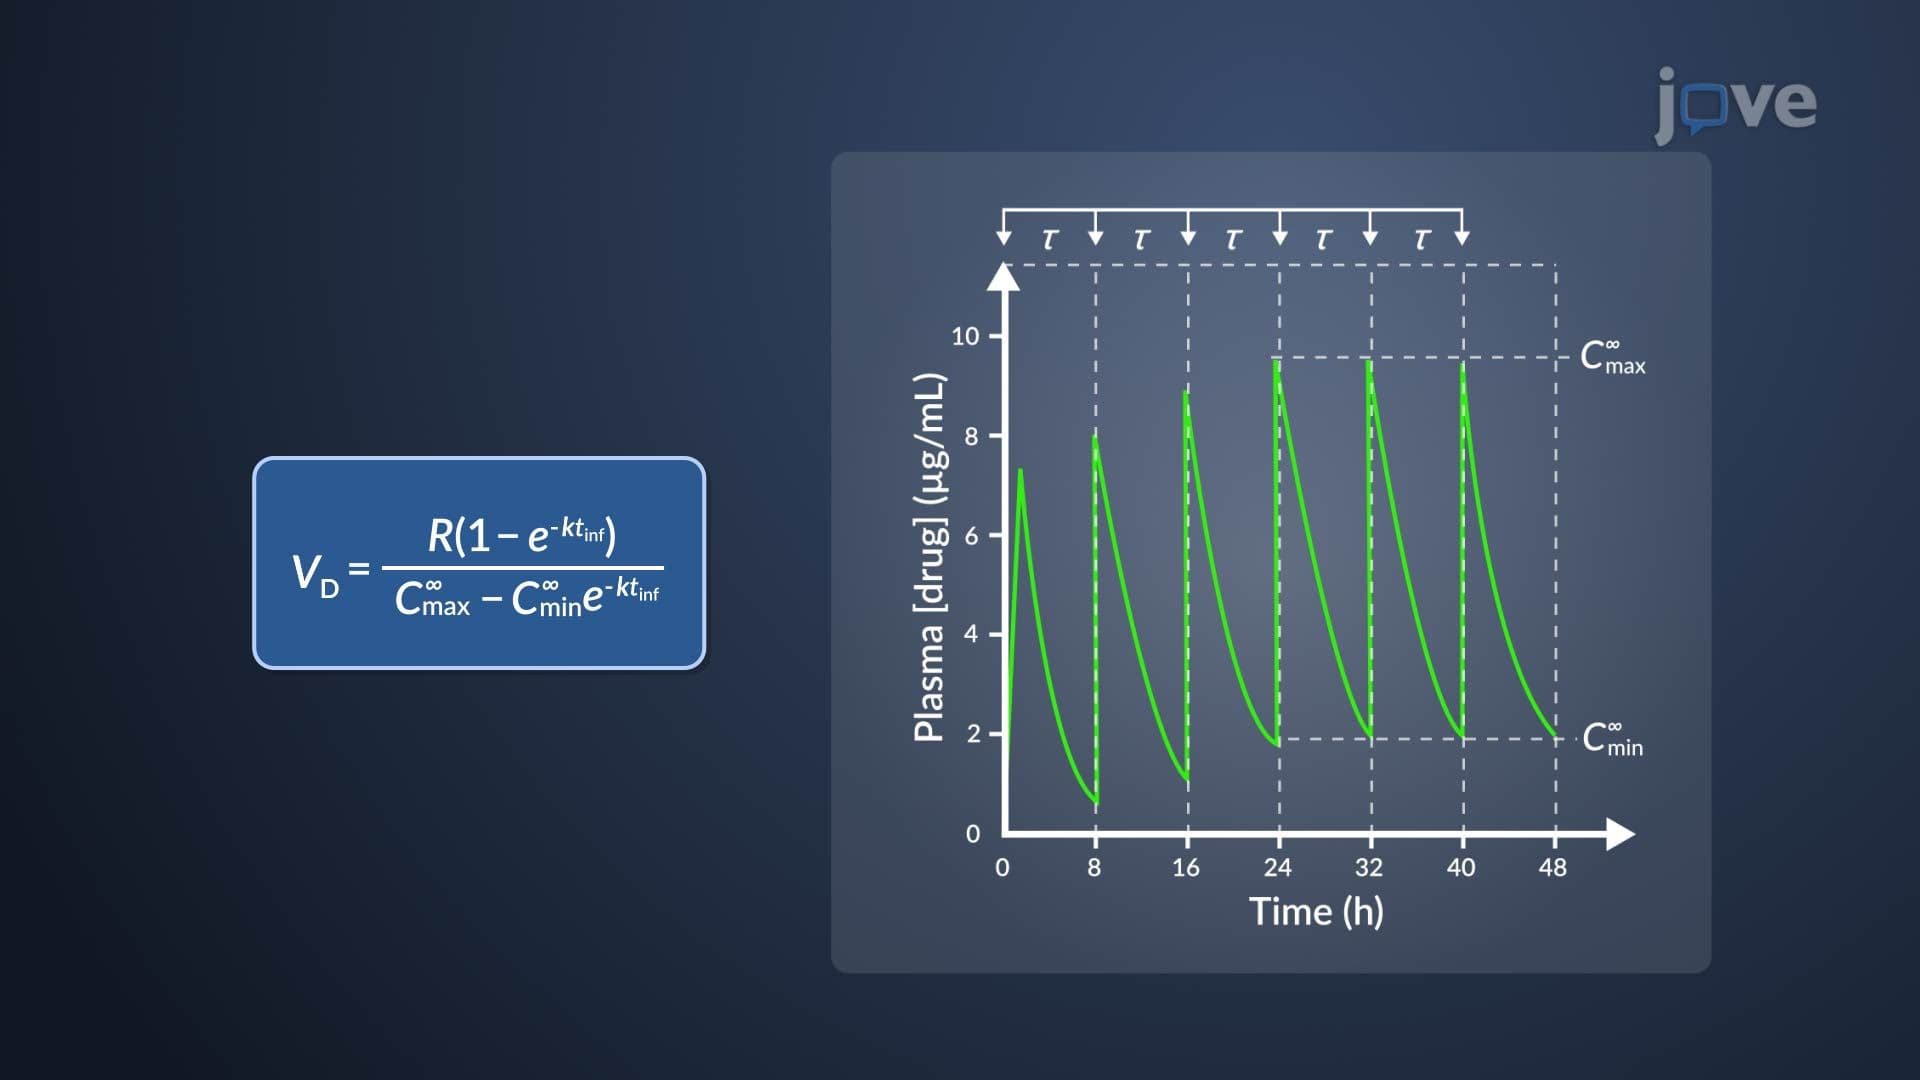
Estimation of k and VD of Aminoglycosides
 01:15
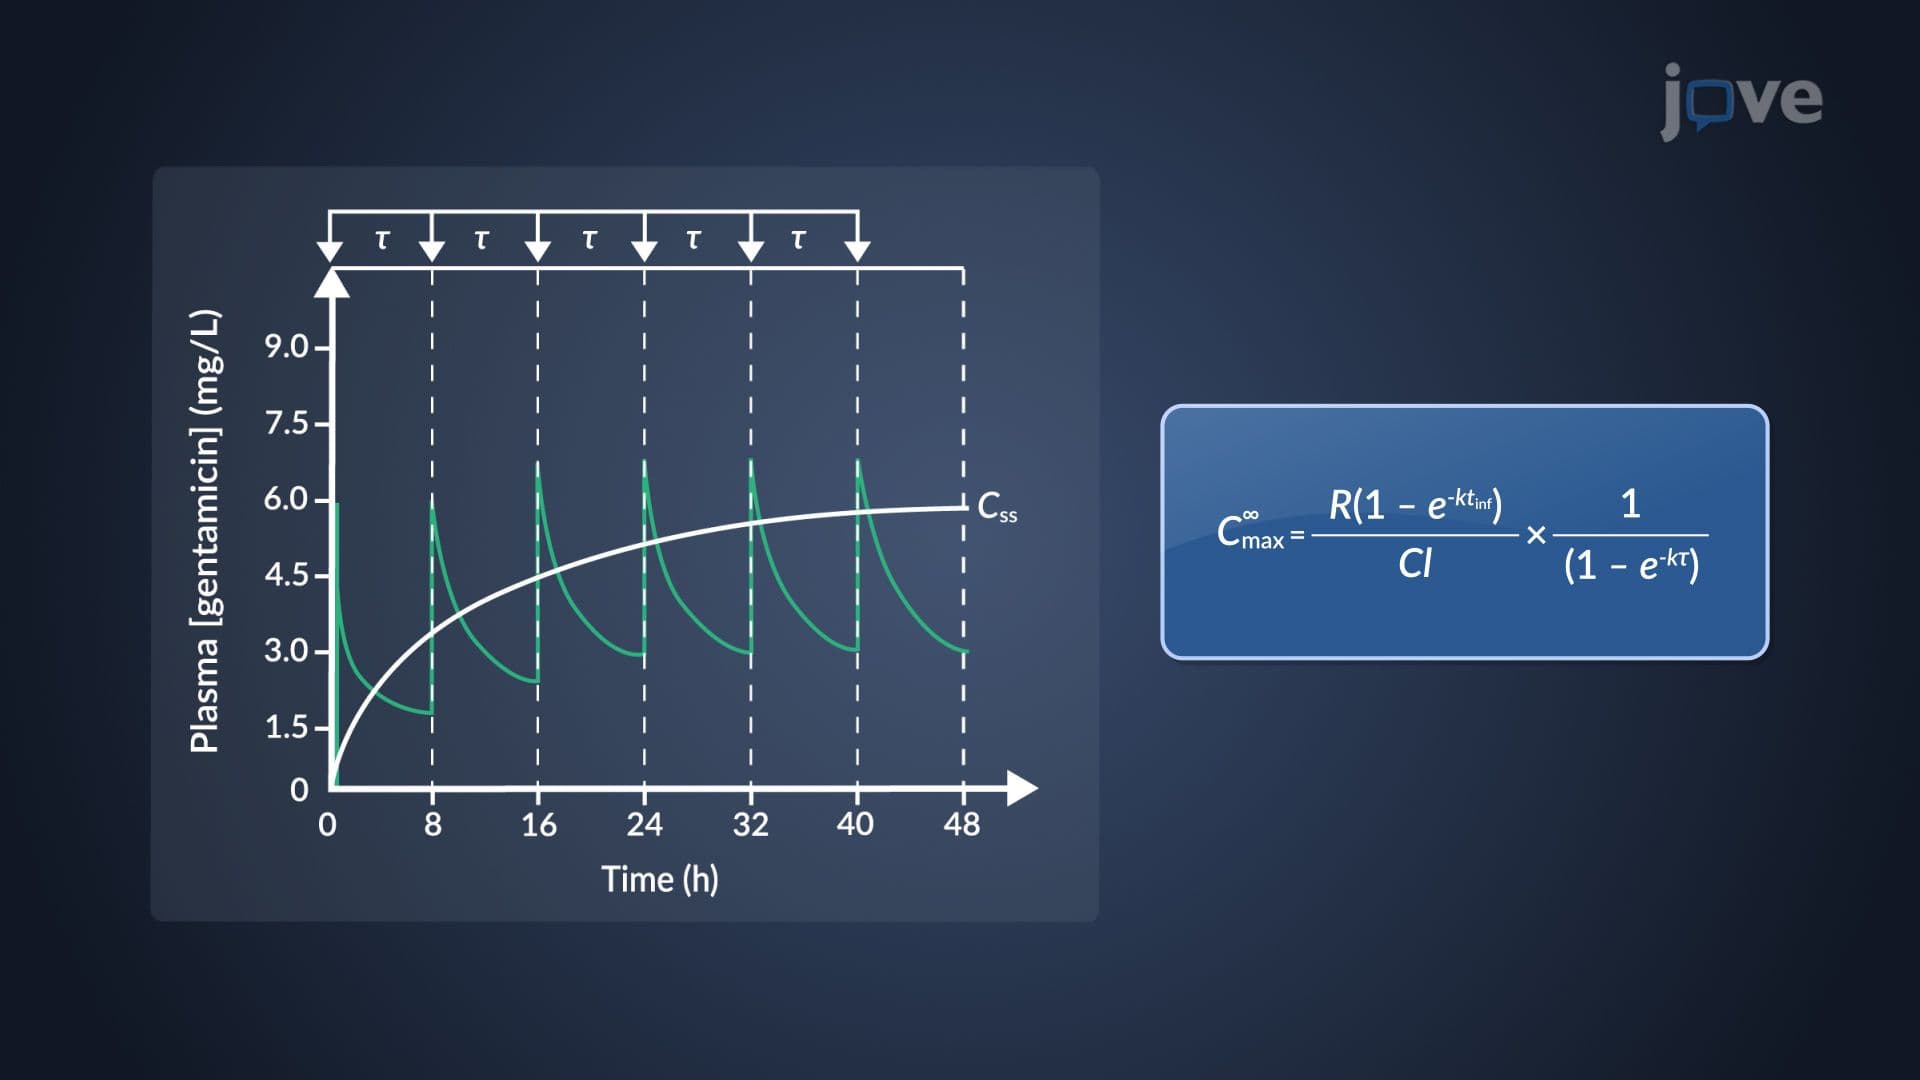
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:19
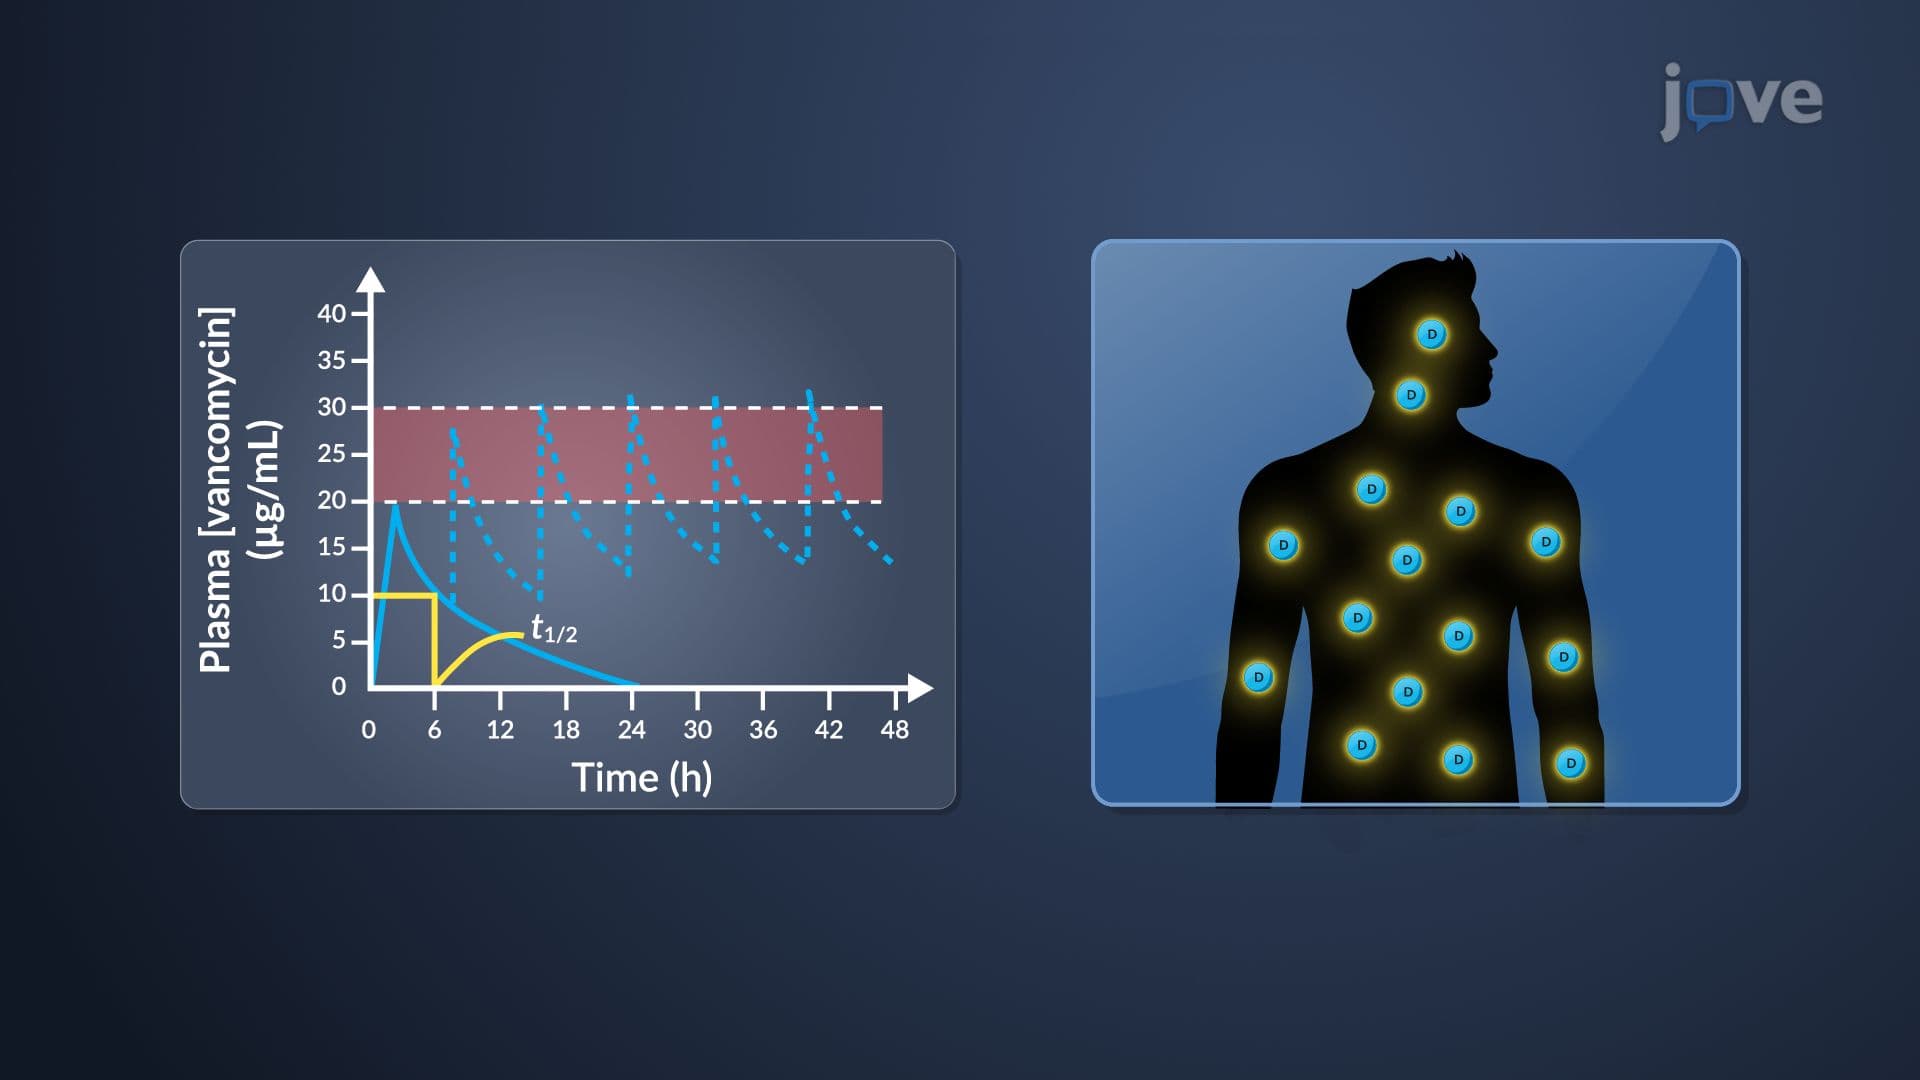
Dosage Interval and Administration Route: Determination Methods
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters