Related Experiment Video
Updated: Nov 30, 2025
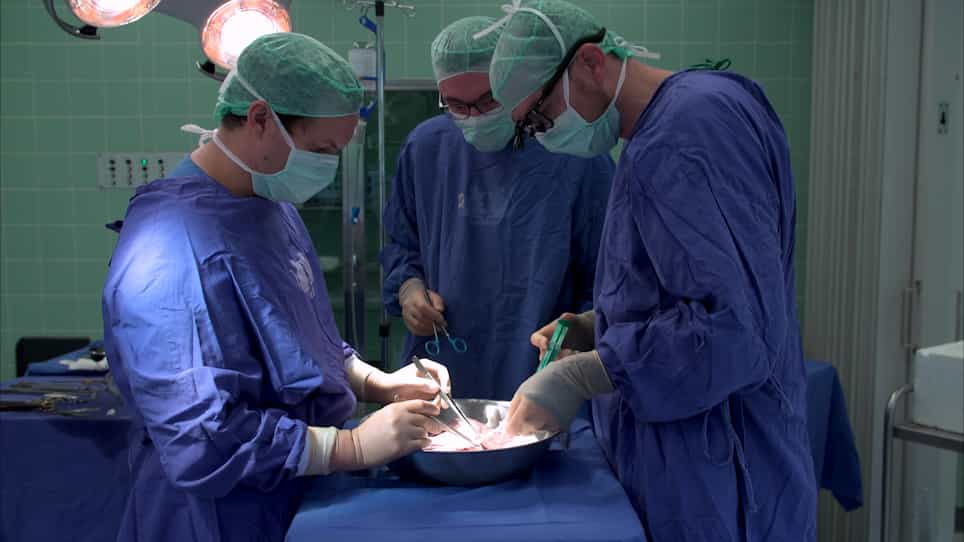
Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Impact of Payer Status on Delisting Among Liver Transplant Candidates in the United States
Krystal L Karunungan1, Yas Sanaiha, Roland A Hernandez
1Cardiovascular Outcomes Research Laboratories (CORELAB)Department of Surgery David Geffen School of Medicine at University of California, Los Angeles Los Angeles CA Division of Cardiac Surgery Swedish Medical Center Seattle WA Dumont-UCLA (University of California, Los Angeles) Transplant and Liver Cancer CentersDepartment of Surgery David Geffen School of Medicine at University of California, Los Angeles Los Angeles CA Department of Medicine Statistics Core University of California, Los Angeles Los Angeles CA.

Abstract:
Although socioeconomic disparities persist both pre- and post-transplantation, the impact of payer status has not been studied at the national level. We examined the association between public insurance coverage and waitlist outcomes among candidates listed for liver transplantation (LT) in the United States. All adults (age ≥18 years) listed for LT between 2002 and 2018 in the United Network for Organ Sharing database were included. The primary outcome was waitlist removal because of death or clinical deterioration. Continuous and categorical variables were compared using the Kruskal-Wallis and chi-square tests, respectively. Fine and Gray competing-risks regression was used to estimate the subdistribution hazard ratios (HRs) for risk factors associated with delisting. Of 131,839 patients listed for LT, 61.2% were covered by private insurance, 22.9% by Medicare, and 15.9% by Medicaid. The 1-year cumulative incidence of delisting was 9.0% (95% confidence interval [CI], 8.3%-9.8%) for patients with private insurance, 10.7% (95% CI, 9.9%-11.6%) for Medicare, and 10.7% (95% CI, 9.8%-11.6%) for Medicaid. In multivariable competing-risks analysis, Medicare (HR, 1.20; 95% CI, 1.17-1.24; P < 0.001) and Medicaid (HR, 1.20; 95% CI, 1.16-1.24; P < 0.001) were independently associated with an increased hazard of death or deterioration compared with private insurance. Additional predictors of delisting included Black race and Hispanic ethnicity, whereas college education and employment were associated with a decreased hazard of delisting. In this study, LT candidates with Medicare or Medicaid had a 20% increased risk of delisting because of death or clinical deterioration compared with those with private insurance. As more patients use public insurance to cover the cost of LT, targeted waitlist management protocols may mitigate the increased risk of delisting in this population.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Kidney Transplant II: Surgical Procedure
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:16
Kidney Transplant III: Nursing Management
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...