Related Experiment Video
Updated: Oct 2, 2026


Inducing Meningococcal Meningitis Serogroup C in Mice via Intracisternal Delivery
Published on: November 5, 2019
Case 288
Settimo Caruso1, Christine Cannataci1, Giuseppe Romano1
1From the Department of Diagnostic and Therapeutic Services (S.C.), and Department for the Treatment and Study of Cardiothoracic Diseases and Cardiothoracic Transplantation, Cardiology Unit (G.R.), Mediterranean Institute for Transplantation and Advanced Specialized Therapies (IRCCS-ISMETT), Via Ernesto Tricomi 5, 90127 Palermo, Italy; and Department of Radiology, Mater Dei Hospital, Msida, Malta (C.C.).

History A 46-year-old woman was admitted to our hospital with decompensated congestive heart failure and pericardial effusion diagnosed on echocardiography. She had no family history of sudden cardiac death. She was born at term and experienced no cardiac events until 4 years of age, at which point she was hospitalized because of three syncopal episodes that were not related to exercise. Over the next 10 years, she experienced two additional episodes of syncope not related to exercise. She had another hospital admission at 12 years of age. Clinical examination did not reveal cyanosis or clubbing, peripheral pulses were normal, and blood pressure was 90/60 mmHg. Her venous pressure was elevated, but the liver was not enlarged, and the lung fields were clear. Electrocardiography showed sinus rhythm, right bundle branch block, T-wave inversion in V6, and evidence of right atrial dilatation. Two-dimensional echocardiography showed normal intracardiac connections, with the tricuspid valve in the normal position and normal size of the left atrium and left ventricle with a normal ejection fraction. The right ventricle was dilated without evidence of right ventricular outflow tract obstruction. Implantation of an implantable cardioverter-defibrillator was considered but was ultimately contraindicated because of right ventricle anatomy. Thus, the patient received conservative care and was started on digoxin and diuretics. At 32 years of age, she experienced an episode of atrial flutter that was treated with electrical cardioversion. As stated earlier, at 46 years of age, she was admitted to our hospital with decompensated heart failure to be evaluated for a heart transplant. She underwent electrocardiography, echocardiography, cardiac MRI with and without administration of contrast media, and non-cardiac-gated multidetector CT with and without contrast media to rule out pulmonary embolism. The following quantitative results were obtained with MRI: Left ventricular end-diastolic volume (LVDV) was 40 mL (LVDV per body surface area [BSA], 25 mL/m2); left ventricular end-systolic volume (LVSV), 21 mL (LVSV/BSA, 13 mL/m2); stroke volume (SV), 19 mL (SV/BSA, 12 mL/m2); and ejection fraction, 47%. Right ventricular end-diastolic volume (RVDV) was 262 mL (RVDV/BSA, 164 mL/m2); right ventricular end-systolic volume (RVSV), 198 mL (RVSV/BSA, 124 mL/m2); stroke volume (SV), 64 mL (SV/BSA, 40 mL/m2); and ejection fraction, 24%. Phase contrast sequences in the aorta and pulmonary artery showed systemic output of 20 mL and pulmonary output of 18 mL. Tricuspid regurgitation was massive (46 mL) (Figs 1-4).
History A 46-year-old woman was admitted to our hospital with decompensated congestive heart failure and pericardial effusion diagnosed on echocardiography. She had no family history of sudden cardiac death. She was born at term and experienced no cardiac events until 4 years of age, at which point she was hospitalized because of three syncopal episodes that were not related to exercise. Over the next 10 years, she experienced two additional episodes of syncope not related to exercise. She had another hospital admission at 12 years of age. Clinical examination did not reveal cyanosis or clubbing, peripheral pulses were normal, and blood pressure was 90/60 mmHg. Her venous pressure was elevated, but the liver was not enlarged, and the lung fields were clear. Electrocardiography showed sinus rhythm, right bundle branch block, T-wave inversion in V6, and evidence of right atrial dilatation. Two-dimensional echocardiography showed normal intracardiac connections, with the tricuspid valve in the normal position and normal size of the left atrium and left ventricle with a normal ejection fraction. The right ventricle was dilated without evidence of right ventricular outflow tract obstruction. Implantation of an implantable cardioverter-defibrillator was considered but was ultimately contraindicated because of right ventricle anatomy. Thus, the patient received conservative care and was started on digoxin and diuretics. At 32 years of age, she experienced an episode of atrial flutter that was treated with electrical cardioversion. As stated earlier, at 46 years of age, she was admitted to our hospital with decompensated heart failure to be evaluated for a heart transplant. She underwent electrocardiography, echocardiography, cardiac MRI with and without administration of contrast media, and non-cardiac-gated multidetector CT with and without contrast media to rule out pulmonary embolism. The following quantitative results were obtained with MRI: Left ventricular end-diastolic volume (LVDV) was 40 mL (LVDV per body surface area [BSA], 25 mL/m2); left ventricular end-systolic volume (LVSV), 21 mL (LVSV/BSA, 13 mL/m2); stroke volume (SV), 19 mL (SV/BSA, 12 mL/m2); and ejection fraction, 47%. Right ventricular end-diastolic volume (RVDV) was 262 mL (RVDV/BSA, 164 mL/m2); right ventricular end-systolic volume (RVSV), 198 mL (RVSV/BSA, 124 mL/m2); stroke volume (SV), 64 mL (SV/BSA, 40 mL/m2); and ejection fraction, 24%. Phase contrast sequences in the aorta and pulmonary artery showed systemic output of 20 mL and pulmonary output of 18 mL. Tricuspid regurgitation was massive (46 mL) (Figs 1-4).
More Related Videos


Related Concept Videos
 01:22
Case Studies
 03:40
Dimensional Analysis
Conversion Factors and Dimensional Analysis
The unit...
 03:25
The Periodic Table
 03:26
Acids, Bases and Neutralization Reactions
 02:49
Bond Energies and Bond Lengths
 03:55
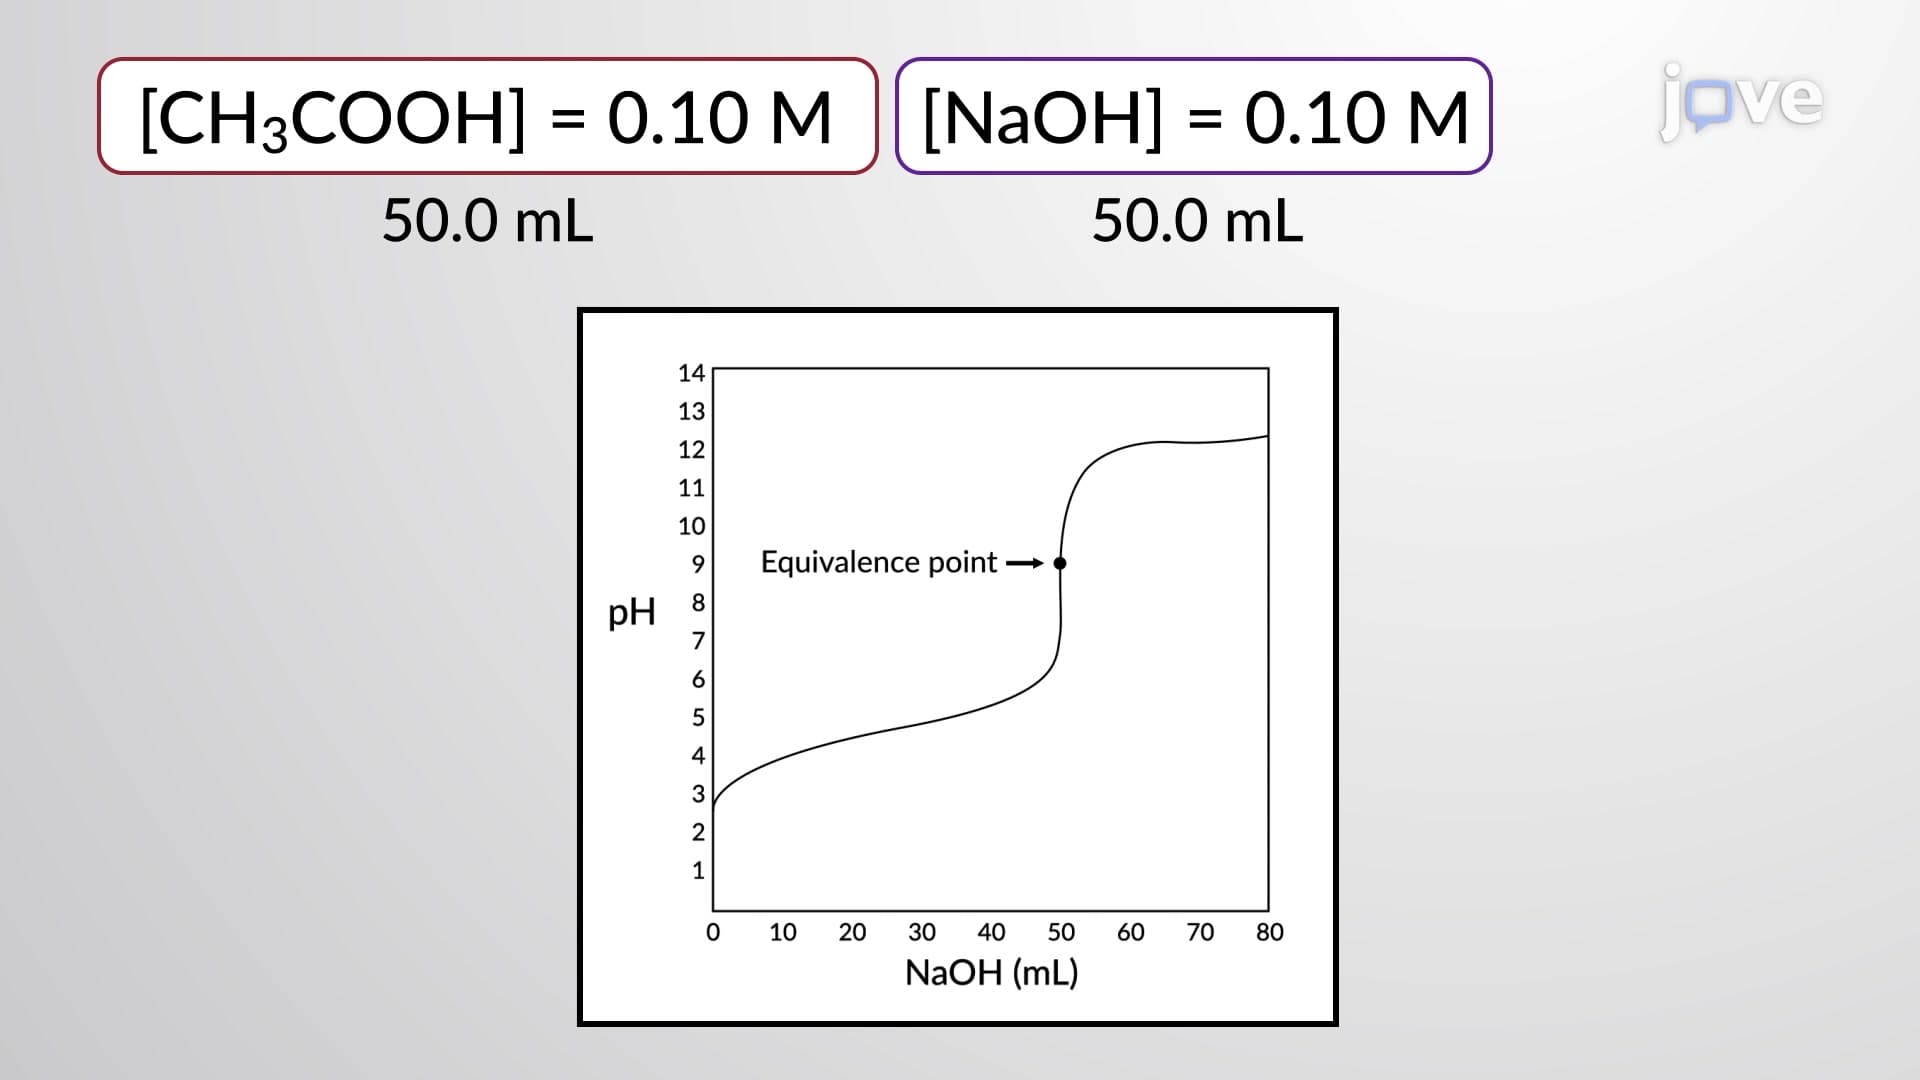
Titration Calculations: Weak Acid - Strong Base
For the titration of 25.00 mL of 0.100 M CH3CO2H with 0.100 M NaOH, the reaction can be represented as: