Related Experiment Video
Updated: Nov 30, 2025
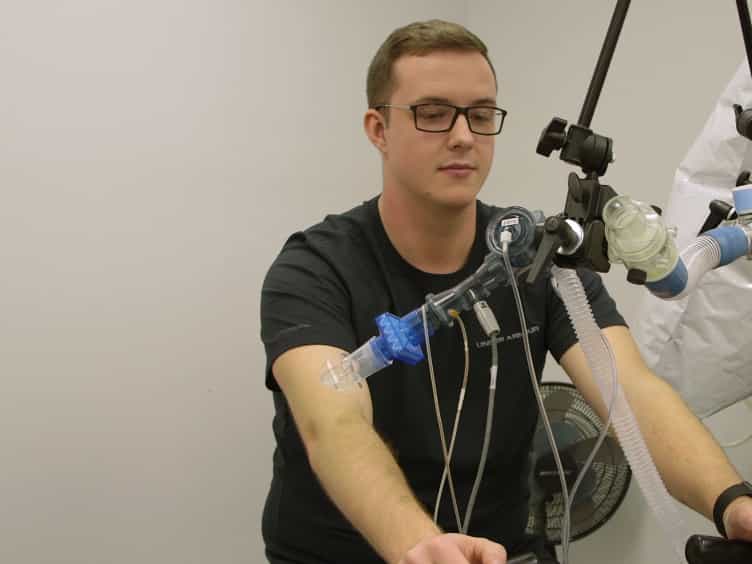

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Exercise pathophysiology differs between connective tissue diseases-associated pulmonary arterial hypertension and
Yi Zhang1, Qi Jin2, Zhihui Zhao1
1Center for Pulmonary Vascular Diseases, Fuwai Hospital, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Objectives:
Previous studies demonstrated that connective tissue diseases-associated pulmonary arterial hypertension (CTD-PAH) had a worse prognosis than idiopathic pulmonary arterial hypertension (IPAH), although the former one had better haemodynamic profiles and right heart function. To find potential explanations for this contradictory phenomenon, we compared the exercise pathophysiology of CTD-PAH with that of IPAH using cardiopulmonary exercise testing (CPET).
Methods:
Ninety-three CTD-PAH patients were retrospectively enrolled and matched 1:1 with 93 IPAH patients according to age, gender, body mass index, and body surface area. Multiple linear regression analysis was performed to adjust confounding factors.
Results:
CTD-PAH had higher rest heart rate (HR@Rest) and lower rest oxygen uptake/HR (VO2/HR@Rest) than IPAH. During exercise, the peak power (Power@Peak), VO2@Peak, peak metabolic equivalents (METS@Peak), peak minute ventilation (VE@Peak), peak tidal volume (VT@Peak), HR@Peak, peak systolic blood pressure (SBP@Peak) and peak diastolic blood pressure (DBP@Peak) of CTD-PAH were lower than those of IPAH. After adjustment, CTD-PAH still had lower values of Power@Peak, VO2@Peak, METS@Peak, VT@Peak, VO2/HR@Rest, DBP@Peak and had higher HR@Rest than IPAH.
Conclusions:
CTD-PAH had more impaired ventilation, cardiac function and muscular strength (reflected by CPET-derived parameters) than IPAH, in despite of better haemodynamic profiles and comparable heart structure (assessed by echocardiography) and functional status (indicated by World Health Organisation functional class, N-terminal pro-brain natriuretic peptide and six-minute walk distance).


Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:30
Peripheral Artery Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...