Related Experiment Video
Updated: Nov 29, 2025

Inducing and Characterizing Vesicular Steatosis in Differentiated HepaRG Cells
Published on: July 18, 2019
The Prevalence and Determinants of Hepatic Steatosis Assessed by Controlled Attenuation Parameter in Thai Chronic
A Sirinawasatien1, T Techasirioangkun1
1Division of Gastroenterology, Department of Medicine, Rajavithi Hospital, College of Medicine, Rangsit University, Bangkok, Thailand.

Aims:
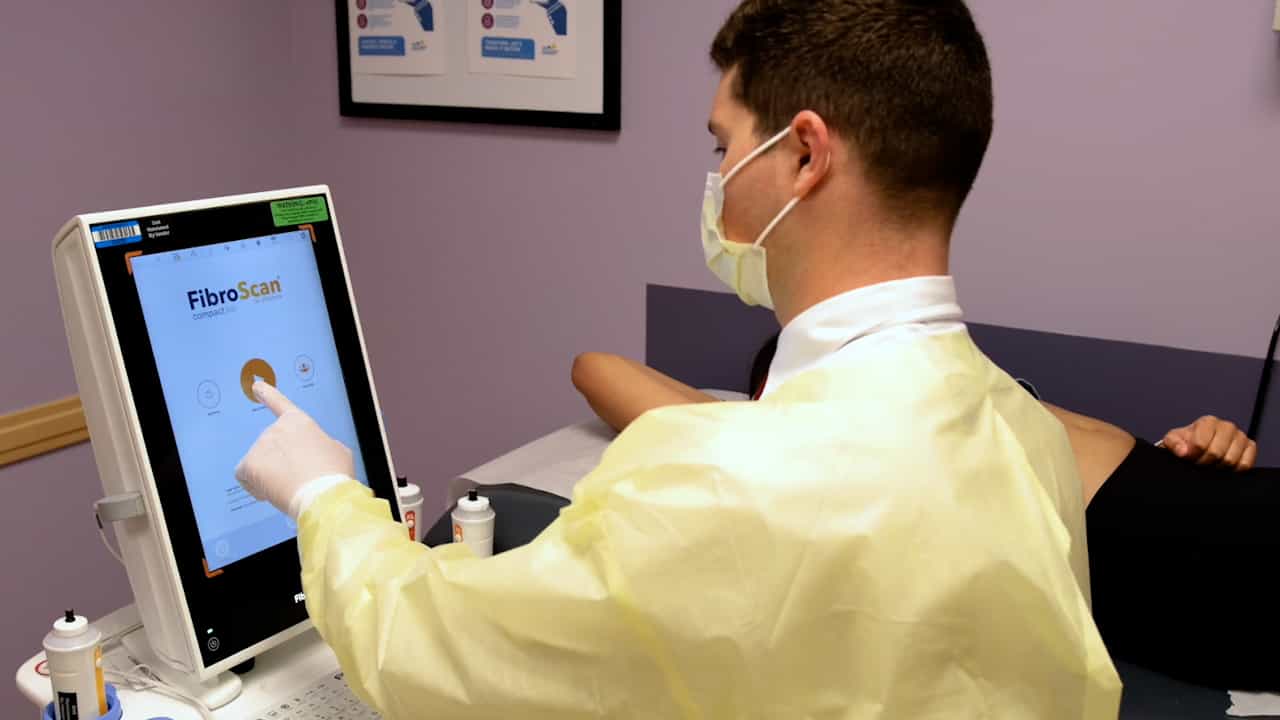
To describe the prevalence of hepatic steatosis using a controlled attenuation parameter (CAP) and to identify the determinants associated with steatosis in Thai chronic hepatitis C patients. Patients and Methods. An observational study was conducted among consecutive chronic hepatitis C patients who underwent vibration-controlled transient elastography (VCTE, FibroScan®) with CAP and followed up at Rajavithi Hospital, Bangkok, Thailand, between June 2018 and May 2019. Hepatic steatosis (i.e., steatosis grades S1-3) was defined by the CAP cutoff value of ≥248 (dB/m). VCTE with CAP assessments and medical records were retrospectively reviewed, and the prevalence and determinants of hepatic steatosis were analyzed.
Results:
A total of 197 eligible patients, of whom 127 (64.5%) were male, were included. The mean age was 54.52 years (SD 9.49 years), and 41.1% of subjects had a body mass index ≥ 25. The prevalence of hepatic steatosis was 26.9%. The mean liver stiffness measurement (LSM) was 21.50 kPa (SD 15.58 kPa), and 61.9% of the study population had cirrhosis, which was defined as LSM ≥ 12.5 kPa. Genotype (GT) 3 was predominant at 40.1%, followed by GT1 at 38.1% and GT6 at 21.8%. The median serum hepatitis C virus viral load was 1,100,000 IU/mL (range 5,824-20,436,840). The significant determinants of hepatic steatosis were obesity (aOR 8.58 (95% CI: 3.41-21.54)) and diabetes mellitus (aOR 3.30 (95% CI: 1.24-8.78)).
Conclusion:
A large proportion of these Thai chronic hepatitis C patients (26.9%) had hepatic steatosis, which was strongly associated with host metabolic factors, e.g., obesity (BMI ≥ 25) and diabetes mellitus. These cofactors contributed to the progression of liver disease to cirrhosis and required concurrent management with antiviral therapy.
More Related Videos
 08:35
A Model of Experimental Steatosis In Vitro: Hepatocyte Cell Culture in Lipid Overload-Conditioned Medium
Published on: May 18, 2021
 05:56
Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...