Related Experiment Video
Updated: Nov 28, 2025
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Cesarean myomectomy in the last ten years; A true shift from contraindication to indication: A systematic review and
Manu Goyal1, Ayman Shehata Dawood2, Shereen B Elbohoty2
1Department of Obstetrics & Gynecology, All India Institute of Medical Sciences, Jodhpur, India.

Background:
A lot of debate is present about Cesarean myomectomy (CM) in women with uterine myoma whether to consider it a feasible and safe procedure or an absolute contraindication.
Objective:
To assess the safety and feasibility of myomectomy during cesarean section in women with uterine myoma.
Search Strategy:
Electronic search was made on MEDLINE, EMBASE, Cochrane Library, ISI web of knowledge and Scopus from January 1, 2008 to December 31, 2019 using terms "Caesarean section", "Myomectomy", "Fibroid", "Caesarean myomectomy".
Selection Criteria:
All full length studies either prospective or retrospective that address caesarean myomectomy were included.
Data Collection And Analysis:
The outcomes studied were haemorrhage, mean change in haemoglobin, operative time, need for blood transfusion, febrile morbidity and duration of hospital stay.
Results:
Total 249 studies were assessed for eligibility and 17 studies included in analysis with 6545 women. There were 4702 (71.85 %) women in caesarean myomectomy (CM) group and 1843 (28.15 %) women in cesarean section (CS) group. There was statistically significant but clinically insignificant decrease in hemoglobin [MD = 0.27, 95 %CI = 0.08-0.45, p = 0.005; very low quality], significant higher need for blood transfusion [RR = 1.45, 95 %CI = 1.05-1.99, p = 0.02; high quality] in CM group versus CS alone. The mean operative time (minutes) [MD = 14.77, 95 %CI = 6.91-22.64, p = 0.0002; moderate quality] and mean hospital stay (days) [MD = 0.36, 95 %CI = 0.19-0.53, p < 0.00001; high quality] was significantly less in CM group, though of not any clinical significance. No difference in incidence of haemorrhage [RR = 1.16, 95 %CI = 0.86-1.56, p = 0.32; moderate quality evidence] and fever [RR = 1.17, 95 %CI = 0.83-1.65), p = 0.36; moderate quality] in two groups.
Conclusions:
The meta-analysis suggests CM is associated with clinical insignificant increase in operative time, blood loss and hospital stay, especially with multiple and large size myomas. CM should be preferred over CS alone especially by experienced surgeons with appropriate haemostatic techniques and tertiary care centres.
More Related Videos
 11:29
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
 05:21
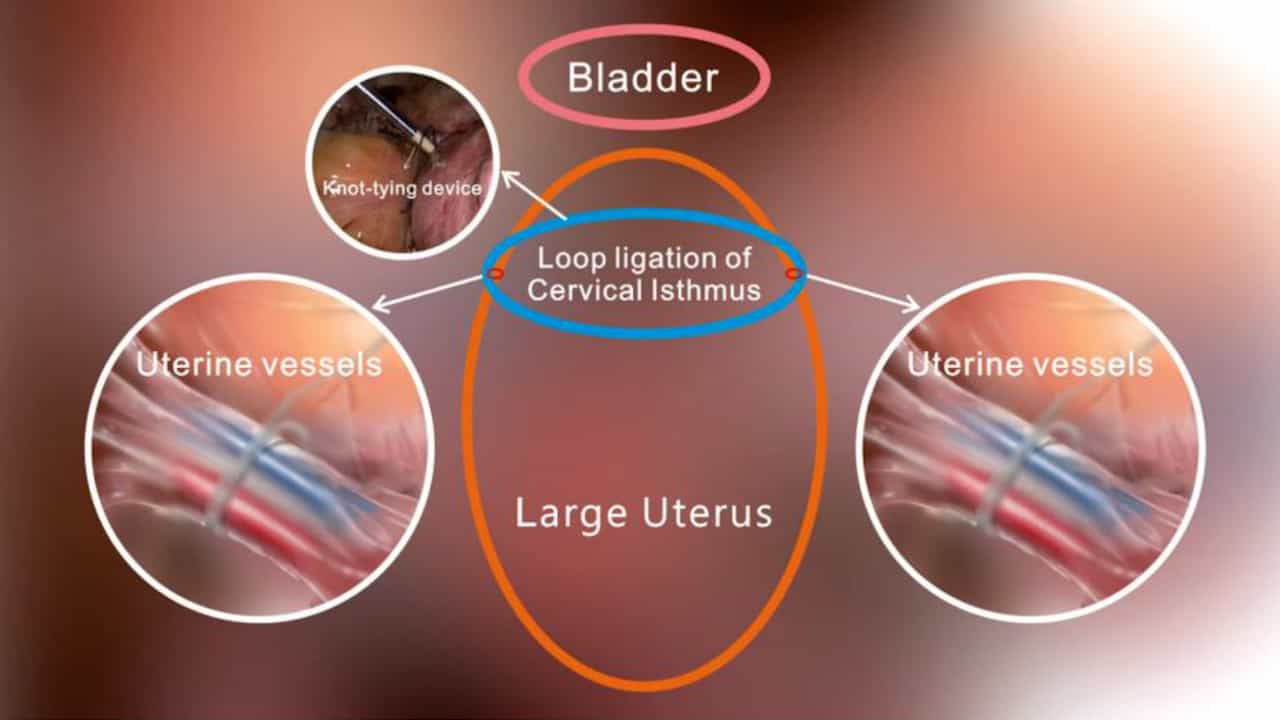
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025