Related Experiment Video
Updated: Nov 28, 2025
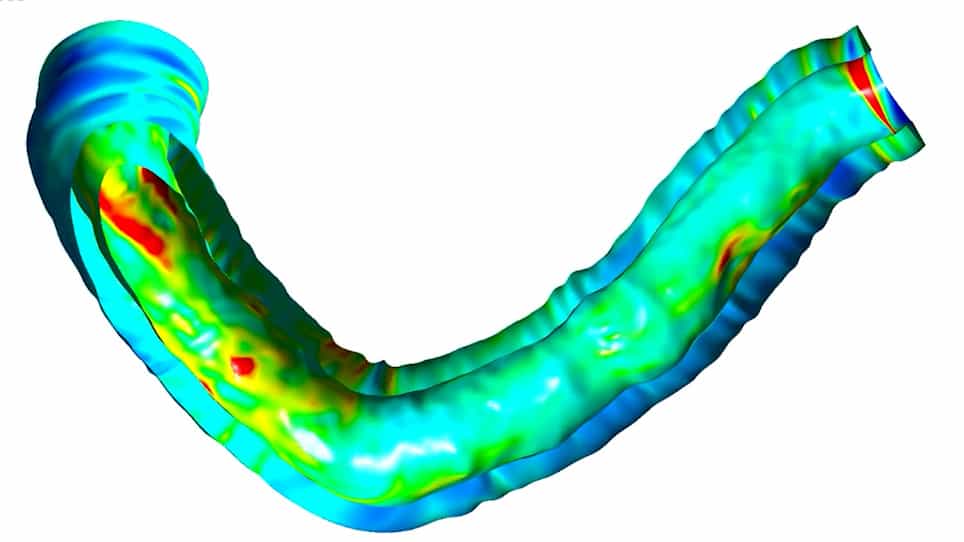

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Prevalence, Features, and Prognosis of Artery-to-Artery Embolic ST-Segment-Elevation Myocardial Infarction: An
Masahiro Takahata1, Yasushi Ino1, Takashi Kubo1
1Department of Cardiovascular Medicine Wakayama Medical University Wakayama Japan.

Insights
Artery-to-artery embolic myocardial infarction (AAEMI) is a rare cause of ST-segment-elevation myocardial infarction, identified in 3.4% of patients. AAEMI exhibits unique plaque morphology with a larger lumen area at the rupture site and smaller area at occlusion.
Area of Science:
- Cardiology
- Interventional Cardiology
- Medical Imaging
Background:
- Acute coronary syndrome mechanisms include plaque rupture, erosion, and calcified nodules.
- Artery-to-artery embolic myocardial infarction (AAEMI) is defined as ST-segment-elevation myocardial infarction from a thrombus migrating from a proximal ruptured plaque.
- Optical coherence tomography (OCT) is crucial for visualizing coronary plaque morphology.
Purpose of the Study:
- To determine the prevalence of AAEMI in patients with ST-segment-elevation myocardial infarction.
- To investigate the distinct clinical and morphological features of AAEMI using OCT.
- To compare AAEMI characteristics with other causes of ST-segment-elevation myocardial infarction.
Main Methods:
- Retrospective enrollment of 297 ST-segment-elevation myocardial infarction patients undergoing pre-percutaneous coronary intervention OCT.
- Classification into four groups: plaque rupture, plaque erosion, calcified nodule, and AAEMI based on OCT findings.
- Analysis of culprit vessel, minimum lumen area, lumen area at rupture/occlusion sites, treatment strategy, and major adverse cardiac events.
Main Results:
- AAEMI prevalence was 3.4%, with the right coronary artery as the culprit vessel in 60% of cases.
- AAEMI demonstrated a significantly larger minimum lumen area at the culprit site compared to other groups (4.0 mm² vs. 1.0-1.1 mm²).
- Patients with AAEMI had a larger lumen area at the rupture site (4.4 mm² vs. 1.5 mm²) and a smaller minimum lumen area at occlusion (1.2 mm²). 40% received a non-stent strategy with 0% 3-year MACE.
Conclusions:
- AAEMI is an uncommon etiology of ST-segment-elevation myocardial infarction with specific OCT-defined plaque characteristics.
- Unique morphological features include a larger lumen area at the rupture site and a smaller lumen area at the occlusion site.
- AAEMI patients showed favorable outcomes with a non-stent strategy and no major adverse cardiac events at 3 years.
Abstract:
Background The major underlying mechanisms contributing to acute coronary syndrome are plaque rupture, plaque erosion, and calcified nodule. Artery-to-artery embolic myocardial infarction (AAEMI) was defined as ST-segment-elevation myocardial infarction caused by migrating thrombus formed at the proximal ruptured plaque. The aim of this study was to investigate the prevalence and clinical features of AAEMI by using optical coherence tomography. Methods and Results This study retrospectively enrolled 297 patients with ST-segment-elevation myocardial infarction who underwent optical coherence tomography before percutaneous coronary intervention. Patients were divided into 4 groups consisting of plaque rupture, plaque erosion, calcified nodule, and AAEMI according to optical coherence tomography findings. The prevalence of AAEMI was 3.4%. The culprit vessel in 60% of patients with AAEMI was right coronary artery. Minimum lumen area at the culprit site was larger in AAEMI compared with plaque rupture, plaque erosion, and calcified nodule (4.0 mm2 [interquartile range (IQR), 2.2-4.9] versus 1.0 mm2 [IQR, 0.8-1.3] versus 1.0 mm2 [IQR, 0.8-1.2] versus 1.1 mm2 [IQR, 0.7-1.6], P<0.001). Lumen area at the rupture site was larger in patients with AAEMI compared with patients with plaque rupture (4.4 mm2 [IQR, 2.5-6.7] versus 1.5 mm2 [IQR, 1.0-2.4], P<0.001). In patients with AAEMI, the median minimum lumen area at the occlusion site was 1.2 mm2 (IQR, 1.0-2.1), 40% of them had nonstent strategy, and the 3-year major adverse cardiac event rate was 0%. Conclusions AAEMI is a rare cause for ST-segment-elevation myocardial infarction and has unique morphological features of plaque including larger lumen area at rupture site and smaller lumen area at the occlusion site.
More Related Videos
 07:18
Evaluation of Capillary and Other Vessel Contribution to Macular Perfusion Density Measured with Optical Coherence Tomography Angiography
Published on: February 18, 2022
 09:46
Imaging In-Stent Restenosis: An Inexpensive, Reliable, and Rapid Preclinical Model
Published on: September 14, 2009
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Coronary Artery Disease II: Pathophysiology
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...