Related Experiment Video
Updated: Aug 4, 2026


Extraction of Tissue Antigens for Functional Assays
Published on: September 10, 2012
Rapid decrease of insulin-specific IgG antibody levels in insulin-dependent patients transferred to semi-synthetic
P Raskin1, D D Etzwiler, J K Davidson
1University of Texas, Southwestern Medical School, Dallas.

A multicenter, open trial was designed to examine the efficacy and safety of semi-synthetic human insulin (SSHI; Novolin R and Novolin L, SQUIBB-NOVO) in patients with insulin-dependent diabetes mellitus who were transferred from other commercially-available insulins. Whether such a change in therapy would reduce circulating IgG antibodies to antibovine insulin was also evaluated. A total of 68 males and females, 8-62 yr of age, were maintained on their original insulin therapy for 4 weeks, when both glycosylated hemoglobin and fasting blood glucose were assessed. IgG antibody titers to antibovine insulin were also measured. All patients were then transferred to SSHI for a period of 20 weeks. The same variables were evaluated at Weeks 2, 4, 8, and 20. Mean fasting blood glucose levels rose monotonically from 189-226.3 mg/dl over the course of the 20-week clinical trial. There was a slight but insignificant increase in glycosylated hemoglobin by the end of the test period. The average value for antibovine insulin IgG antibodies decreased from 2.54 mu/ml at baseline to 1.32 mu/ml by the completion of the trial. Significant decreases were first observed 4 weeks after the patients were placed on SSHI therapy. After transfer to SSHI, 43.3% of the patients achieved some improvement in glycemic control and only 16.4% were worse than at baseline. A decrease in weekly hypoglycemic reactions occurred during the course of the SSHI therapy. It appears that SSHI provides safe and effective treatment for insulin-dependent diabetic patients and that its use results in a rapid and significant decrease in insulin antibody formation.
A multicenter, open trial was designed to examine the efficacy and safety of semi-synthetic human insulin (SSHI; Novolin R and Novolin L, SQUIBB-NOVO) in patients with insulin-dependent diabetes mellitus who were transferred from other commercially-available insulins. Whether such a change in therapy would reduce circulating IgG antibodies to antibovine insulin was also evaluated. A total of 68 males and females, 8-62 yr of age, were maintained on their original insulin therapy for 4 weeks, when both glycosylated hemoglobin and fasting blood glucose were assessed. IgG antibody titers to antibovine insulin were also measured. All patients were then transferred to SSHI for a period of 20 weeks. The same variables were evaluated at Weeks 2, 4, 8, and 20. Mean fasting blood glucose levels rose monotonically from 189-226.3 mg/dl over the course of the 20-week clinical trial. There was a slight but insignificant increase in glycosylated hemoglobin by the end of the test period. The average value for antibovine insulin IgG antibodies decreased from 2.54 mu/ml at baseline to 1.32 mu/ml by the completion of the trial. Significant decreases were first observed 4 weeks after the patients were placed on SSHI therapy. After transfer to SSHI, 43.3% of the patients achieved some improvement in glycemic control and only 16.4% were worse than at baseline. A decrease in weekly hypoglycemic reactions occurred during the course of the SSHI therapy. It appears that SSHI provides safe and effective treatment for insulin-dependent diabetic patients and that its use results in a rapid and significant decrease in insulin antibody formation.


Related Concept Videos
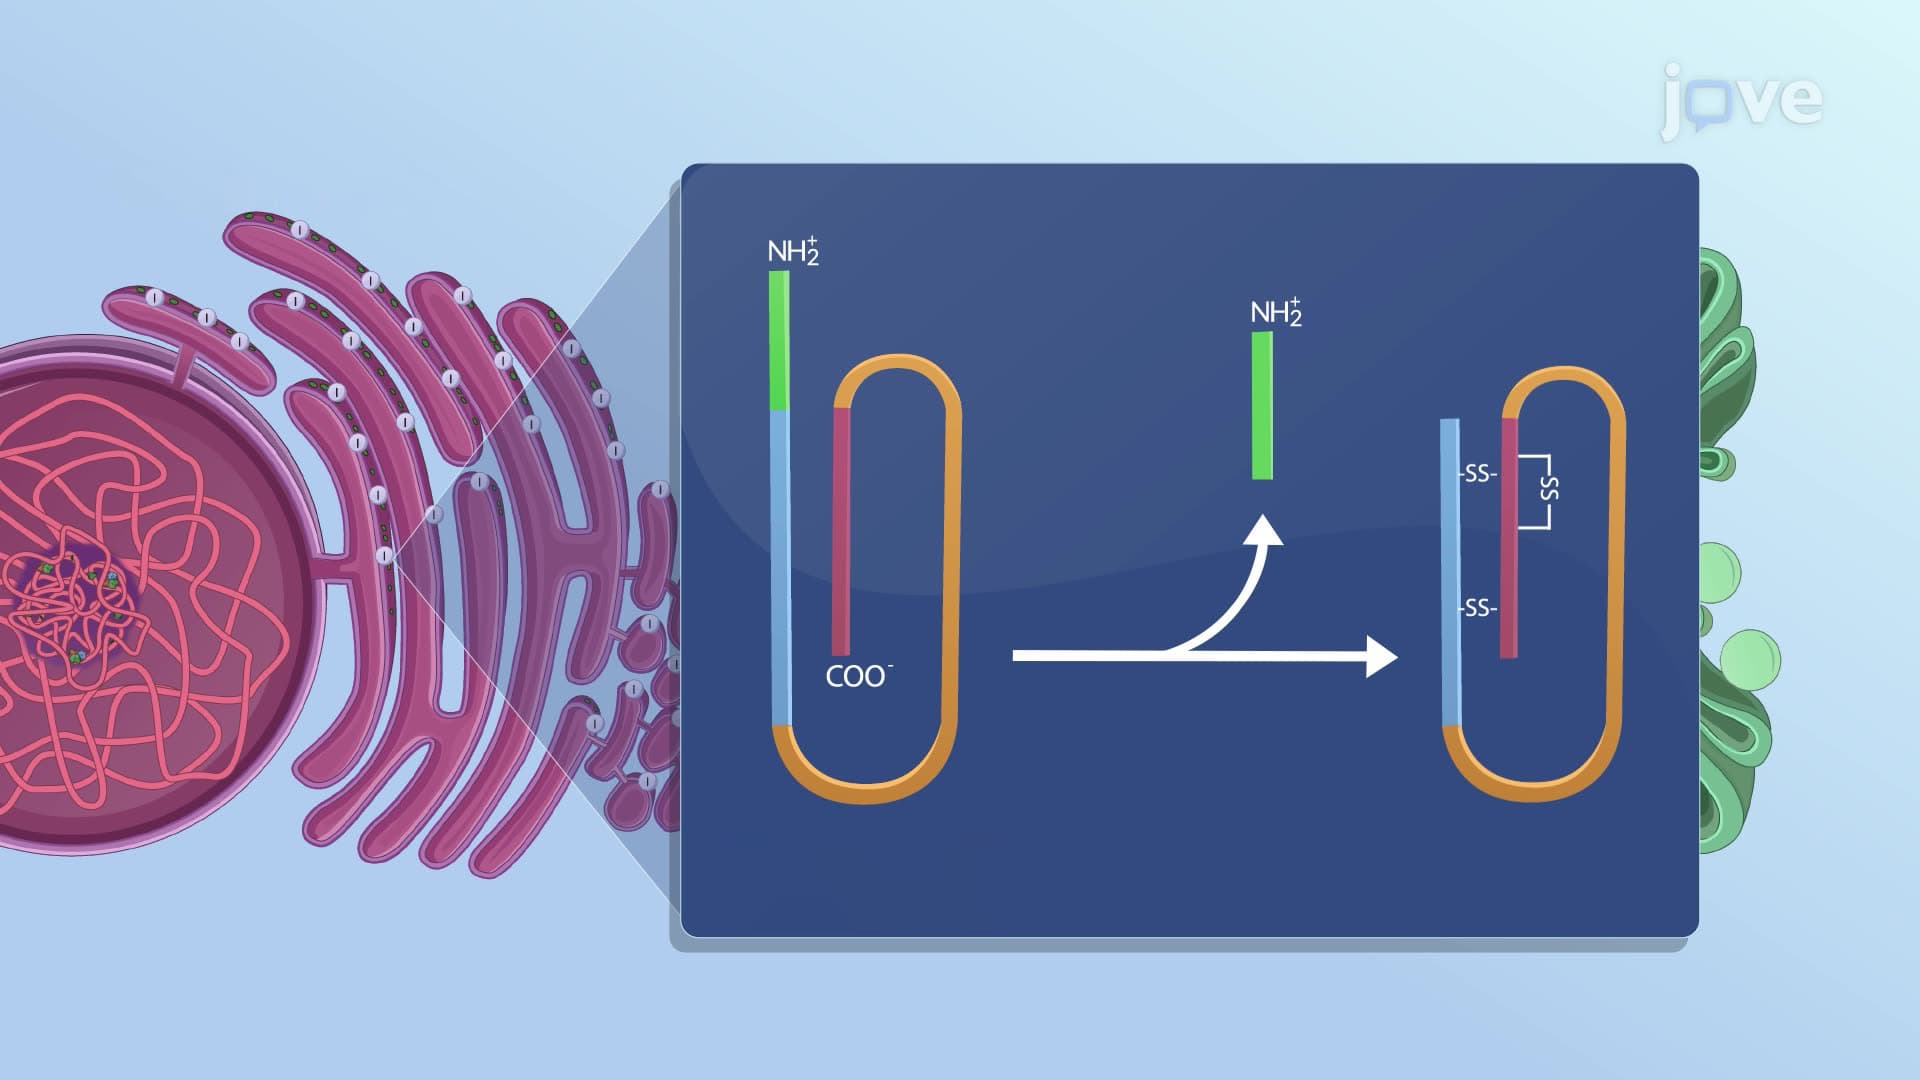 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:15
Hypoglycemia and Glucagon
 01:12
Type I Diabetes I: Introduction
 01:26
Type I Diabetes II: Pathophysiology