Related Experiment Video
Updated: Nov 27, 2025
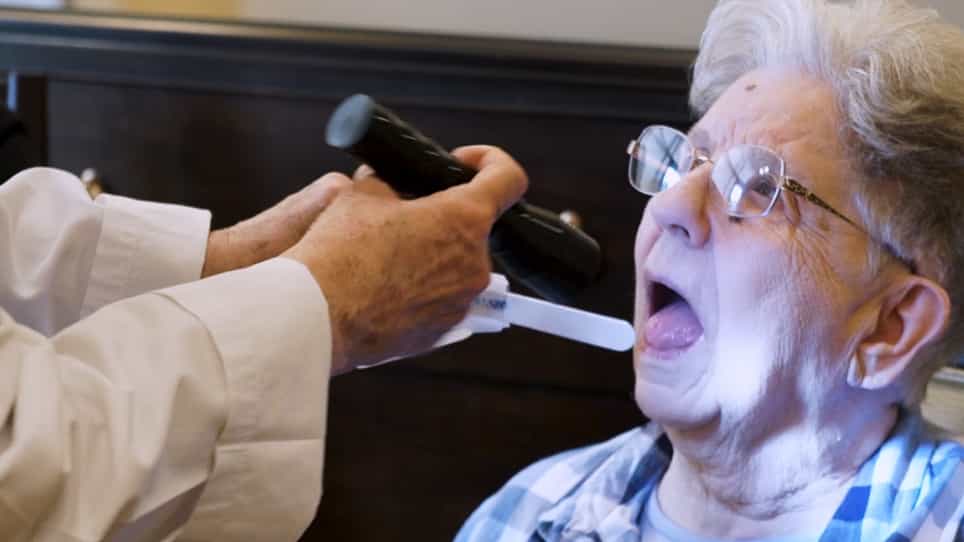
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Relationship between Socioeconomic Inequalities and Oral Hygiene Indicators in Private and Public Schools in Karachi:
Tamsal Khalid1, Syed Sarosh Mahdi1,2, Mariam Khawaja1
1Department of Community Dentistry, Jinnah Medical & Dental College, Sohail University, Karachi 74800, Pakistan.

Background:
The study investigated the relationship between socioeconomic status and oral hygiene indicators in two schools located in Karachi, Pakistan. Oral hygiene indicators of public and private school children were compared. Private schools cater to children of relatively wealthier families compared to public school, whose attendees are generally children from less affluent backgrounds. The aim of this study was to determine whether socio-economic differences and inequalities have an impact on key oral hygiene indicators.
Methodology:
Primary data for this research was collected from community school visits conducted by the community dentistry department of Jinnah Medical and Dental and Medical College from January to September 2019. A convenience sample of the two schools, comprising 300 school students was selected. Data was collected using modified World Health Organization (WHO) oral health care forms. A pre-tested/customized dental hygiene form based on WHO forms was created by the research team. This form was used to measure DMFT/dmft scores and key oral hygiene indicators in the sample.
Results:
A total sample size of 300 school-children affiliated with public and private schools was selected. The children's age ranged from 2 to 18 years. The mean DMFT scores of private and public-school children were not significantly different (private (1.82) vs. public (1.48)). (p = 0.257). The mean of carious teeth was 1.69 in private school children compared to 1.34 in government school children, whereas the mean values of other key indicators of oral hygiene including plaque deposition (p = 0.001), dental stains (p < 0.001) and bleeding gums/gingivitis (p < 0.001), were statistically significant between public and private school children.
Conclusion:
Oral health inequalities can be reduced with increased awareness and public funding to cater for the oral health needs of children of less affluent families. A dynamic and practical community-oriented program is fundamental for enhancing pediatric oral hygiene status, particularly for children attending government schools.

Related Concept Videos
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 02:30
Naturalistic Observations
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:11
Oral Cavity
Teeth: The teeth are the hardest structures in our bodies. Humans have two sets of teeth throughout their lifetime: deciduous (baby) teeth and permanent teeth. Each tooth consists of several parts: the crown (visible part), the root (embedded in the jaw), enamel (hard outer...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
Assessment of the Gastrointestinal System II: Health Perception Pattern
Health Perception Patterns
Health perception patterns offer valuable insights into a patient's lifestyle habits and how they may impact their GI health. These patterns include: