Related Experiment Video
Updated: Nov 27, 2025
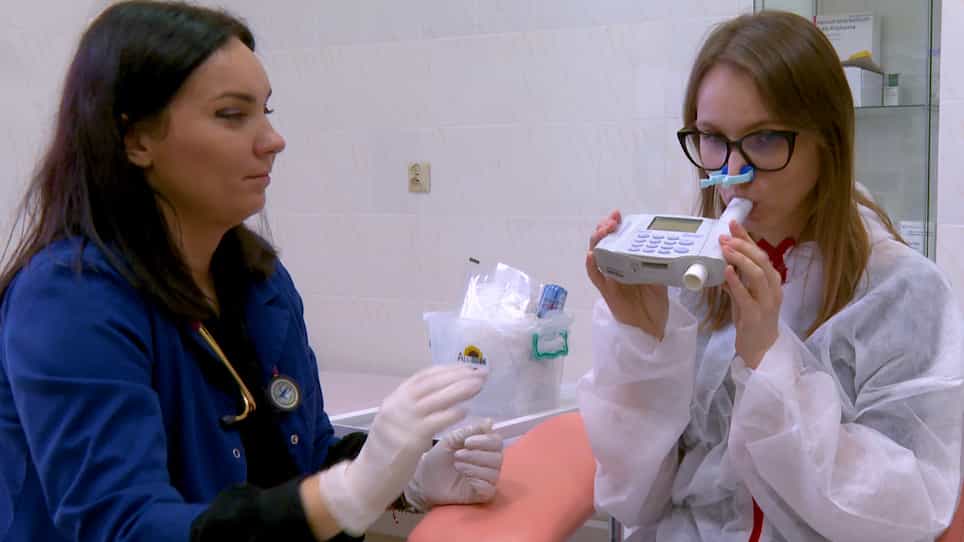

Symptom Assessment of Patients with Allergic Rhinitis Using an Allergen Exposure Chamber
Published on: March 3, 2023
Endotypes identified by cluster analysis in asthmatics and non-asthmatics and their clinical characteristics at
Rachel Nadif1, Mickael Febrissy2, Miora Valérie Andrianjafimasy3
1Université Paris-Saclay, UVSQ, Univ. Paris-Sud, INSERM, Equipe d'Epidémiologie Respiratoire Intégrative, CESP, 94807 Villejuif, France rachel.nadif@inserm.fr.

Background:
Identifying relevant asthma endotypes may be the first step towards improving asthma management. We aimed identifying respiratory endotypes in adults using a cluster analysis and to compare their clinical characteristics at follow-up.
Methods:
The analysis was performed separately among current asthmatics (CA, n=402) and never asthmatics (NA, n=666) from the first follow-up of the French EGEA study (EGEA2). Cluster analysis jointly considered 4 demographic, 22 clinical/functional (respiratory symptoms, asthma treatments, lung function) and four blood biological (allergy-related, inflammation-related and oxidative stress-related biomarkers) characteristics at EGEA2. The clinical characteristics at follow-up (EGEA3) were compared according to the endotype identified at EGEA2.
Results:
We identified five respiratory endotypes, three among CA and two among NA: CA1 (n=53) with active treated adult-onset asthma, poor lung function, chronic cough and phlegm and dyspnoea, high body mass index, and high blood neutrophil count and fluorescent oxidation products level; CA2 (n=219) with mild asthma and rhinitis; CA3 (n=130) with inactive/mild untreated allergic childhood-onset asthma, high frequency of current smokers and low frequency of attacks of breathlessness at rest, and high IgE level; NA1 (n=489) asymptomatic, and NA2 (n=177) with respiratory symptoms, high blood neutrophil and eosinophil counts. CA1 had poor asthma control and high leptin level, CA2 had hyper-responsiveness and high interleukin (IL)-1Ra, IL-5, IL-7, IL-8, IL-10, IL-13 and TNF-α levels, and NA2 had high leptin and C reactive protein levels. Ten years later, asthmatics in CA1 had worse clinical characteristics whereas those in CA3 had better respiratory outcomes than CA2; NA in NA2 had more respiratory symptoms and higher rate of incident asthma than those in NA1.
Conclusion:
These results highlight the interest to jointly consider clinical and biological characteristics in cluster analyses to identify endotypes among adults with or without asthma.
More Related Videos
 06:34
A Component-resolved Diagnostic Approach for a Study on Grass Pollen Allergens in Chinese Southerners with Allergic Rhinitis and/or Asthma
Published on: June 4, 2017
 08:44
Identification and Characterization of Immunogenic RNA Species in HDM Allergens that Modulate Eosinophilic Lung Inflammation
Published on: May 30, 2020
Related Concept Videos
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:29
Asthma-I: Introduction
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...