Related Experiment Video
Updated: Nov 27, 2025
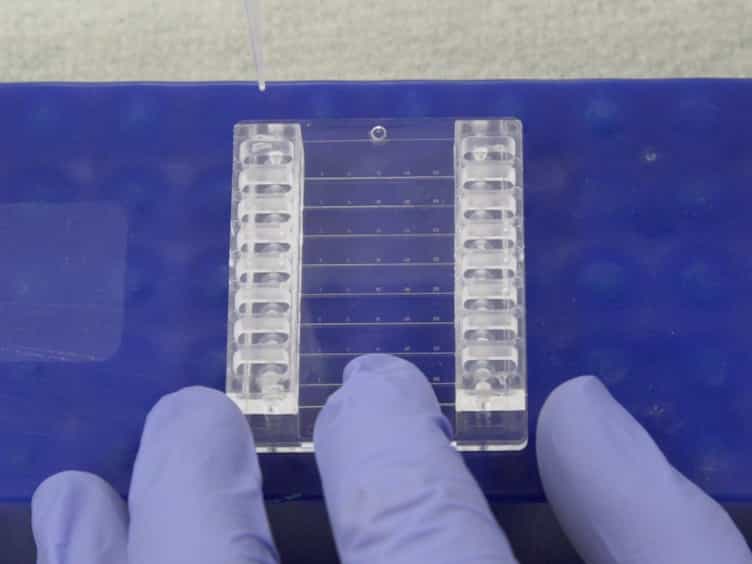

A Microfluidic Flow Chamber Model for Platelet Transfusion and Hemostasis Measures Platelet Deposition and Fibrin Formation in Real-time
Published on: February 14, 2017
How well do platelets prevent bleeding?
1University of Pittsburgh, Vitalant Clinical Services, Pittsburgh, PA.

Prophylactic platelet transfusions are used to reduce the risk of spontaneous bleeding in patients with treatment- or disease-related severe thrombocytopenia. A prophylactic platelet-transfusion threshold of <10 × 103/µL has been shown to be safe in stable hematology/oncology patients. A higher threshold and/or larger or more frequent platelet doses may be appropriate for patients with clinical features associated with an increased risk of bleeding such as high fevers, sepsis, disseminated intravascular coagulation, anticoagulation therapy, or splenomegaly. Unique factors in the outpatient setting may support the use of a higher platelet-transfusion threshold and/or dose of platelets. A prophylactic platelet-transfusion strategy has been shown to be associated with a lower risk of bleeding compared with no prophylaxis in adult patients receiving chemotherapy but not for autologous transplant recipients. Despite the use of prophylactic platelet transfusions, a high incidence (50% to 70%) of spontaneous bleeding remains. Using a higher threshold or larger doses of platelets does not change this risk. New approaches to reduce the risk of spontaneous bleeding, including antifibrinolytic therapy, are currently under study.
Prophylactic platelet transfusions are used to reduce the risk of spontaneous bleeding in patients with treatment- or disease-related severe thrombocytopenia. A prophylactic platelet-transfusion threshold of <10 × 103/µL has been shown to be safe in stable hematology/oncology patients. A higher threshold and/or larger or more frequent platelet doses may be appropriate for patients with clinical features associated with an increased risk of bleeding such as high fevers, sepsis, disseminated intravascular coagulation, anticoagulation therapy, or splenomegaly. Unique factors in the outpatient setting may support the use of a higher platelet-transfusion threshold and/or dose of platelets. A prophylactic platelet-transfusion strategy has been shown to be associated with a lower risk of bleeding compared with no prophylaxis in adult patients receiving chemotherapy but not for autologous transplant recipients. Despite the use of prophylactic platelet transfusions, a high incidence (50% to 70%) of spontaneous bleeding remains. Using a higher threshold or larger doses of platelets does not change this risk. New approaches to reduce the risk of spontaneous bleeding, including antifibrinolytic therapy, are currently under study.


Related Concept Videos
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:18
Structure and Function of Platelets
Platelets are continually replenished, circulating in the bloodstream for 9-12 days before being removed by phagocytes, primarily in the spleen. A microliter of circulating blood contains between 150,000 and 450,000...
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...
 01:16
Clot Retraction and Fibrinolysis
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins