Related Experiment Video
Updated: Nov 26, 2025
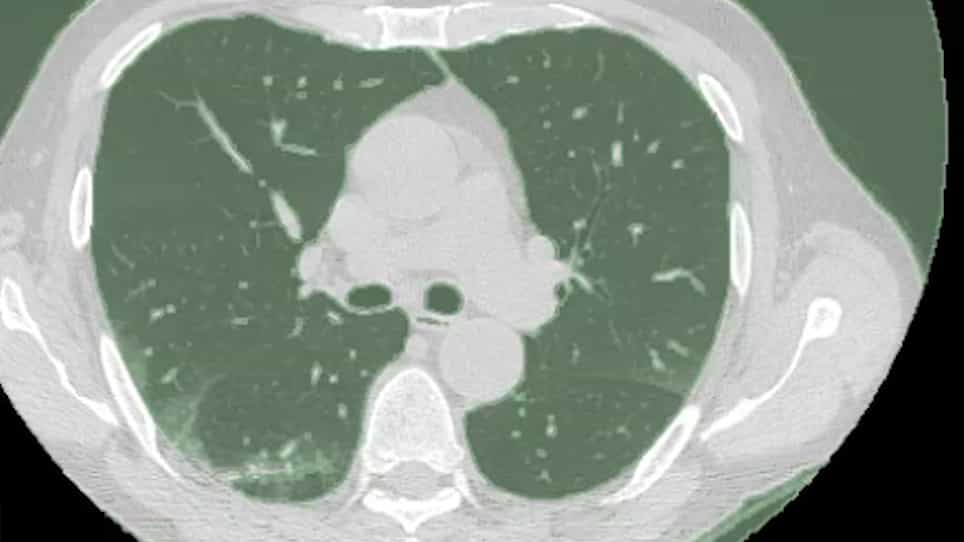

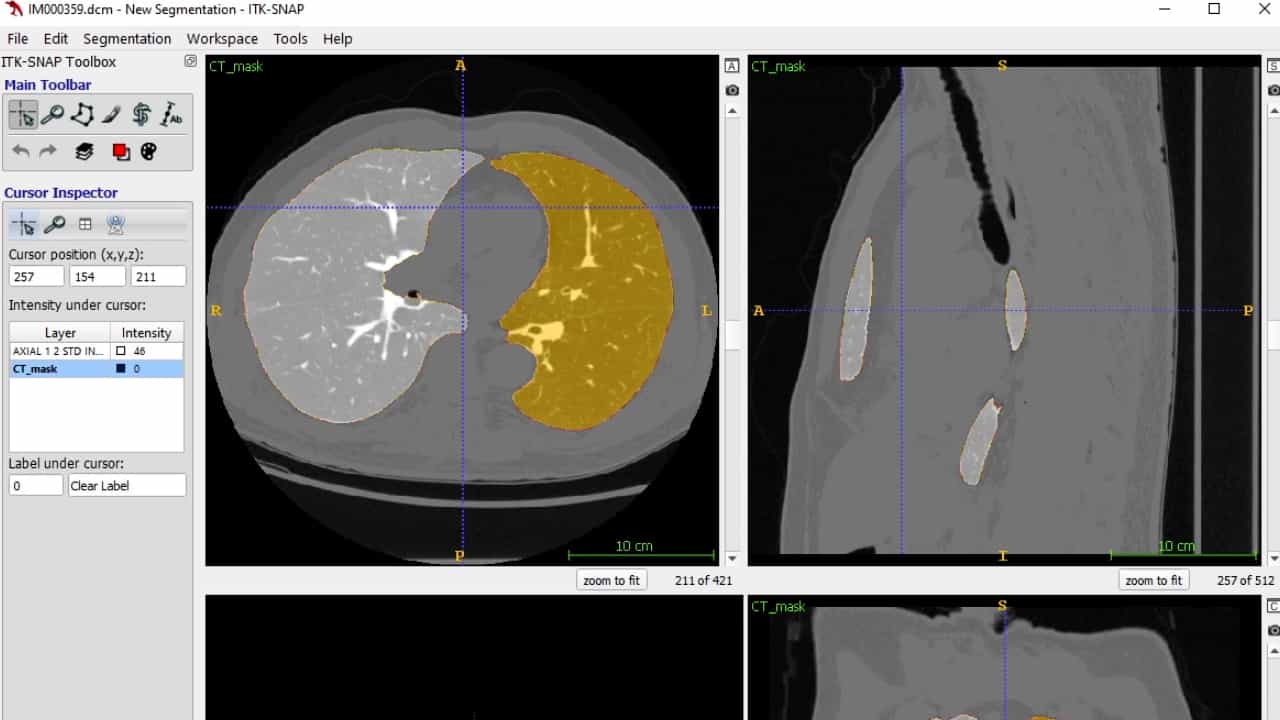
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Dyspnoea, lung function and CT findings 3 months after hospital admission for COVID-19
Tøri Vigeland Lerum1, Trond Mogens Aaløkken2,3, Eivind Brønstad4,5
1Dept of Pulmonary Medicine, Oslo University Hospital Ullevål, Oslo, Norway.

Abstract:
The long-term pulmonary outcomes of coronavirus disease 2019 (COVID-19) are unknown. We aimed to describe self-reported dyspnoea, quality of life, pulmonary function and chest computed tomography (CT) findings 3 months following hospital admission for COVID-19. We hypothesised outcomes to be inferior for patients admitted to intensive care units (ICUs), compared with non-ICU patients.Discharged COVID-19 patients from six Norwegian hospitals were enrolled consecutively in a prospective cohort study. The current report describes the first 103 participants, including 15 ICU patients. The modified Medical Research Council (mMRC) dyspnoea scale, the EuroQol Group's questionnaire, spirometry, diffusing capacity of the lung for carbon monoxide (D LCO), 6-min walk test, pulse oximetry and low-dose CT scan were performed 3 months after discharge.mMRC score was >0 in 54% and >1 in 19% of the participants. The median (25th-75th percentile) forced vital capacity and forced expiratory volume in 1 s were 94% (76-121%) and 92% (84-106%) of predicted, respectively. D LCO was below the lower limit of normal in 24% of participants. Ground-glass opacities (GGO) with >10% distribution in at least one of four pulmonary zones were present in 25% of participants, while 19% had parenchymal bands on chest CT. ICU survivors had similar dyspnoea scores and pulmonary function as non-ICU patients, but higher prevalence of GGO (adjusted OR 4.2, 95% CI 1.1-15.6) and lower performance in usual activities.3 months after admission for COVID-19, one-fourth of the participants had chest CT opacities and reduced diffusing capacity. Admission to ICU was associated with pathological CT findings. This was not reflected in increased dyspnoea or impaired lung function.
More Related Videos
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:30
Pneumonia III: Complications and Assessment
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:27
Pneumothorax-II
Clinical Manifestations: