Related Experiment Video
Updated: Nov 26, 2025
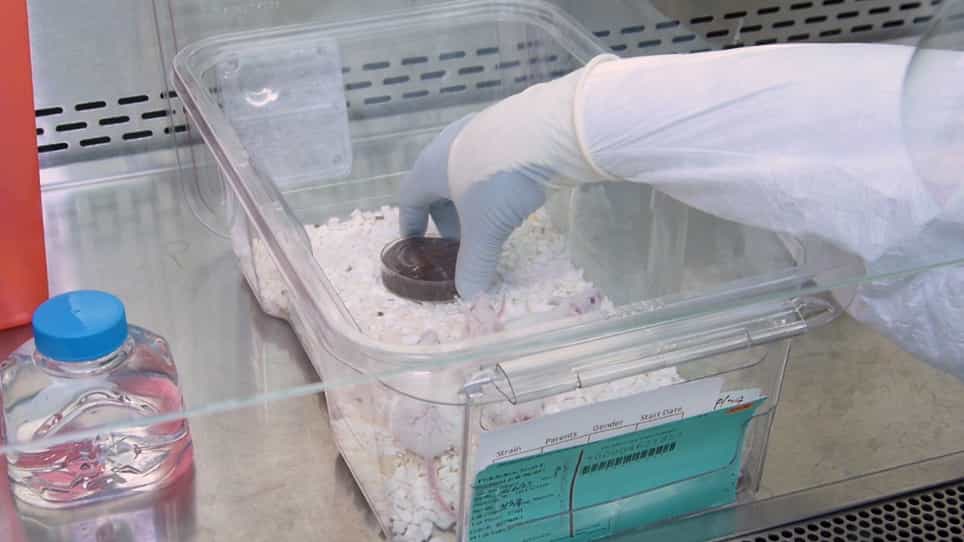

Oral Combinational Antiretroviral Treatment in HIV-1 Infected Humanized Mice
Published on: October 6, 2022
Benefits of enhanced infection prophylaxis at antiretroviral therapy initiation by cryptococcal antigen status
Sarah L Pett1,2,3, Moira Spyer2, Lewis J Haddow1
1Institute for Global Health.

Objectives:
To assess baseline prevalence of cryptococcal antigen (CrAg) positivity; and its contribution to reductions in all-cause mortality, deaths from cryptococcus and unknown causes, and new cryptococcal disease in the REALITY trial.
Design:
Retrospective CrAg testing of baseline and week-4 plasma samples in all 1805 African adults/children with CD4+ cell count less than 100 cells/microl starting antiretroviral therapy who were randomized to receive 12-week enhanced-prophylaxis (fluconazole 100 mg/day, azithromycin, isoniazid, cotrimoxazole) vs. standard-prophylaxis (cotrimoxazole).
Methods:
Proportional hazards models were used to estimate the relative impact of enhanced-prophylaxis vs. standard-cotrimoxazole on all, cryptococcal and unknown deaths, and new cryptococcal disease, through 24 weeks, by baseline CrAg positivity.
Results:
Excluding 24 (1.4%) participants with active/prior cryptococcal disease at enrolment (all treated for cryptococcal disease), 133/1781 (7.5%) participants were CrAg-positive. By 24 weeks, 105 standard-cotrimoxazole vs. 78 enhanced-prophylaxis participants died. Of nine standard-cotrimoxazole and three enhanced-prophylaxis cryptococcal deaths, seven and two, respectively, were CrAg-positive at baseline. Among deaths of unknown cause, only 1/46 standard-cotrimoxazole and 1/28 enhanced-prophylaxis were CrAg-positive at baseline. There was no evidence that relative reductions in new cryptococcal disease associated with enhanced-prophylaxis varied between baseline CrAg-positives [hazard-ratio = 0.36 (95% confidence interval 0.13-0.98), incidence 19.5 vs. 56.5/100 person-years] and CrAg-negatives [hazard-ratio = 0.33 (0.03-3.14), incidence 0.3 vs. 0.9/100 person-years; Pheterogeneity = 0.95]; nor for all deaths, cryptococcal deaths or unknown deaths (Pheterogeneity > 0.3).
Conclusion:
Relative reductions in cryptococcal disease/death did not depend on CrAg status. Deaths of unknown cause were unlikely to be cryptococcus-related; plausibly azithromycin contributed to their reduction. Findings support including 100 mg fluconazole in an enhanced-prophylaxis package at antiretroviral therapy initiation where CrAg screening is unavailable/impractical.


Related Concept Videos
 01:10
Retrovirus Life Cycles
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...