Related Experiment Video
Updated: Nov 26, 2025


Author Spotlight: Advancements in Retroperitoneal Approach for Necrotizing Pancreatitis
Published on: March 15, 2024
Groove pancreatitis has a spectrum of severity and can be managed conservatively
Kohtaro Ooka1, Harkirat Singh2, Matthew G Warndorf3
1New York University, Division of Gastroenterology and Hepatology, USA.

Background & Aims:
The natural history of groove pancreatitis is incompletely characterized. Published literature suggests a high rate of surgery. We describe the short- and long-term outcomes in a cohort of patients with groove pancreatitis treated at our institution.
Methods:
Medical records of patients hospitalized in the University of Pittsburgh Medical Center system from 2000 to 2014 and diagnosed with groove pancreatitis based on imaging were retrospectively reviewed. Clinical presentation and outcomes during index admission and follow-up were recorded.
Results:
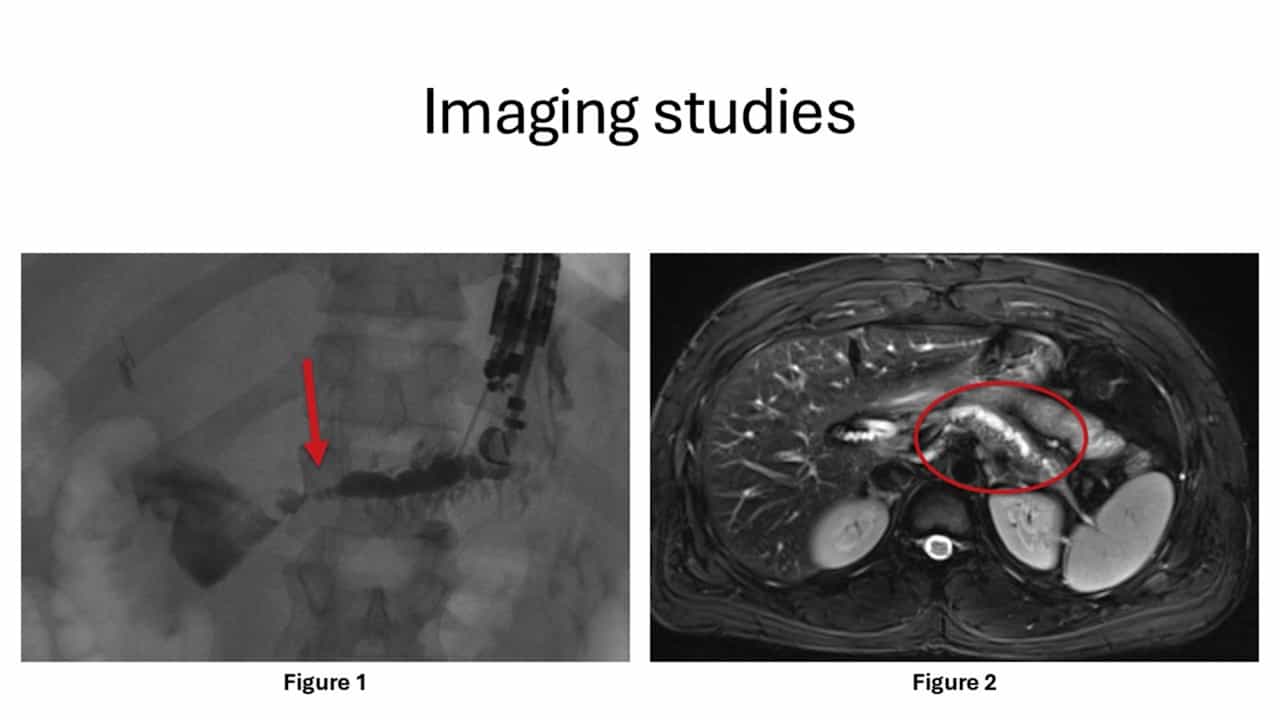
Forty-eight patients with groove pancreatitis were identified (mean age 53.2 years, 79% male). Seventy-one percent were alcohol abusers and an equal number were cigarette smokers. Prior histories of acute and chronic pancreatitis were noted in 30 (62.5%) and 21 (43.8%), respectively. Forty-four (91.7%) met criteria for acute pancreatitis during their index admission. Alcohol was the most common etiology (68.8%). No patient experienced organ failure. The most frequent imaging findings were fat stranding in the groove (83.3%), duodenal wall thickening (52.1%), and soft tissue mass/thickening in the groove (50%). Over a mean follow-up of 5.0 years, seven (14.6%) required a pancreas-related surgery. Patients had a high burden of pancreatitis-related readmissions (68.8%, 69.4/100 patient-years). Incident diabetes and chronic pancreatitis were diagnosed in 5 (13.9% of patients at risk) and 8 (29.6% of patients at risk) respectively.
Conclusions:
Groove pancreatitis has a wide spectrum of severity; most patients have mild disease. These patients have a high burden of readmissions and progression to chronic pancreatitis. A small minority requires surgical intervention.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...