Related Experiment Video
Updated: Nov 25, 2025
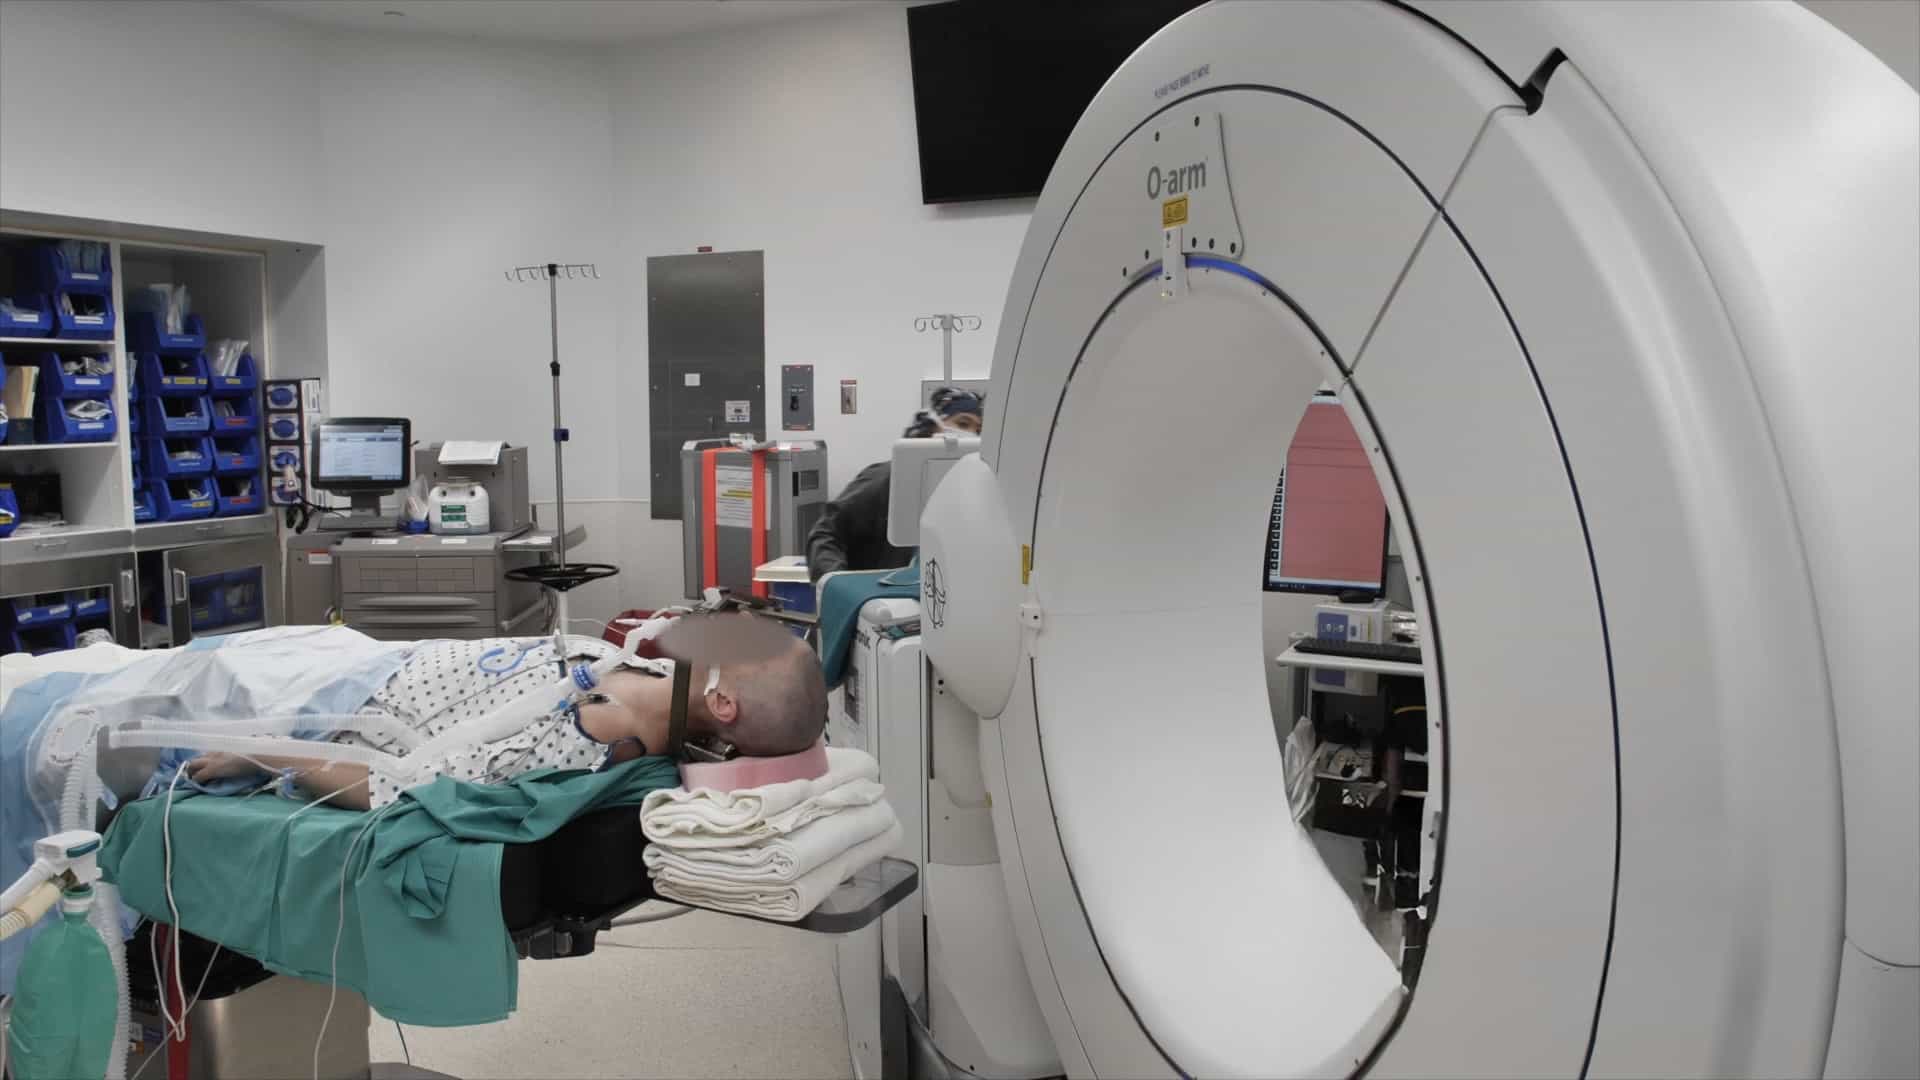
Robotic-Guided Stereoelectroencephalography for Invasive Epilepsy Monitoring
Published on: June 13, 2025
Difficult-to-Localize Epilepsy After Stereoelectroencephalography: Technique, Safety, and Efficacy of Placing
Alexander C Whiting1, Juan Bulacio1, Benjamin B Whiting2
1Cleveland Clinic Epilepsy Center, Cleveland Clinic Foundation, Cleveland, Ohio.

Background:
Stereoelectroencephalography (SEEG) is used to identify the epileptogenic zone (EZ) in patients with epilepsy for potential surgical intervention. Occasionally, the EZ is difficult to localize even after an SEEG implantation.
Objective:
To demonstrate a safe technique for placing additional electrodes in ongoing SEEG evaluations. Describe efficacy, complications, and surgical outcomes.
Methods:
An operative technique which involves maintaining previously placed electrodes and sterilely placing new electrodes was developed and implemented. All patients who underwent placement of additional SEEG electrodes during the same admission were retrospectively reviewed.
Results:
A total of 14 patients met criteria and had undergone SEEG evaluation with 198 electrodes implanted. A total 93% of patients (13/14) had nonlesional epilepsy. After unsuccessful localization of the EZ after a mean of 9.6 d of monitoring, each patient underwent additional placement of electrodes (5.5 average electrodes per patient) to augment the original implantation. At no point did any patients develop new hemorrhage, infection, wound breakdown, or require any kind of additional antimicrobial treatment. A total 64% (9/14) of patients were able to undergo surgery aimed at removing the EZ guided by the additional SEEG electrodes. A total 44% (4/9) of surgical patients had Engel class I outcomes at an average follow-up time of 11 mo.
Conclusion:
Placing additional SEEG electrodes, while maintaining the previously placed electrodes, appears to be safe, effective, and had no infectious complications. When confronted with difficult-to-localize epilepsy even after invasive monitoring, it appears to be safe and potentially clinically effective to place additional electrodes during the same admission.