Related Experiment Video
Updated: Nov 25, 2025

Ex Vivo Porcine Experimental Model for Studying and Teaching Lung Mechanics
Published on: April 19, 2024
The effects of tidal volume size and driving pressure levels on pulmonary complement activation: an observational
Friso M de Beer1,2,3, Luuk Wieske4,5,6, Gerard van Mierlo7
1Department of Intensive Care Medicine, Amsterdam UMC, University of Amsterdam, Amsterdam, The Netherlands. frisodebeer@hotmail.com.

Background:
Mechanical ventilation can induce or even worsen lung injury, at least in part via overdistension caused by too large volumes or too high pressures. The complement system has been suggested to play a causative role in ventilator-induced lung injury.
Aims And Methods:
This was a single-center prospective study investigating associations between pulmonary levels of complement activation products and two ventilator settings, tidal volume (VT) and driving pressure (ΔP), in critically ill patients under invasive ventilation. A miniature bronchoalveolar lavage (BAL) was performed for determination of pulmonary levels of C5a, C3b/c, and C4b/c. The primary endpoint was the correlation between BAL fluid (BALF) levels of C5a and VT and ΔP. Levels of complement activation products were also compared between patients with and without ARDS or with and without pneumonia.
Results:
Seventy-two patients were included. Median time from start of invasive ventilation till BAL was 27 [19 to 34] hours. Median VT and ΔP before BAL were 6.7 [IQR 6.1 to 7.6] ml/kg predicted bodyweight (PBW) and 15 [IQR 11 to 18] cm H2O, respectively. BALF levels of C5a, C3b/c and C4b/c were neither different between patients with or without ARDS, nor between patients with or without pneumonia. BALF levels of C5a, and also C3b/c and C4b/c, did not correlate with VT and ΔP. Median BALF levels of C5a, C3b/c, and C4b/c, and the effects of VT and ΔP on those levels, were not different between patients with or without ARDS, and in patients with or without pneumonia.
Conclusion:
In this cohort of critically ill patients under invasive ventilation, pulmonary levels of complement activation products were independent of the size of VT and the level of ΔP. The associations were not different for patients with ARDS or with pneumonia. Pulmonary complement activation does not seem to play a major role in VILI, and not even in lung injury per se, in critically ill patients under invasive ventilation.
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
 05:56
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Related Concept Videos
 01:24
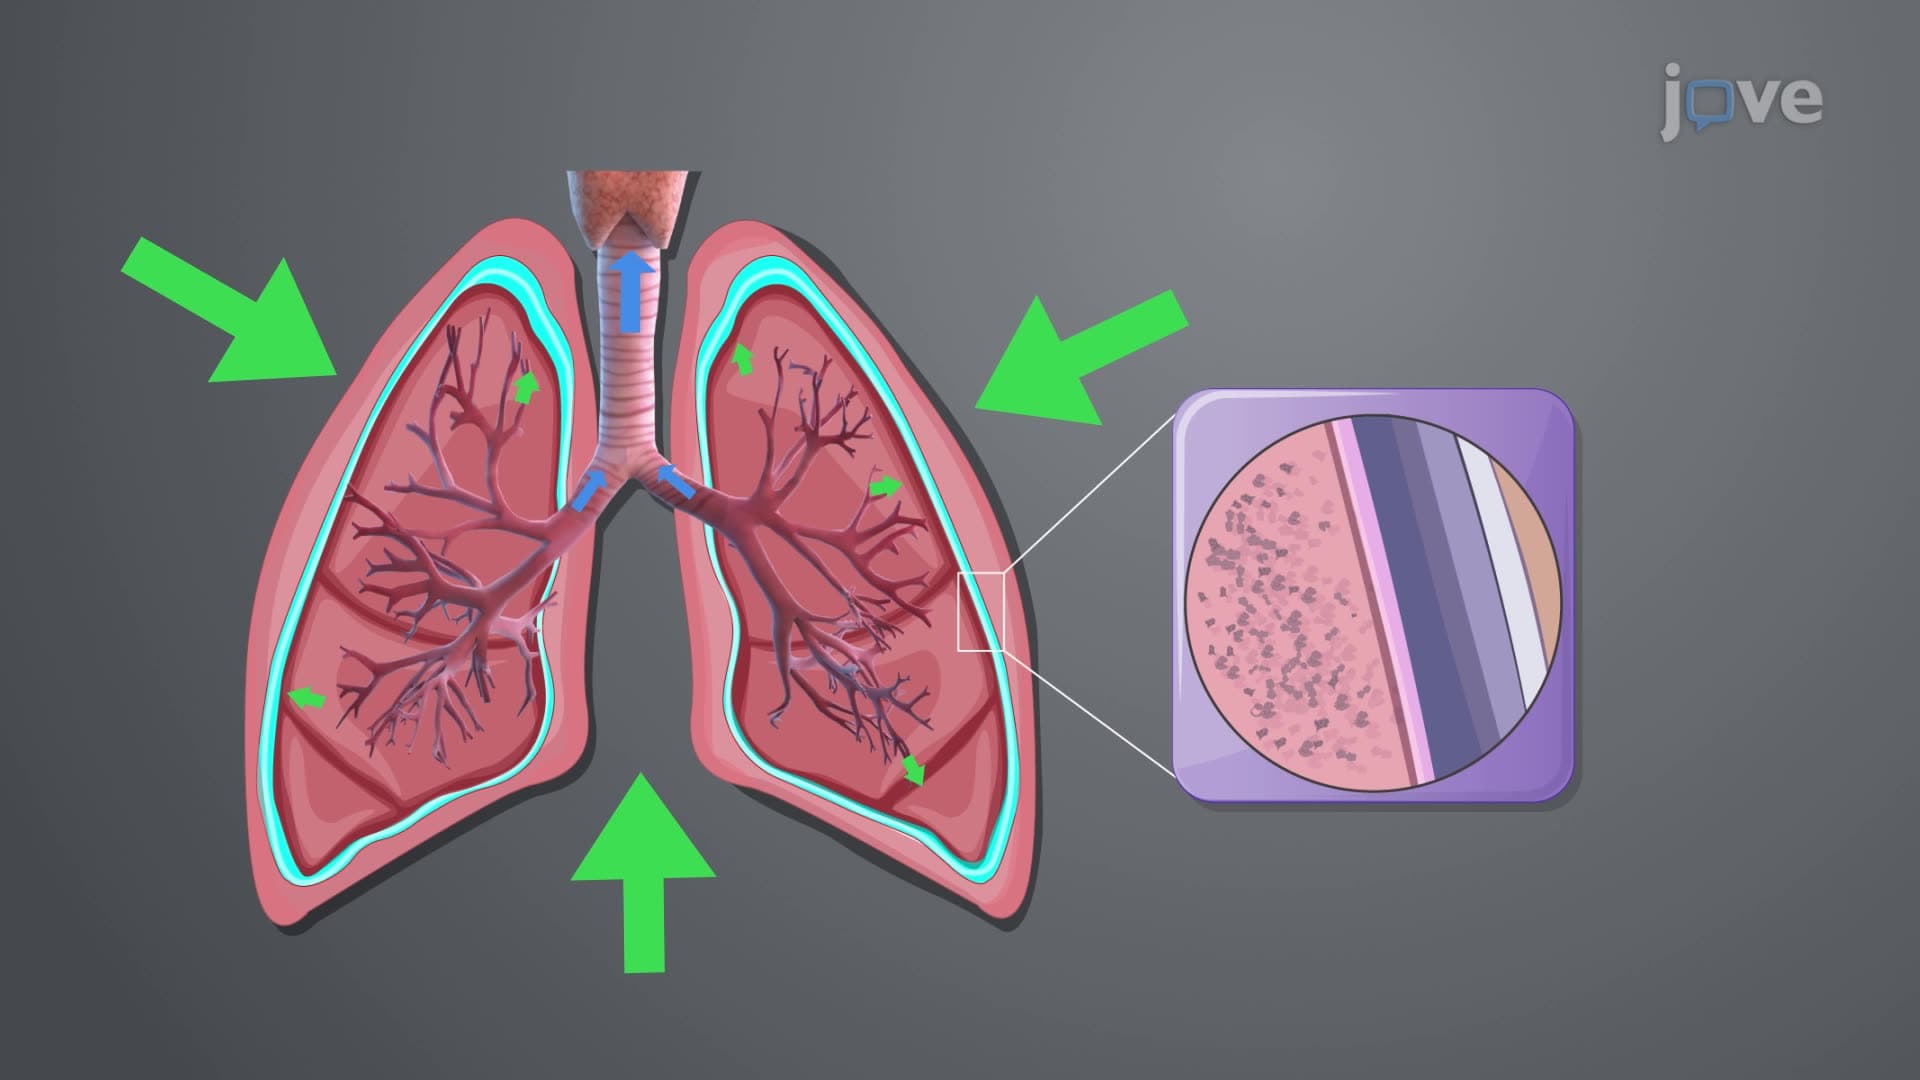
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
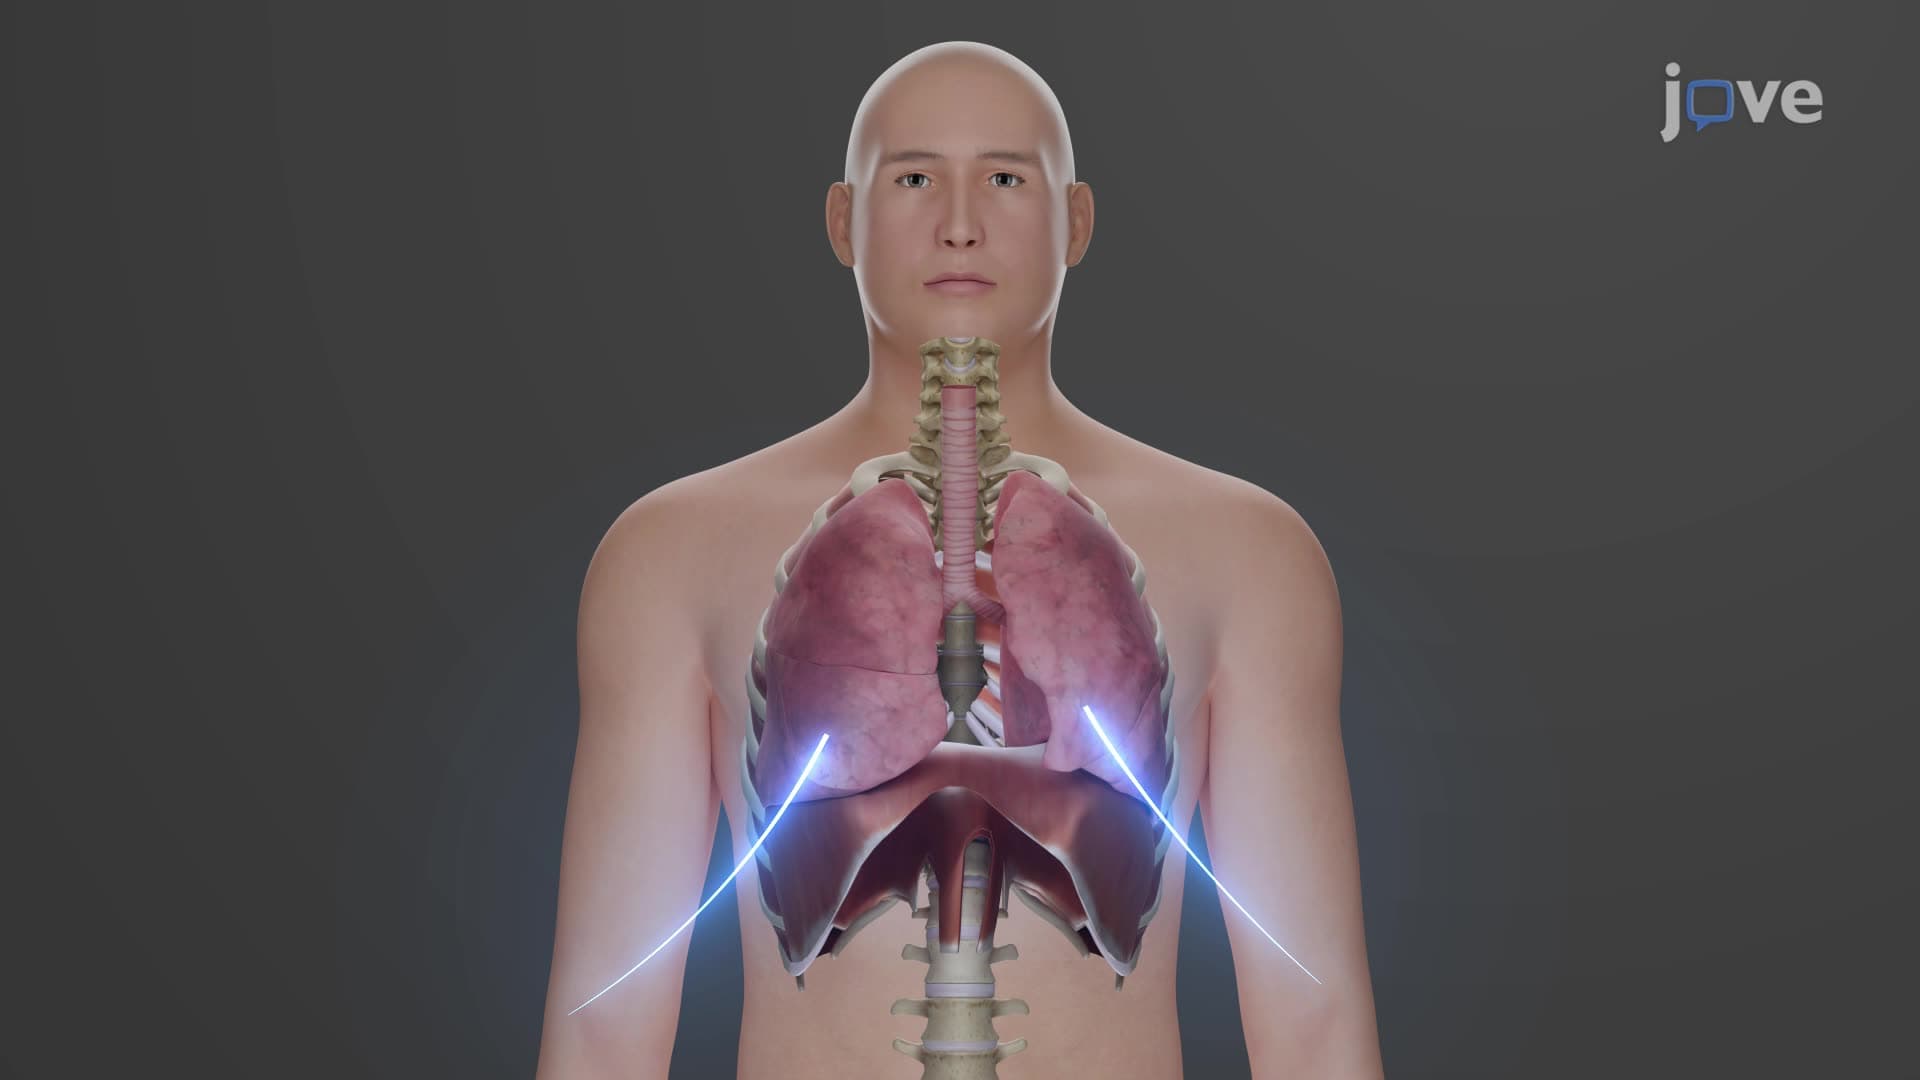
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...