Related Experiment Video
Updated: Nov 25, 2025
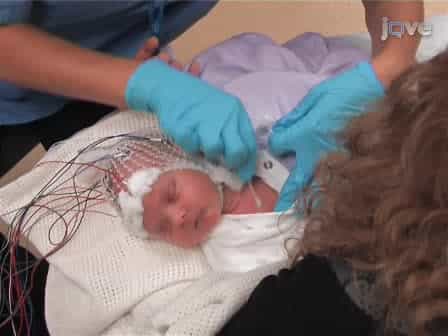

Electrophysiological Measurements and Analysis of Nociception in Human Infants
Published on: December 20, 2011
[Pediatric pain treatment and prevention for hospitalized children]
Stefan J Friedrichsdorf1,2,3, Liesbet Goubert4
1Center of Pain Medicine, Palliative Care and Integrative Medicine, University of California at San Francisco (UCSF), Benioff Children's Hospitals in Oakland and San Francisco, Kalifornien, USA. Stefan.Friedrichsdorf@ucsf.edu.

Insights
Effective pain management in children requires multimodal approaches. Evidence-based strategies for acute and chronic pediatric pain, including needle procedures, are essential for optimal care.
Area of Science:
- Pediatric Pain Management
- Evidence-Based Medicine
- Clinical Practice Guidelines
Background:
- Pediatric pain prevention and treatment are often inadequate, especially in younger children.
- Children aged 0-17 years represent a vulnerable population requiring specialized pain care.
- Current practices frequently fall short of optimal pain management for children.
Purpose of the Study:
- To outline evidence-based strategies for preventing and treating acute and chronic pain in children.
- To provide recommendations for analgesic starting doses.
- To address pain management during common procedures, including needle-based interventions.
Main Methods:
- Review of the 2019 IASP Global Year Against Pain in the Vulnerable "Factsheet Pain in Children: Management".
- Synthesis of best evidence and clinical practice for pediatric pain management.
- Elaboration on multimodal analgesia and interdisciplinary approaches.
Main Results:
- Multimodal analgesia (pharmacology, regional anesthesia, psychological, spiritual, integrative modalities) offers synergistic benefits for acute pediatric pain.
- Effective chronic pain management involves interdisciplinary rehabilitation (physical therapy, psychological treatment, mind-body techniques).
- A bundle of four modalities (topical anesthesia, comfort positioning, sucrose/breastfeeding, distraction) is recommended for all elective needle procedures in children.
Conclusions:
- Failure to implement evidence-based pain management in pediatric patients is unacceptable.
- Adhering to evidence-based practices is considered the standard of care for children.
- Improved pain prevention and treatment are critical for vulnerable pediatric populations.
Introduction:
Prevention and treatment of pain in pediatric patients compared with adults is often not only inadequate but also less often implemented the younger the children are. Children 0 to 17 years are a vulnerable population.
Objectives:
To address the prevention and treatment of acute and chronic pain in children, including pain caused by needles, with recommended analgesic starting doses.
Methods:
This Clinical Update elaborates on the 2019 IASP Global Year Against Pain in the Vulnerable "Factsheet Pain in Children: Management" and reviews best evidence and practice.
Results:
Multimodal analgesia may include pharmacology (eg, basic analgesics, opioids, and adjuvant analgesia), regional anesthesia, rehabilitation, psychological approaches, spirituality, and integrative modalities, which act synergistically for more effective acute pediatric pain control with fewer side effects than any single analgesic or modality. For chronic pain, an interdisciplinary rehabilitative approach, including physical therapy, psychological treatment, integrative mind-body techniques, and normalizing life, has been shown most effective. For elective needle procedures, such as blood draws, intravenous access, injections, or vaccination, overwhelming evidence now mandates that a bundle of 4 modalities to eliminate or decrease pain should be offered to every child every time: (1) topical anesthesia, eg, lidocaine 4% cream, (2) comfort positioning, eg, skin-to-skin contact for infants, not restraining children, (3) sucrose or breastfeeding for infants, and (4) age-appropriate distraction. A deferral process (Plan B) may include nitrous gas analgesia and sedation.
Conclusion:
Failure to implement evidence-based pain prevention and treatment for children in medical facilities is now considered inadmissible and poor standard of care.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:29
Drug Dosing: Infants and Children
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:25
Analgesia and Pain Management
 01:26
Tonsillitis II: Management