Related Experiment Video
Updated: Nov 25, 2025
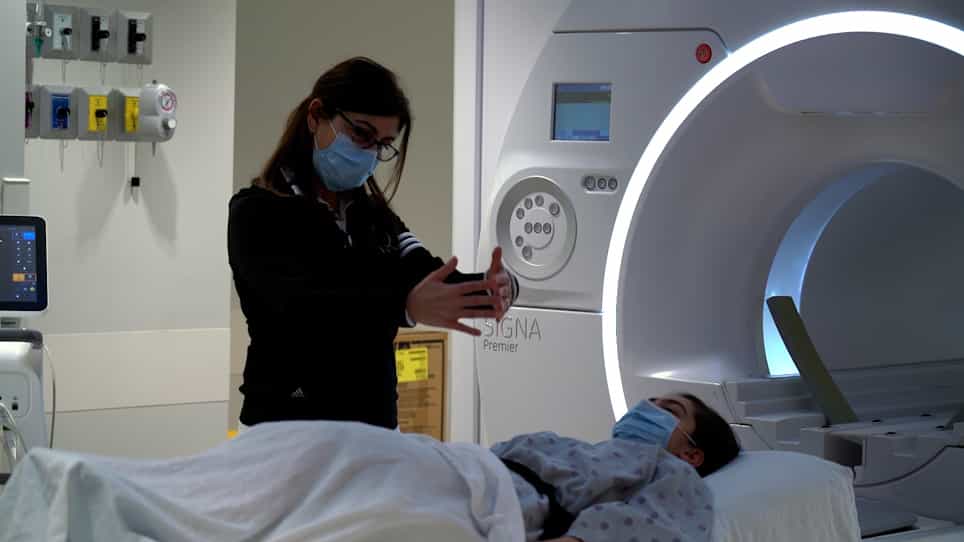

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Prevalence, Clinical Factors, and Outcomes Associated With Myocardial Infarction With Nonobstructive Coronary Artery
Katie Schmitz1, Nicole Groth2, Richard Mullvain2
1From the University of Minnesota Medical School, Duluth Campus, Duluth, MN.

Background:
Myocardial infarction with nonobstructive coronary arteries (MINOCA) is an underrecognized clinical problem in patients presenting with acute coronary syndrome. Various clinical disorders lead to MINOCA thus making treatment and diagnosis a challenge. We aimed to compare the clinical factors and outcomes of patients with MINOCA versus obstructive disease [myocardial infarction due to coronary artery disease (MI-CAD)] in a largely rural health system.
Methods:
Between May 1, 2009 and June 24, 2019, all consecutive ST-segment elevation myocardial infarction patients at Essentia Health were prospectively examined. We categorized patients into MI-CAD (obstructive plaque ≥ 50% with revascularization) or MINOCA (obstructive plaque < 50% with exclusion of other alternative cause). Outcomes included 30-day and 1-year all-cause mortality, 30-day all-cause readmission and 30-day cardiac readmission.
Results:
There were 2170 patients included in the study; 2097 (96.6 %) had MI-CAD and 73 (3.4%) met the definition of MINOCA. Within the MINOCA group, the 3 most common presentations were supply-demand mismatch (28.8%), spontaneous coronary artery dissection (9.6%), and other etiology (60.3%). Only 10 (13 %) MINOCA patients had cardiac magnetic resonance imaging studies obtained within 6 months. MINOCA patients were younger 61.6 versus 63.4 years with higher left ventricular function 51.6% versus 50.4% with less likelihood of prior myocardial infarction 4.1% versus 15.5% or congestive heart failure 2.7% versus 6.3% (P < 0.05). Compared with MI-CAD patients, MINOCA patients had similar 30-day mortality (7.1% vs. 8.2%; P = 0.70), 1-year mortality (10.4% vs. 8.2 %; P = 0.55), and 30-day cardiac readmission (8.7% vs. 9.6%; P = 0.29). MINOCA patients were less likely to be discharged on aspirin, betablockers, angiotensin-converting enzyme inhibitor/angiotensin receptor blockers, or statins (P < 0.05).
Conclusion:
Though there was no difference in readmission and mortality between MINOCA and MI-CAD; use of secondary prevention medications and cardiac rehabilitation referral was low in MINOCA patients. Prospective studies will be relevant to assess effective medical therapy to improve outcomes in MINOCA patients.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 10:03
Coronary Progenitor Cells and Soluble Biomarkers in Cardiovascular Prognosis after Coronary Angioplasty
Published on: January 28, 2020
Related Concept Videos
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:30
Coronary Artery Disease I: Introduction
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Acute Coronary Syndrome I: Introduction