Related Experiment Video
Updated: Nov 24, 2025


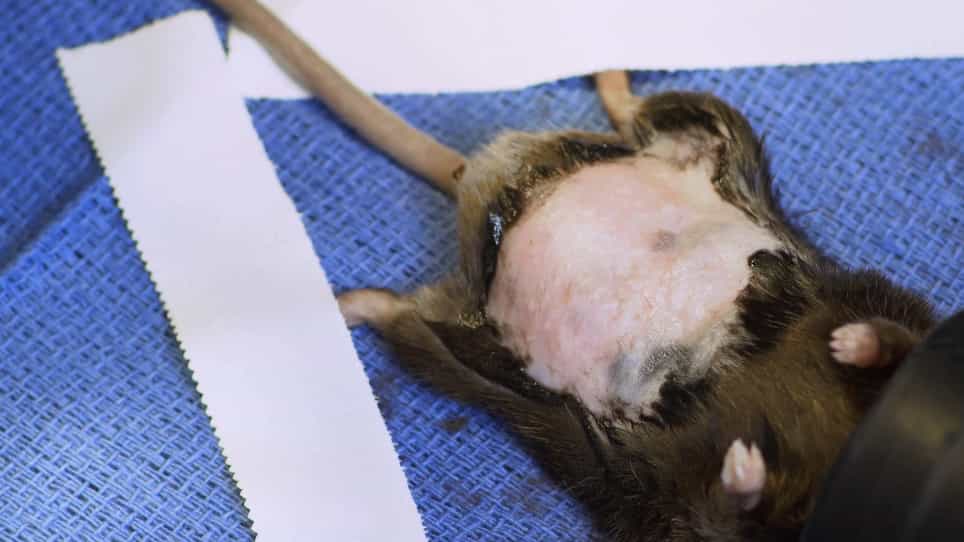
Murine Distal Colostomy, A Novel Model of Diversion Colitis in C57BL/6 Mice
Published on: July 12, 2018
Facility of Origin Predicts Mortality After Colonic Perforation
Samuel D Butensky1, Emma Gazzara1,2, Gainosuke Sugiyama1,2
1232890Donald & Barbara Zucker School of Medicine at Hofstra/Northwell, Hempstead, NY, USA.

Introduction:
Colonic perforation often requires emergent intervention and carries high morbidity and mortality. The objective of this study was to determine whether nonclinical factors, such as transition of care from outpatient facilities to inpatient settings, are associated with increased risk of mortality in patients who underwent emergent surgical intervention for colonic perforation.
Materials And Methods:
Using the 2006-2015 ACS National Surgical Quality Improvement Program database, we identified adult patients who underwent emergent partial colectomy with primary anastomosis ± protecting ostomy or partial colectomy with ostomy with intraoperative finding of wound class III or IV for a diagnosis of perforated viscus. The outcome of interest was 30-day postoperative mortality. Univariate and multivariate analyses using logistic regression were performed.
Results:
4705 patients met criteria, of which 841 (17.9%) died. Univariate analysis showed that patients who died after emergent surgery for perforated viscus were more likely to present from a chronic care facility (13.4% vs. 4.4%, P < .0001) and had longer time from admission to undergoing surgery (mean 4.1 vs. 2.0 days, P < .0001. Logistic regression demonstrated that septic shock vs. none (OR 3.60, P < .0001), sepsis vs. none (OR 1.57, P = .00045), transfer from chronic care facility vs. home (OR 1.87, P < .0001), and increased time from admission vs. operation (OR 1.01, P = .0055) were independently associated with increased risk of death.
Discussion:
Transfer from a chronic care facility was independently associated with increased mortality in patients undergoing emergent surgery for perforated viscus.

Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...