Related Experiment Video
Updated: Nov 23, 2025


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Initial Basal and Bolus Rates and Basal Rate Variability During Pump Treatment in Children and Adolescents
Günay Demir1, Yasemin Atik Altınok1, Samim Özen1
1Ege University Faculty of Medicine, Department of Pediatrics, Division of Pediatric Endocrinology, İzmir, Turkey

Insights
Basal insulin needs in type 1 diabetes vary by age, impacting pump therapy. Adjusting basal rates based on age-specific circadian profiles optimizes treatment faster and easier for children and adolescents.
Area of Science:
- Pediatric Endocrinology
- Metabolic Disorders
- Diabetes Technology
Background:
- Type 1 diabetes (T1DM) management in children using insulin pumps shows significant variation in basal insulin (BI) needs.
- BI requirements are influenced by age-specific patterns of cortisol and growth hormone secretion, affecting insulin sensitivity (e.g., dawn/dusk phenomena).
- Current methods for initiating basal rates lack evidence-based recommendations, particularly for younger children, often relying on uniform distribution or tertiles.
Purpose of the Study:
- To analyze the changes in initial, equally distributed basal insulin rates over the first year of standard insulin pump therapy in pediatric patients with T1DM.
- To investigate the impact of age-specific circadian profiles on basal insulin requirements in young individuals with T1DM.
Main Methods:
- A cohort of 154 patients with T1DM, aged 0 to <21 years at diagnosis, was studied retrospectively.
- Patients were categorized into five age groups at pump initiation: <5, 5-8, 8-15, 15-18, and >18 years.
- Hourly basal insulin rates were evaluated at pump initiation and after one year, with analysis of circadian distribution.
Main Results:
- Mean total insulin dose/kg and mean daily basal rate/kg differed significantly across the five age groups at initiation and after one year.
- A significant decrease in mean total insulin dose/kg was observed from initiation to one year of pump therapy (0.86±0.23 U/kg to 0.78±0.19 U/kg).
- The circadian distribution of basal insulin varied markedly among the different age groups, highlighting age-specific needs.
Conclusions:
- Age-specific circadian profiles are crucial considerations when initiating insulin pump therapy in pediatric patients with T1DM.
- Accounting for these profiles can lead to faster and more effective optimization of basal insulin rates.
- This approach supports personalized diabetes management tailored to the unique physiological characteristics of different pediatric age groups.
Objective:
Pump-treated children with type 1 diabetes (T1DM) have widely differing basal insulin (BI) infusion profiles for specific periods of the day. The pattern of BI requirements depends on the timing and magnitude of cortisol and growth hormone secretion within each age group. In adolescents and young adults, a decreased insulin sensitivity is seen, particularly in the early morning (dawn phenomenon) and to a lesser extent, in the late afternoon (dusk phenomenon). Different approaches exist for the inititation of basal rates. However, there is a lack of evidence-based recommendation, especially in young children. Usually the basal rates are set equally throughout day and night or the day is divided into tertiles. The aim of this study was to analyze the change of the initial, equally distributed, BI rates over the first year of standard insulin pump therapy.
Methods:
A total of 154 patients with T1DM, aged between 0 and <21 years at diagnosis, from a single center were documented. Patients were divided into five age groups according to age at pump initiation: group 1, <5 years (n=36); group 2, 5-8 years (n=20); group 3, 8-15 years (n=74); group 4, 15-18 years, (n=19); and group 5, >18 years, (n=5). Distribution of hourly basal rates at the initiation of the pump and at the end of first year were evaluated.
Results:
Median (range) age and diabetes duration was 14.46 (1.91-26.15) and 7.89 (1.16-17.15) years, respectively. Forty-four percent were male, 56% were female. Mean total insulin dose/kg in the whole cohort at the initiation and after one year of pump therapy was 0.86±0.23 U/kg and 0.78±0.19 U/kg, respectively and differed significantly between each age group (p<0.001; p<0.001). Mean daily basal rate/kg showed significant differences between the five groups (p<0.001). Circadian distribution of BI differed markedly among the five age groups.
Conclusion:
At the initiation of insulin pump therapy, circadian profiles by age group should be taken into account in pediatric patients to optimize basal rate faster and more easily.


Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:18
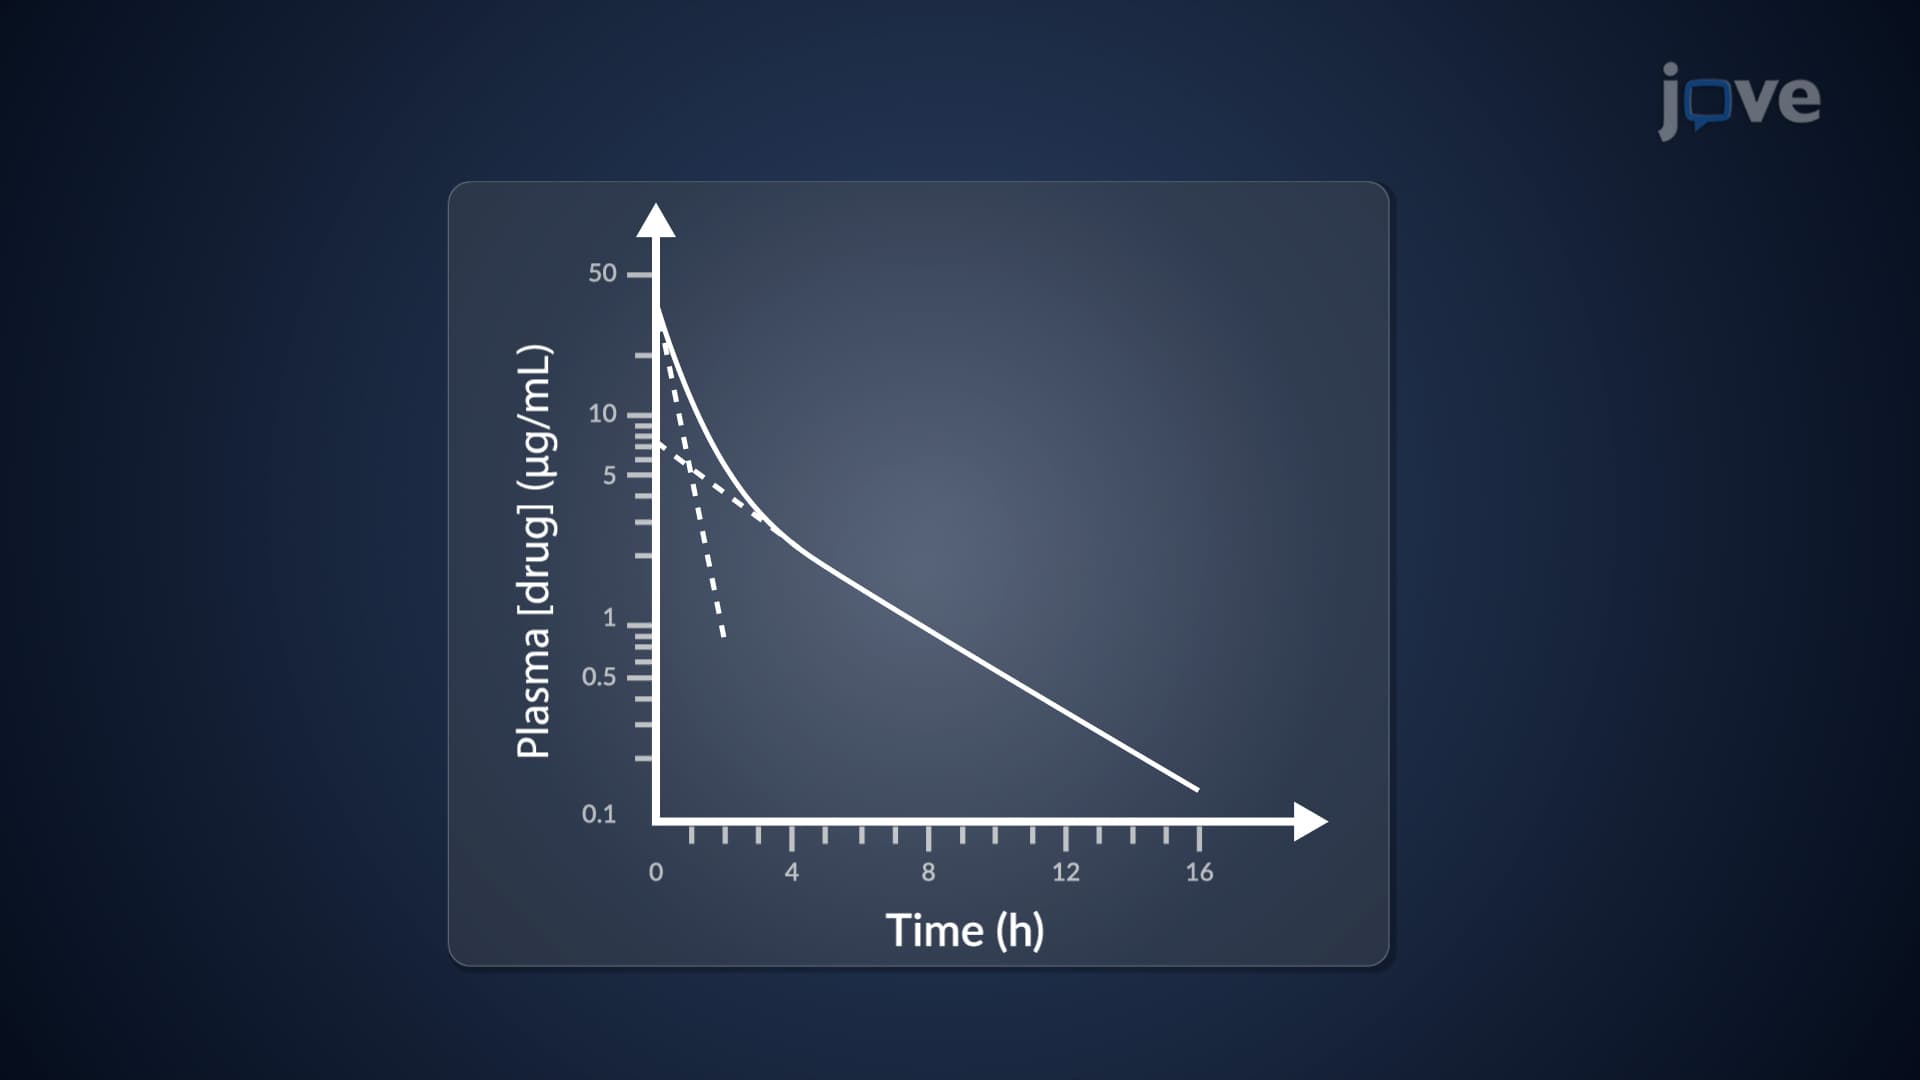
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...