Related Experiment Video
Updated: Nov 23, 2025
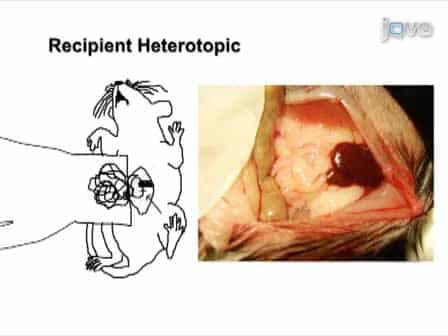

Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Postoperative outcome of tracheal resection in benign and malignant tracheal stenosis
Joana Ferreirinha1, Claudio Caviezel1, Walter Weder1
1Department of Thoracic Surgery, University Hospital of Zürich, Switzerland.

Background:
Tracheal or cricotracheal resection is the standard of care for definitive treatment of tracheal stenosis. However, the incidence is low, the management is complex, and only a few centres have reported their experience. Therefore, more clinical reports on this topic are needed.
Methods:
We performed a retrospective analysis of all patients who underwent tracheal or cricotracheal resection for malignant or benign tracheal stenosis in our institution between 2001 and 2016. Fisher’s exact test was used for analysis of complications and recurrence. P-value <0.05 was considered statistically significant.
Results:
37 patients, aged 19–74, underwent tracheal (n = 21, 56.8%) or cricotracheal (n = 16, 43.2%) resection for idiopathic (n = 15, 40.5%), neoplasm-related (n = 11, 29.7%), postintubation/-tracheotomy (n = 10, 27%), and congenital (n = 1, 2.7%) stenosis. Cervical incision was applied in 28 patients (75.7%), and an extended access (5 thoracotomy, 3 hemiclamshell, 1 partial-sternotomy) was required in 9 patients (24.3%). Mediastinal lymphadenectomy was done in 7 patients (18.9%), all with neoplasm-related stenosis. Median resection length was 2.8 cm (range 1.0–6.0), and longer than 4.0 cm in 6 cases (16.2%). Release manoeuvre was performed in 7 patients (18.9%). All patients were extubated immediately after surgery and median hospital stay was 5 days (range 3–15). Median follow-up was 6 months (range, 1-93). There was no 30-day mortality, and no dehiscence or fistula occurred at the suture line. Complications were seen in 11 patients (29.7%), significantly correlating to malignant stenosis (p = 0.011) and surgical procedure, meaning extended access (p = 0.011), mediastinal lymphadenectomy (p = 0.016), and release manoeuvres (p = 0.016). Temporary hoarseness was the most common complication (n = 5, 13.5%), but remained persistent in only one patient (n = 1, 2.7%). Recurrence was seen only in patients with idiopathic stenosis (n = 5, 13.5%).
Conclusions:
Our results confirm good efficacy for surgical resection of tracheal stenosis. The complication rate is relatively low in comparison to the literature, suggesting the importance of managing tracheal stenosis in a tertiary referral centre.

Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:23
Tracheostomy Suctioning II: Procedure
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...