
Complete Sternal Cleft Repair
Ankita Harijee1, Sundeep Vijayaraghavan1, Arjun Reddy Marathi1
1Department of Plastic & Reconstructive Surgery, Amrita Institute of Medical Sciences & Research Centre, Kochi, India.

Insights
This study presents a novel surgical technique for complete sternal cleft (SC) repair in an infant. The innovative approach utilizes multiple tissue grafts and 3D printing for successful chest wall reconstruction.
Area of Science:
- Congenital Malformations
- Pediatric Surgery
- Thoracic Reconstruction
Background:
- Sternal cleft (SC) is a rare congenital anomaly with variable presentation.
- Complete SC requires complex surgical intervention for chest wall reconstruction.
Observation:
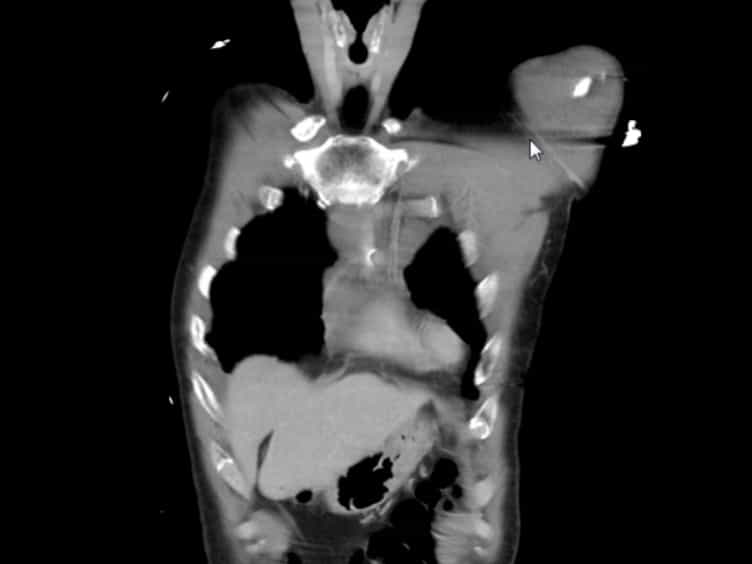
- A case of complete sternal cleft in a 9-month-old infant is detailed.
- The defect size and patient age influenced the surgical strategy.
Findings:
- A multi-component surgical technique was employed, including deep cervical fascial extension, anterior perichondrial flaps, and rib grafting.
- The reconstruction incorporated the xiphoid process and was covered by bilateral pectoralis major muscle flaps.
- Three-dimensional (3D) printing facilitated preoperative planning for this complex case.
Implications:
- This surgical approach offers a viable solution for complete sternal cleft repair in pediatric patients.
- The described technique highlights the importance of tailored reconstruction strategies based on defect characteristics.
- Advanced planning tools like 3D printing can enhance outcomes in congenital chest wall deformities.
Abstract:
Sternal cleft (SC) is a rare congenital malformation which can be partial or complete. We report a case of complete SC in a 9-month-old child. Our technique involves a combination of reinforcement with the deep cervical fascial extension, followed by the anterior perichondrial flaps, bridged with the rib graft, incorporating surplus resected cartilaginous xiphoid process, and covered with the bilateral pectoralis major muscle flap for the chest wall reconstruction with 3D printing assisting preoperative planning. The size of the defect in relation to the age of presentation was a deciding factor in the adoption of this alternative surgical technique.


