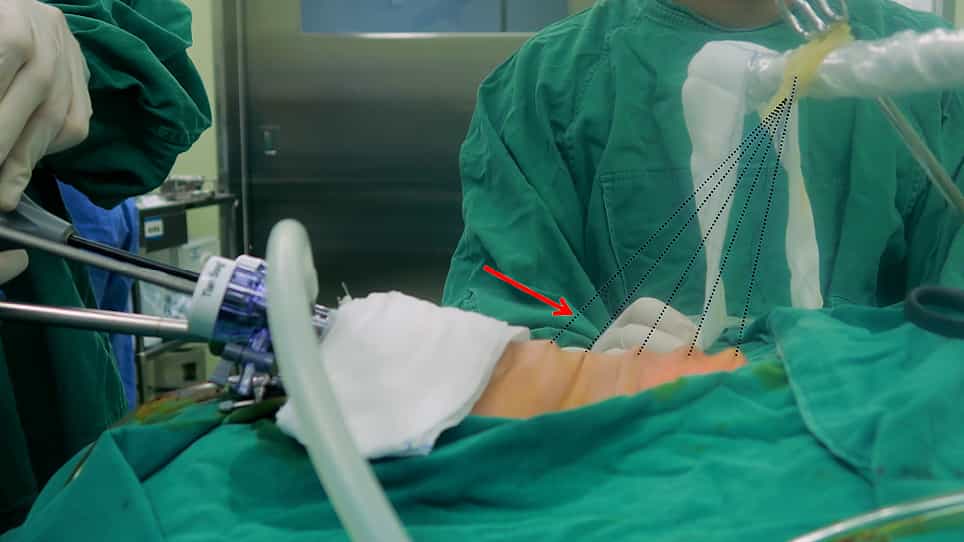
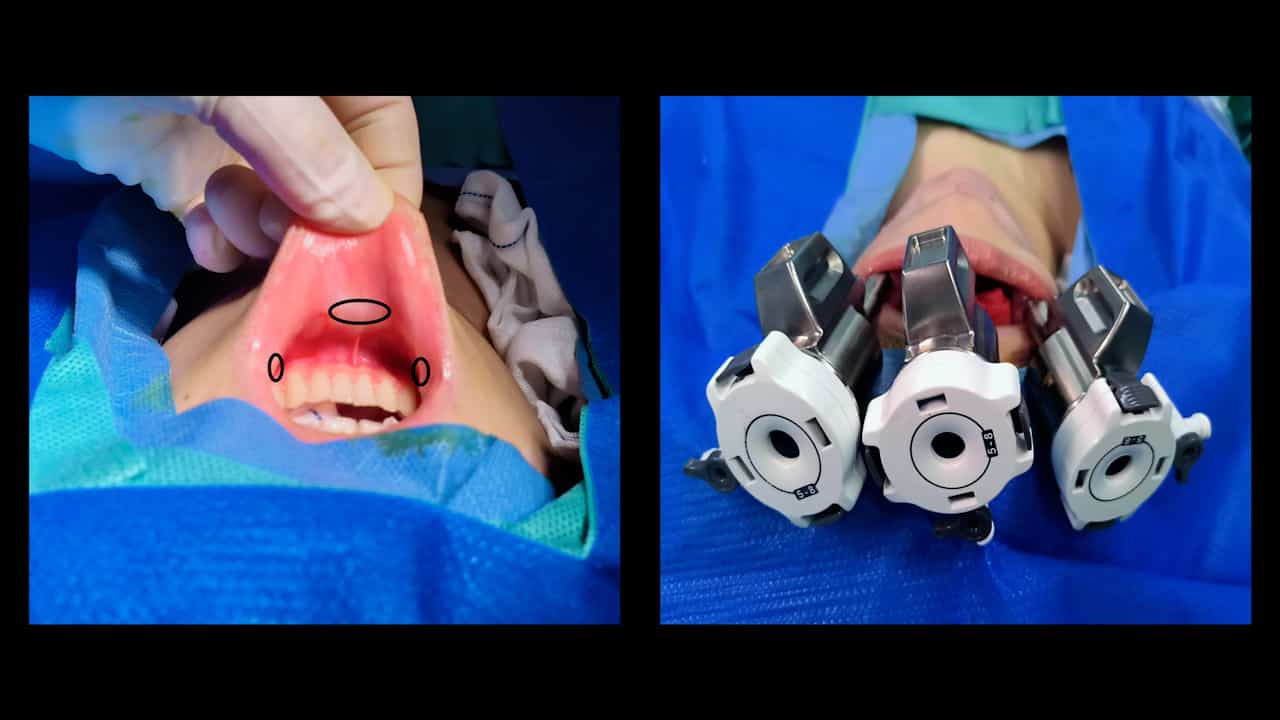
Related Experiment Video
Updated: Nov 21, 2025


Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Preservation of level IIb lymph nodes during supraomohyoid neck dissection for clinically node-negative oral squamous
Hao Wu1,2,3, Xue-Hui Sun2, Wen-Ting Hu1,2
1Weifang Medical University, College of Stomatology Weifang 261000, China.

Purpose:
To identify the significance of level IIb neck dissection for patients with clinically node-negative oral squamous cell carcinoma (OSCC).
Methods:
A retrospective study was conducted with 203 patients with OSCC with no palpable lymph nodes in neck admitted to the Department of Oral Maxillofacial-Head and Neck Oncology from January 2012 through December 2014. After the diagnostic evaluations, all patients underwent wide local dissection and periodic supraomohyoid neck dissection (SOHND). In total, 115 patients underwent SOHND with IIb lymph node dissection, and 88 patients underwent elective SOHND without IIb lymph node dissection. The incidence of level IIb lymph node metastasis was evaluated by pathological and immunohistological analyses. The results were analyzed with independent sample t-tests. The incidence of complications (mainly scapular syndrome) and IIb lymph node metastasis rate (mainly for the preserving IIb group) were analyzed.
Results:
In total, 7 (6.09%) of the 115 patients who underwent SOHND had level IIb lymph nodes involvement. After 3 years of follow-up, 83 (72.17%) patients who underwent SOHND had different degrees of scapular syndrome, and 27 (32.53%) patients who underwent SOHND improved through rehabilitation training but did not fully recover. Four (4.55%) patients who underwent elective SOHND (preserving IIb) developed scapular syndrome and recovered through rehabilitation after surgery. The 3-year overall survival rate of the 115 patients was 86.09%, and the 3-year overall survival rate of the 88 patients who underwent elective SOHND (preserving IIb) was 84.09%. There were no significant differences between the two groups (P > 0.05).
Conclusion:
Patients with clinically N0 OSCC have a low rate of level IIb lymph node metastasis. Level IIb lymph nodes resection are not necessary during SOHND, which thereby protects the accessory nerve and its branches from damage and improves patient quality of life.