Related Experiment Video
Updated: Nov 21, 2025


Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
A narrative review of gallbladder adenomyomatosis: what we need to know
Kit-Fai Lee1, Esther H Y Hung2, Howard H W Leung3
1Division of Hepatobiliary and Pancreatic Surgery, Department of Surgery, Prince of Wales Hospital, the Chinese University of Hong Kong, Hong Kong, China.

Abstract:
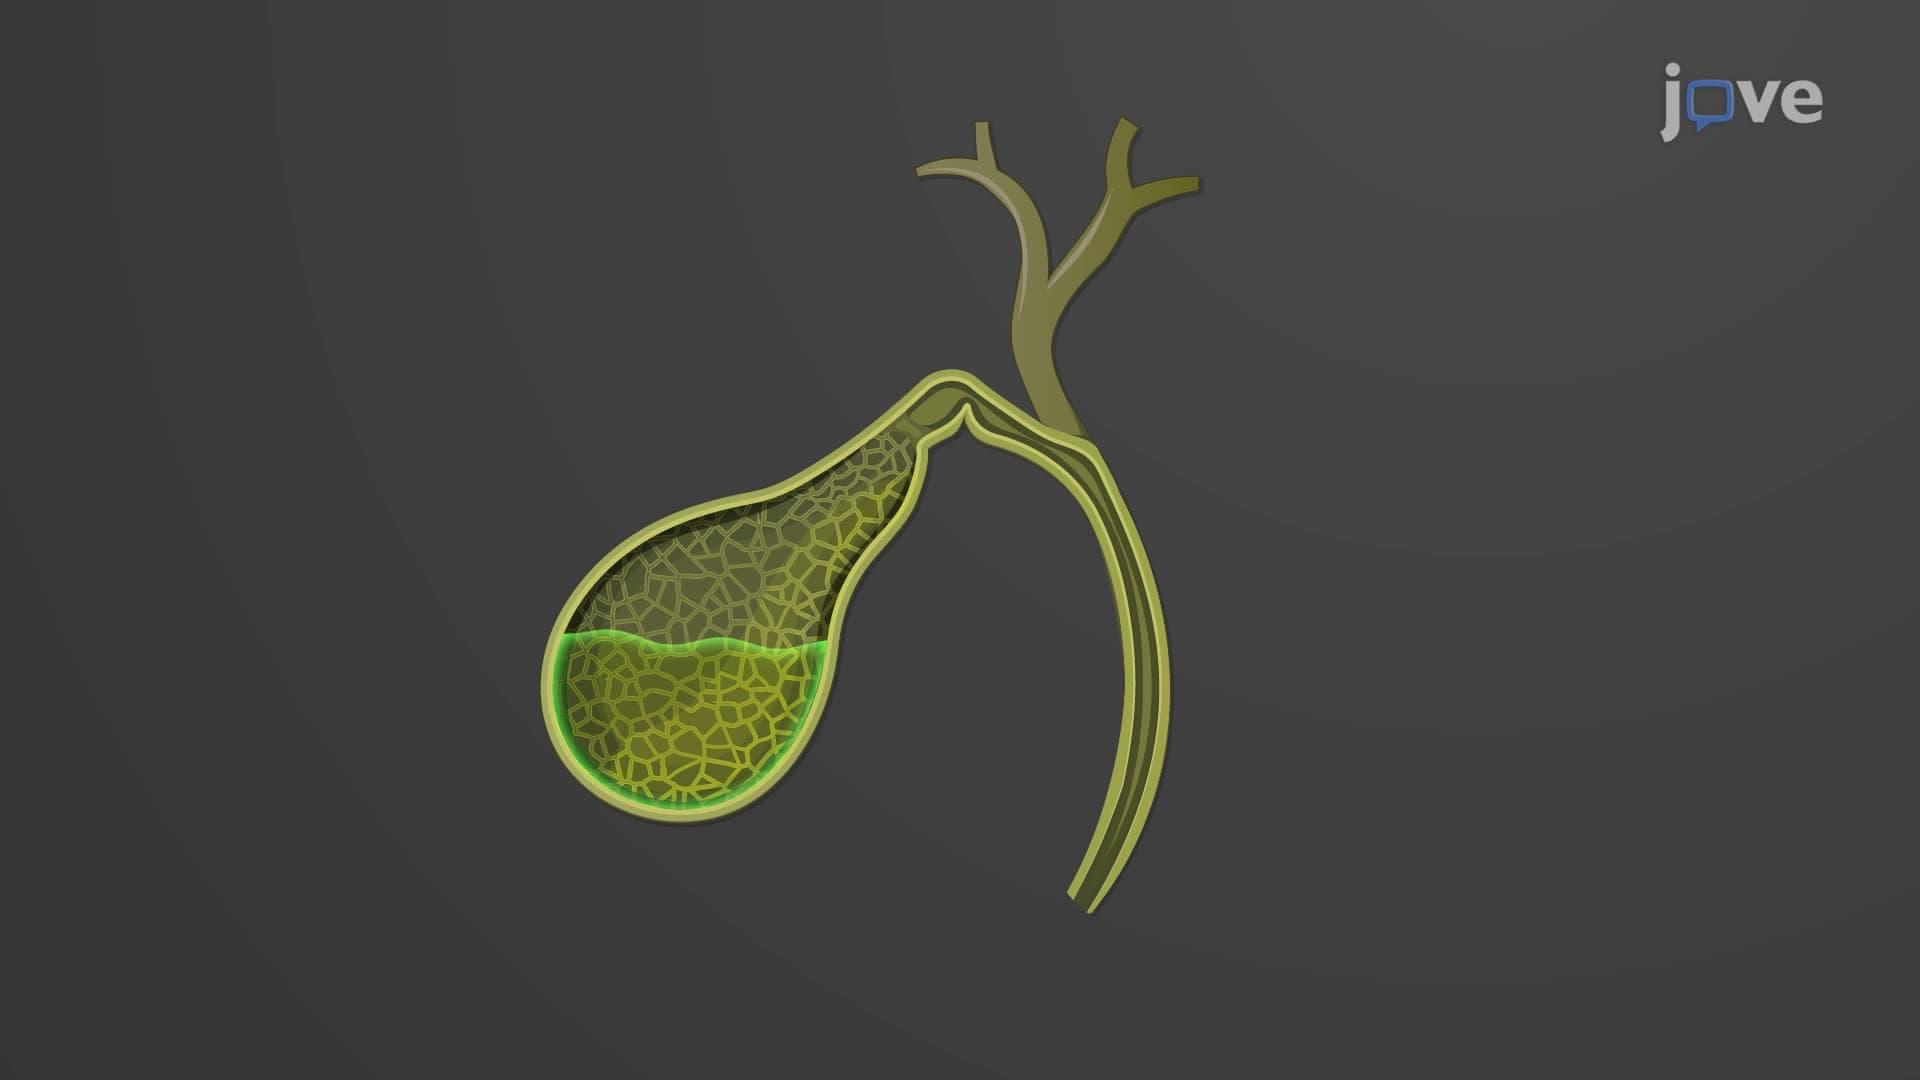
Gallbladder adenomyomatosis (GA) is increasingly encountered in clinical practice due to increasing use of imagings especially ultrasound (US). Clinicians need to know what is the implication of this condition and its proper management. GA is a degenerative and proliferative disease characterized by excessive epithelial proliferation associated with hypertrophy of muscularis propria. This leads to outpouchings of mucosa into or beyond the muscle layer forming intramural diverticula recognized as Rokitansky-Aschoff sinuses (RAS). Three types of GA are recognised: fundal, segmental and diffuse type. In fundal GA, there is focal thickening involving the GB fundus. In segmental GA, there is circumferential overgrowth of the GB wall that leads to formation of compartments. In diffuse GA, there is disseminated thickening and irregularity of the mucosa and muscularis. The pathogenesis of GA is unknown. It commonly occurs in middle age with equal sex distribution. Diagnosis of GA is by imagings showing thickened gallbladder wall containing cysts. Characteristic features are "comet-tail" artefacts and "twinkling" artefacts on US, "pearl-necklace sign" on magnetic resonance imaging (MRI) and "rosary sign" on computed tomography (CT). Cholecystectomy should be offered for symptomatic GA of any type. For asymptomatic GA, cholecystectomy may be considered for segmental type for its increased risk of malignancy and for diffuse type for its difficult visualization of any coexisting malignancy. Asymptomatic fundal GA can be safely observed with US. How frequent and how long should a fundal GA be monitored with US remains unknown. In case of diagnostic doubt, cholecystectomy should always be offered to avoid overlooked malignancy.