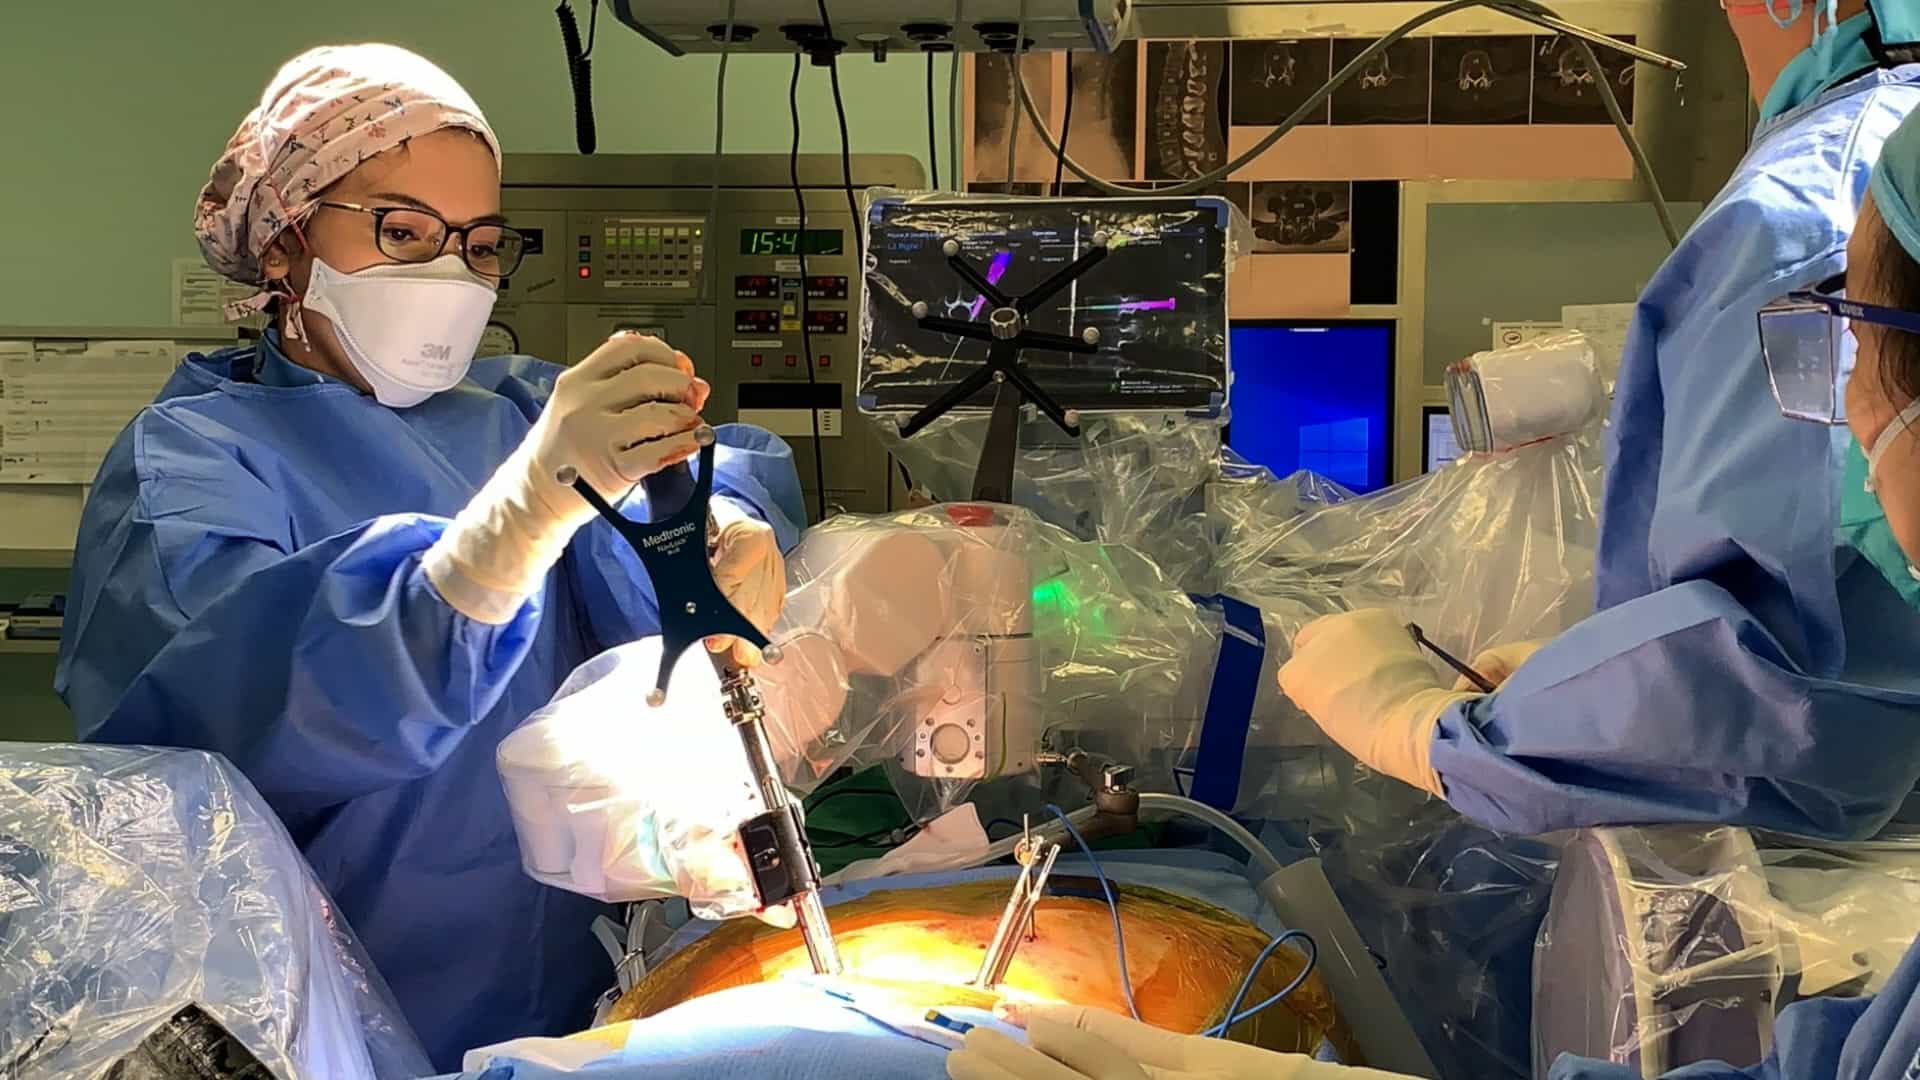
Related Experiment Video
Updated: Nov 21, 2025
Diagnosis and Surgical Treatment of Human Brucellar Spondylodiscitis
Published on: May 23, 2021
One-stage oblique lateral corridor antibiotic-cement reconstruction for Candida spondylodiscitis in patients with
Z Wang1, V T Truong1, D Shedid2
1Division of Orthopedics, Centre Hospitalier de l'Université de Montréal (CHUM), University of Montreal, 1051 Sanguinet Street, Montreal, QC H2X 3E4 Canada.

Abstract:
Fungal spondylodiscitis is rare (0.5%-1.6% of spondylodiscitis) and mainly caused by Candida albicans. Surgical intervention in spondylodiscitis patients is indicated for compression of neural elements, spinal instability, severe kyphosis, failure of conservative management and intractable pain. However, there is no evidence-based optimal surgical approach for spondylodiscitis. There have been only case reports of surgical treatment for Candida spondylodiscitis. We evaluated the preliminary results of the efficacy and safety of one-stage debridement via oblique lateral corridor with interbody fusion (OLIF) using stand-alone cement reconstruction after debridement for the treatment of Candida spondylodiscitis in patients with major co-morbidities. Five patients (4 males, 1 female, mean age: 64.2 years) suffering from Candida albicans lumbar spondylodiscitis who underwent this procedure were studied. Their predominant symptoms were unremitting back and leg pain and all had pre and postoperative anti-fungal therapy under microbiologist supervision. The operative time ranged from 137minutes to 260minutes (mean: 213.4minutes). The mean blood loss was 160mL (range: 100-200mL). There were no perioperative complications. At follow-up all showed major improvement in pain and ambulatory status. CT scan showed radiological stability for all patients at 6-12 months. Our preliminary results showed stand-alone anterior debridement and spinal re-construction with cement through mini-open OLIF approach might be a safe and effective option for patients with spinal fungal infection and major comorbidities.
Insights
This study suggests a minimally invasive surgical technique, oblique lateral corridor with interbody fusion (OLIF), may be safe and effective for treating fungal spondylodiscitis, particularly in patients with Candida albicans infection and significant health issues.
Area of Science:
- Spine Surgery
- Infectious Diseases
- Orthopedics
Background:
- Fungal spondylodiscitis is a rare spinal infection, primarily caused by Candida albicans.
- Surgical intervention is often necessary for spinal instability, neural compression, or intractable pain.
- Optimal surgical approaches for fungal spondylodiscitis remain undefined, with limited evidence beyond case reports.
Purpose of the Study:
- To evaluate the preliminary efficacy and safety of a one-stage debridement and stand-alone cement reconstruction via oblique lateral corridor with interbody fusion (OLIF).
- To assess this minimally invasive approach for treating Candida albicans spondylodiscitis in patients with major comorbidities.
Main Methods:
- A retrospective study of five patients with Candida albicans lumbar spondylodiscitis and major comorbidities.
- Patients underwent a one-stage debridement and stand-alone cement reconstruction using a mini-open OLIF approach.
- All patients received pre- and postoperative antifungal therapy under microbiologist supervision.
Main Results:
- The OLIF procedure demonstrated acceptable operative times and minimal blood loss without perioperative complications.
- All patients experienced significant improvement in pain and ambulatory status post-surgery.
- Radiological stability was confirmed in all patients at 6-12 months post-procedure via CT scan.
Conclusions:
- Preliminary findings suggest that stand-alone anterior debridement and spinal reconstruction with cement via a mini-open OLIF approach is a potentially safe and effective option.
- This technique may be particularly beneficial for patients with spinal fungal infections and significant comorbidities, offering a less invasive alternative.