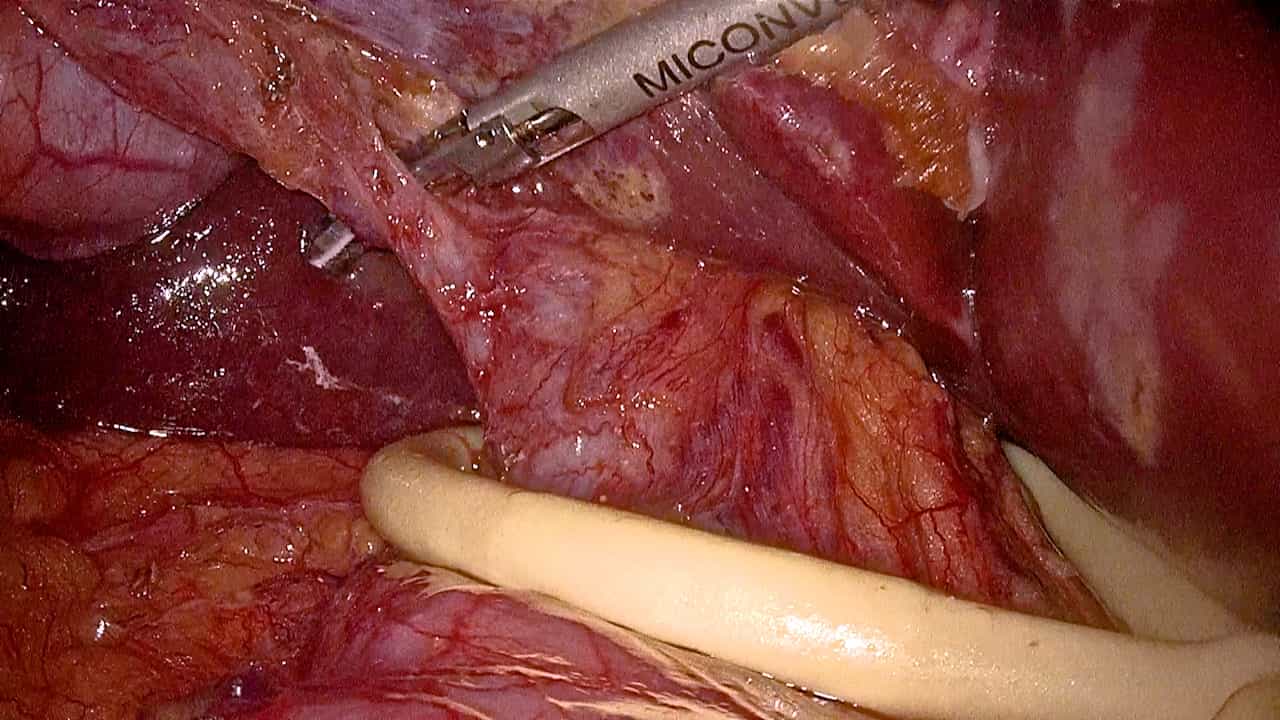
Simple transabdominal minimally invasive direct coronary artery bypass surgery with right gastroepiploic artery
Wei-Guang Chen1, Ye-Yang Wang1, Da-Peng Wang1
1Department of Cardiovascular Surgery, The Fourth Affiliated Hospital of Harbin Medical University, Harbin, Heilongjiang, China.

Insights
This study presents a minimally invasive bypass surgery for right coronary artery disease, offering a safe alternative for patients resistant to other treatments. The transabdominal approach avoids sternotomy, reducing complications and future surgical risks.
Area of Science:
- Cardiovascular Surgery
- Minimally Invasive Cardiac Surgery
- Coronary Artery Bypass Grafting
Background:
- Isolated right coronary artery disease poses treatment challenges, especially in drug-resistant or interventional therapy-intolerant patients.
- Traditional bypass grafting often involves cardiopulmonary bypass and median sternotomy, carrying significant risks and potential complications.
Observation:
- Three patients with isolated right coronary artery disease underwent transabdominal small incision bypass grafting of the right gastroepiploic artery to the posterior descending branch.
- The procedure was performed without cardiopulmonary bypass, utilizing a minimally invasive approach.
Findings:
- All three patients experienced smooth discharge without complications.
- Follow-up at three months showed unobstructed myocardial bridges and good cardiac function.
- The transabdominal approach resulted in minimal injury and avoided sternum and pericardium adhesion issues.
Implications:
- This technique offers a viable, less invasive alternative for specific coronary artery disease patient populations.
- Avoiding thoracotomy and cardiopulmonary bypass reduces surgical risk and recovery time.
- This approach is particularly beneficial for patients requiring reoperation, circumventing risks associated with median sternotomy.
Abstract:
For three patients with isolated right coronary artery disease who had drug resistance and were intolerant to interventional therapy, simple transabdominal small incision bypass grafting of the right gastroepiploic artery and the posterior descending branch of the right coronary artery was conducted without cardiopulmonary. All three patients were discharged smoothly without complications, and were followed up for three months, during which time the myocardial bridges were unobstructed and the cardiac functions were good. The surgery needs no thoracotomy and the injury is small, and avoids influences of sternum and pericardium adhesion on other cardiac surgery in the future. The risk of median sternotomy can be avoided for patients undergoing reoperation for coronary artery bypass surgery.