Related Experiment Video
Updated: Nov 19, 2025


Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Use of the Urine-to-Plasma Urea Ratio to Predict ADPKD Progression
Judith E Heida1, Ron T Gansevoort1, A Lianne Messchendorp1
1Department of Nephrology, University Medical Center Groningen, University of Groningen, Groningen, The Netherlands.

Insights
The urine-to-plasma urea ratio can predict autosomal dominant polycystic kidney disease (ADPKD) progression. This simple ratio, reflecting kidney concentrating ability, aids in identifying patients at risk for faster disease decline.
Area of Science:
- Nephrology
- Urology
- Biochemistry
Background:
- Autosomal dominant polycystic kidney disease (ADPKD) progression is challenging to predict, particularly in early stages.
- Cyst growth in ADPKD diminishes urine-concentrating capacity, suggesting a potential marker for disease monitoring.
- The urine-to-plasma urea ratio may serve as a surrogate marker for urine-concentrating capacity and ADPKD progression.
Purpose of the Study:
- To investigate the urine-to-plasma urea ratio as a predictor of disease progression in ADPKD.
- To validate the urine-to-plasma urea ratio as a marker of maximal urine-concentrating capacity.
- To compare the predictive value of the urine-to-plasma urea ratio with established ADPKD risk factors.
Main Methods:
- Calculated urine-to-plasma urea ratio from spot urine and plasma urea concentrations.
- Validated the ratio in 30 ADPKD patients during a water deprivation test.
- Assessed the association with estimated glomerular filtration rate (eGFR) slope in 583 ADPKD patients using multivariable regression.
- Compared the ratio with sex, age, baseline eGFR, Mayo Clinic height-adjusted total kidney volume class, and PKD gene mutation.
Main Results:
- Maximal urine-concentrating capacity strongly correlated with the urine-to-plasma urea ratio (R=0.90).
- The ratio was significantly associated with the rate of eGFR decline (β=0.58, P=0.02).
- A 10-unit decrease in the ratio increased the odds of rapidly progressive disease by 1.35 (P<0.001).
- A combined risk score including the ratio, kidney volume, and PKD mutation improved prediction of rapid progression.
Conclusions:
- The urine-to-plasma urea ratio is a valuable, routinely measurable marker for predicting ADPKD progression.
- This ratio provides additional predictive information beyond established risk markers.
- Incorporating the urine-to-plasma urea ratio into risk scores can enhance the identification of rapidly progressing ADPKD cases.
Background And Objectives:
Predicting disease progression in patients with autosomal dominant polycystic kidney disease (ADPKD) poses a challenge, especially in early-stage disease when kidney function is not yet affected. Ongoing growth of cysts causes maximal urine-concentrating capacity to decrease from early on. We therefore hypothesized that the urine-to-plasma urea ratio, as a reflection of the urine-concentrating capacity, can be used as a marker to predict ADPKD progression.
Design:
The urine-to-plasma urea ratio was calculated by dividing concentrations of early morning fasting spot urine urea by plasma urea. First, this ratio was validated as surrogate marker in 30 patients with ADPKD who underwent a prolonged water deprivation test. Thereafter, association with kidney outcome was evaluated in 583 patients with ADPKD with a broad range of kidney function. Multivariable mixed-model regression was used to assess association with eGFR slope, and logarithmic regression to identify patients with rapidly progressive disease, using a cutoff of -3.0 ml/min per 1.73 m2 per year. The urine-to-plasma urea ratio was compared with established predictors, namely, sex, age, baseline eGFR, Mayo Clinic height-adjusted total kidney volume class, and PKD gene mutation.
Results:
The maximal urine-concentrating capacity and urine-to-plasma urea ratio correlated strongly (R=0.90; P<0.001). Next, the urine-to-plasma urea ratio was significantly associated with rate of eGFR decline during a median follow-up of 4.0 (interquartile range, 2.6-5.0) years, both crude and after correction for established predictors (β=0.58; P=0.02). The odds ratio of rapidly progressive disease was 1.35 (95% confidence interval, 1.19 to 1.52; P<0.001) for every 10 units decrease in urine-to-plasma urea ratio, with adjustment for predictors. A combined risk score of the urine-to-plasma urea ratio, Mayo Clinic height-adjusted total kidney volume class, and PKD mutation predicted rapidly progressive disease better than each of the predictors separately.
Conclusions:
The urine-to-plasma urea ratio, which is calculated from routine laboratory measurements, predicts disease progression in ADPKD in addition to other risk markers.
Podcast:
This article contains a podcast at https://www.asn-online.org/media/podcast/CJASN/2021_01_27_CJN10470620_final.mp3.


Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:29
Urine Studies I: Urinalysis
 01:11
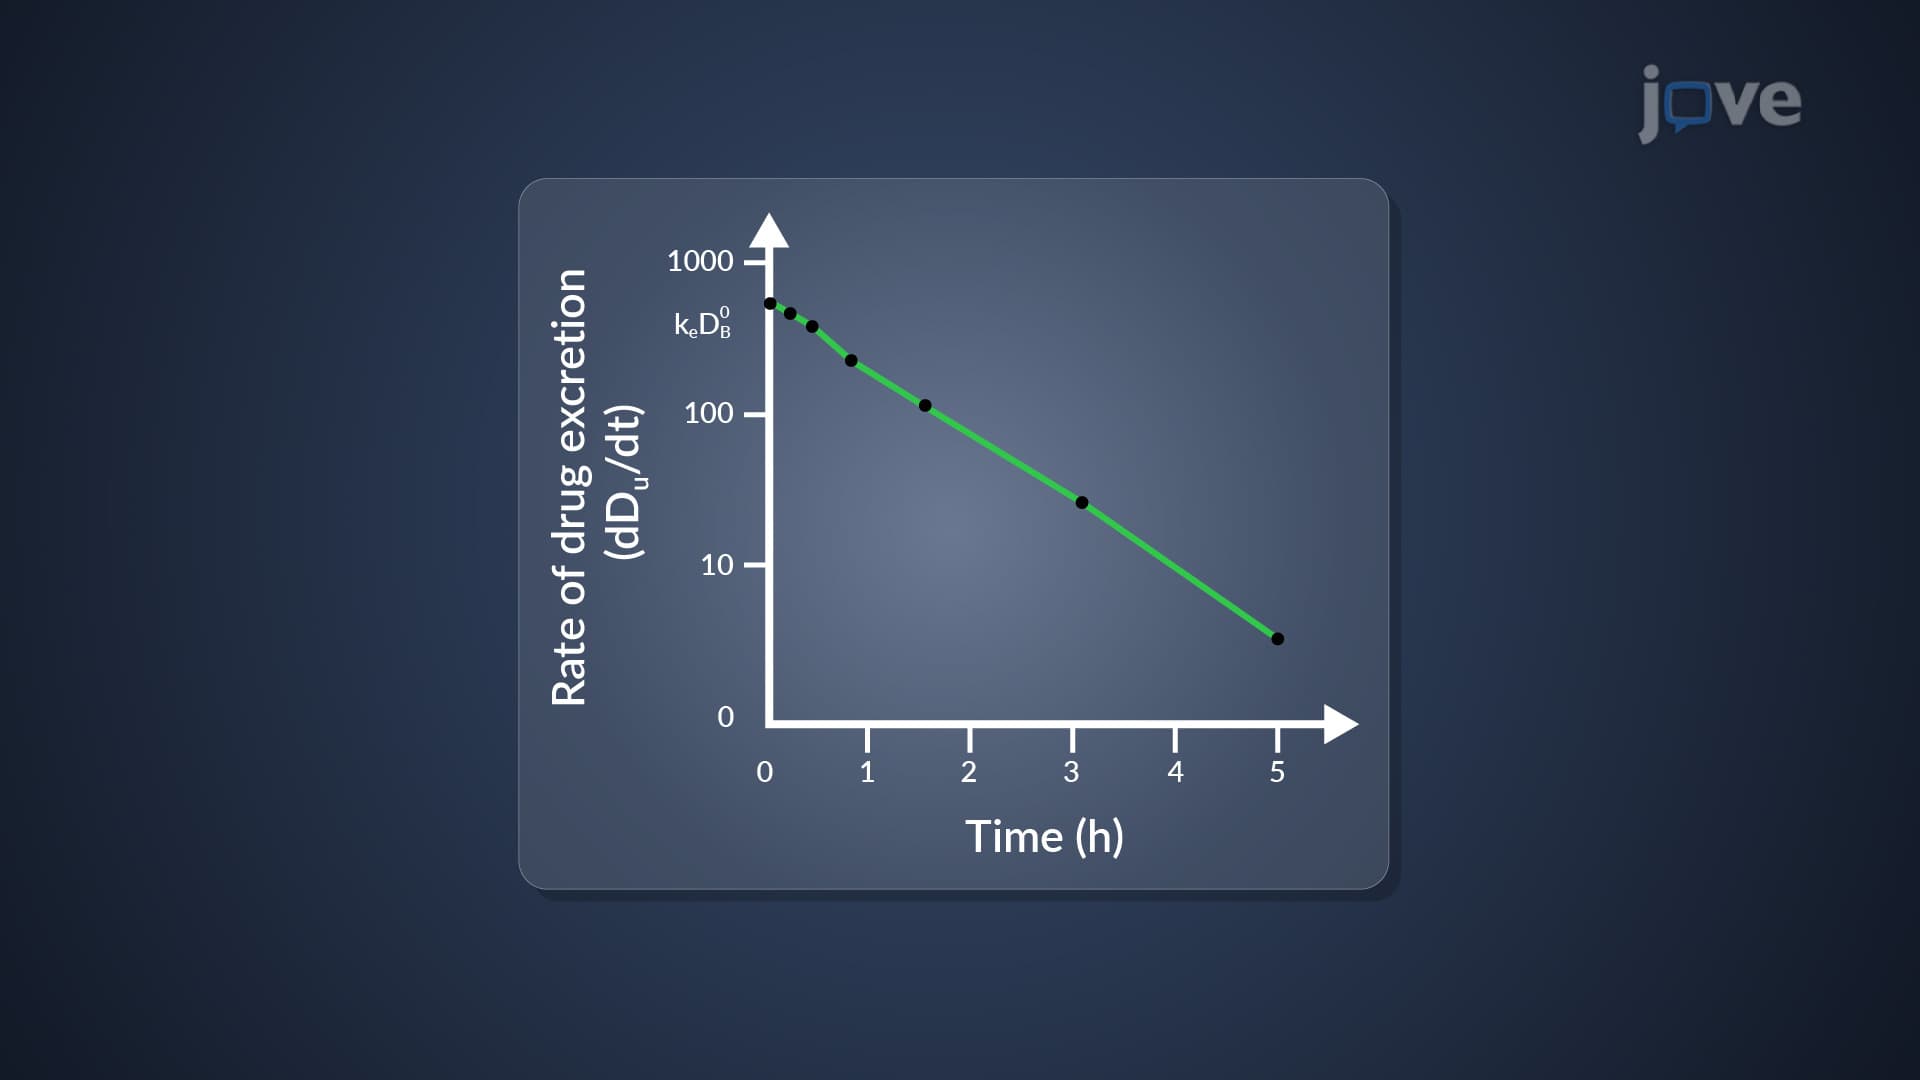
One-Compartment Open Model: Urinary Excretion Data and Determination of k