Related Experiment Video
Updated: Nov 19, 2025


Coronary Progenitor Cells and Soluble Biomarkers in Cardiovascular Prognosis after Coronary Angioplasty
Published on: January 28, 2020
Predictors of recurrent angina in patients with no need for secondary revascularization
Tian Xu1,2, Ya Li1,2, Li-Ding Zhao1,2
1Department of Cardiovascular Disease, Sir Run Run Shaw Hospital, School of Medicine, Zhejiang University, Hangzhou 310016, China.

Insights
Recurrent angina after successful coronary revascularization is predicted by female sex, older age, smoking, high LDL-C, and poor coronary blood flow. Dual antiplatelet therapy may reduce this risk.
Area of Science:
- Cardiology
- Interventional Cardiology
- Vascular Biology
Background:
- Coronary artery disease (CAD) affects millions, with a significant portion experiencing recurrent angina pectoris post-percutaneous coronary intervention (PCI).
- Understanding predictors of recurrent angina in patients without need for repeat revascularization is crucial for optimizing patient outcomes.
- This study addresses a gap in knowledge regarding factors influencing angina recurrence after seemingly successful PCI.
Purpose of the Study:
- To identify predictors of recurrent angina pectoris in patients with initially successful PCI.
- To investigate risk factors associated with elevated Thrombolysis in Myocardial Infarction (TIMI) frame count, indicative of coronary microcirculation dysfunction.
- To explore the role of patient characteristics and post-procedural treatment in angina recurrence.
Main Methods:
- Retrospective analysis of 3,837 patients with CAD undergoing successful PCI between January 2007 and June 2019.
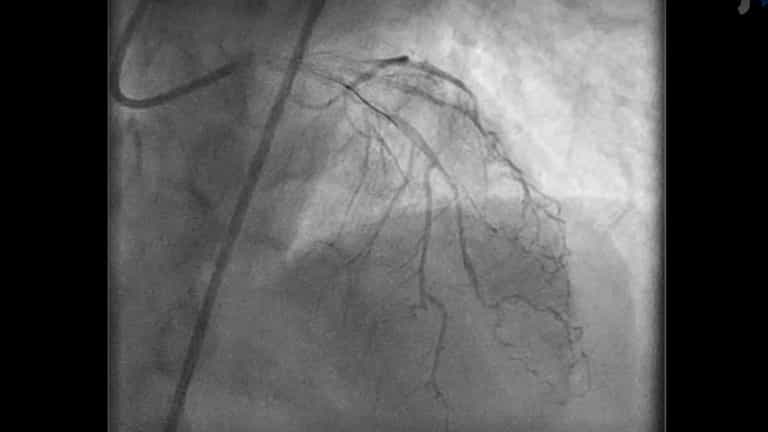
- Evaluation of coronary blood flow velocity using TIMI frame count in follow-up angiograms.
- Multivariate logistic and linear regression analyses to identify risk factors for recurrent angina and TIMI frame count.
Main Results:
- Over half (53.5%) of patients experienced recurrent angina pectoris.
- Key predictors identified for recurrent angina include female sex, older age, current smoking, LDL-C ≥1.8 mmol/L, and elevated TIMI frame count.
- Risk factors for elevated TIMI frame count were female sex, older age, diabetes, BMI, and lack of dual antiplatelet therapy post-procedure.
Conclusions:
- Female sex, older age, diabetes, and elevated BMI are linked to coronary microcirculation dysfunction and recurrent angina post-PCI.
- Current smoking and high LDL-C are significant risk factors for angina recurrence.
- Dual antiplatelet therapy demonstrates a protective effect, correlating negatively with elevated TIMI frame count and angina recurrence risk.
Background:
Approximately 20% to 30% of patients with coronary artery disease (CAD) develop recurrent angina pectoris following successful and complete coronary revascularization utilizing percutaneous coronary intervention (PCI). We aim to investigate predictors of recurrent angina pectoris in patients who have undergone successful coronary revascularization using PCI, but on repeat coronary angiography have no need for secondary revascularization.
Methods:
The study comprised 3,837 patients with CAD, who were enrolled from January 2007 to June 2019. They had undergone successful PCI; some of them redeveloped angina pectoris within one year after the procedure, but on repeat coronary angiography had no need for revascularization. Thrombolysis in myocardial infarction (TIMI) frame count was used to evaluate the velocity of coronary blood in the follow-up angiogram. Multivariate logistic regression was used to investigate risk factors for recurrent angina pectoris. Similarly, predictors of recurrent angina according to the TIMI frame count were assessed using multivariate linear regression.
Results:
In this retrospective study, 53.5% of patients experienced recurrent angina pectoris. By multivariate logistic regression, the following characteristics were statistically identified as risk factors for recurrent angina pectoris: female sex, older age, current smoking, low-density lipoprotein cholesterol (LDL-C) ≥1.8 mmol/L, and an elevated TIMI frame count (P for all <0.05). Similarly, using multivariate linear regression, the statistical risk factors for TIMI frame count included: female sex, older age, diabetes, body mass index (BMI), post-procedural treatment without the inclusion of dual antiplatelet therapy.
Conclusions:
Patient characteristics of female sex, older age, diabetes, and elevated BMI are associated with an increased TIMI frame count, coronary microcirculation dysfunction, and recurrent angina pectoris after initially successful PCI. In addition, current smoking and LDL-C ≥1.8 mmol/L are risk factors for recurrent angina pectoris. In contrast, the treatment with dual antiplatelet therapy is negatively correlated with a higher TIMI frame count and the risk of recurrent angina pectoris.

Related Concept Videos
 01:27
Angina II: Classification
 01:29
Angina III: Clinical Manifestations and Assessment
 01:20
Angina V: Nursing Management
 01:26
Angina IV: Management
 01:30
Angina I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations