Related Experiment Video
Updated: Nov 19, 2025


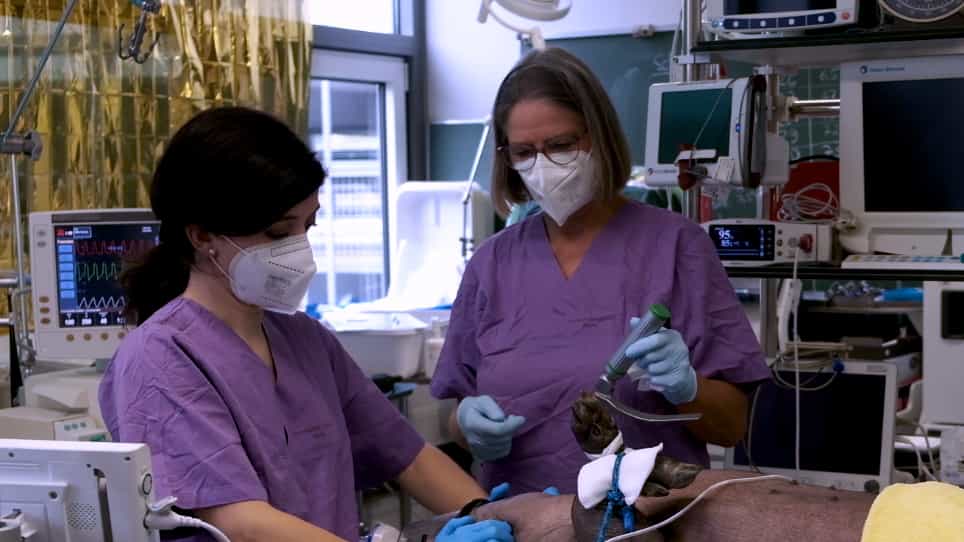
Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Airway Management for Initial PEG Insertion in the Pediatric Endoscopy Unit: A Retrospective Evaluation of 168
Jacquelin Peck1, Anh Thy H Nguyen2, Aditi Dey3
1Department of Anesthesiology, Mount Sinai Medical Center, Miami Beach, FL, USA.

Insights
Pediatric percutaneous endoscopic gastrostomy (PEG) tube placement using general endotracheal anesthesia (GETA) is associated with longer procedure times and hospital stays compared to anesthesia-directed deep sedation (ADDS) in higher-risk children.
Area of Science:
- Pediatric Gastroenterology
- Anesthesiology
- Endoscopic Procedures
Background:
- Percutaneous endoscopic gastrostomy (PEG) tube placement is a common pediatric endoscopic procedure.
- Patients undergoing PEG are at increased risk for airway complications due to underlying conditions.
Purpose of the Study:
- To compare patient characteristics and complications between general endotracheal anesthesia (GETA) and anesthesia-directed deep sedation with a natural airway (ADDS) for initial PEG insertion.
- To identify factors influencing the choice between GETA and ADDS in pediatric PEG procedures.
Main Methods:
- Retrospective cohort study of 168 pediatric patients (6 months to 18 years) undergoing initial PEG insertion.
- Anesthesia selection (GETA vs. ADDS) was determined by the attending anesthesiologist in consultation with the gastroenterologist.
Main Results:
- GETA patients were younger, had higher rates of severe American Society of Anesthesiologists (ASA) disease severity scores (ASA 4-5), and more cardiac comorbidities compared to ADDS patients.
- No significant differences were observed in airway support, 30-day readmission, fever, or pain medication between the two groups.
- GETA was associated with significantly increased length of hospital stay, room time, and anesthesia time after adjusting for relevant factors.
Conclusions:
- Younger and higher-risk pediatric patients are more likely to receive GETA for PEG tube placement.
- GETA for pediatric PEG procedures is linked to extended procedural and hospital stay durations compared to ADDS.
Purpose:
Percutaneous endoscopic gastrostomy (PEG) tube placements are commonly performed pediatric endoscopic procedures. Because of underlying disease, these patients are at increased risk for airway-related complications. This study compares patient characteristics and complications following initial PEG insertion with general endotracheal anesthesia (GETA) vs. anesthesia-directed deep sedation with a natural airway (ADDS).
Methods:
All patients 6 months to 18 years undergoing initial PEG insertion within the endoscopy suite were considered for inclusion in this retrospective cohort study. Selection of GETA vs. ADDS was made by the anesthesia attending after discussion with the gastroenterologist.
Results:
This study included 168 patients (GETA n=38, ADDS n=130). Cohorts had similar characteristics with respect to sex, race, and weight. Compared to ADDS, GETA patients were younger (1.5 years vs. 2.9 years, p=0.04), had higher rates of severe American Society of Anesthesiologists (ASA) disease severity scores (ASA 4-5) (21% vs. 3%, p<0.001), and higher rates of cardiac comorbidities (39.5% vs. 18.5%, p=0.02). Significant associations were not observed between GETA/ADDS status and airway support, 30-day readmission, fever, or pain medication in unadjusted or adjusted models. GETA patients had significantly increased length of stay (eβ=1.55, 95% confidence interval [CI]=1.11-2.18) after adjusting for ASA class, room time, anesthesia time, fever, and cardiac diagnosis. GETA patients also had increased room time (eβ=1.20, 95% CI=1.08-1.33) and anesthesia time (eβ=1.50, 95% CI=1.30-1.74) in adjusted models.
Conclusion:
Study results indicate that younger and higher risk patients are more likely to undergo GETA. Children selected for GETA experienced longer room times, anesthesia times, and hospital length of stay.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....