Related Experiment Video
Updated: Nov 19, 2025

Induction of Paralysis and Visual System Injury in Mice by T Cells Specific for Neuromyelitis Optica Autoantigen Aquaporin-4
Published on: August 21, 2017
Targeting the complement system in neuromyelitis optica spectrum disorder
Nithi Asavapanumas1, Lukmanee Tradtrantip2, Alan S Verkman2
1Chakri Naruebodindra Medical Institute, Faculty of Medicine Ramathibodi Hospital, Mahidol University, Bangkok, Thailand.

Introduction:
Neuromyelitis optica spectrum disorder (NMOSD) is characterized by central nervous system inflammation and demyelination. In AQP4-IgG seropositive NMOSD, circulating immunoglobulin G (IgG) autoantibodies against astrocyte water channel aquaporin-4 (AQP4) cause tissue injury. Compelling evidence supports a pathogenic role for complement activation following AQP4-IgG binding to AQP4. Clinical studies supported the approval of eculizumab, an inhibitor of C5 cleavage, in AQP4-IgG seropositive NMOSD.
Areas Covered:
This review covers in vitro, animal models, and human evidence for complement-dependent and complement-independent tissue injury in AQP4-IgG seropositive NMOSD. Complement targets are discussed, including complement proteins, regulators and anaphylatoxin receptors, and corresponding drug candidates.
Expert Opinion:
Though preclinical data support a central pathogenic role of complement activation in AQP4-IgG seropositive NMOSD, they do not resolve the relative contributions of complement-dependent vs. complement-independent disease mechanisms such as antibody-dependent cellular cytotoxicity, T cell effector mechanisms, and direct AQP4-IgG-induced cellular injury. The best evidence that complement-dependent mechanisms predominate in AQP4-IgG seropositive NMOSD comes from eculizumab clinical data. Various drug candidates targeting distinct complement effector mechanisms may offer improved safety and efficacy. However, notwithstanding the demonstrated efficacy of complement inhibition in AQP4-IgG seropositive NMOSD, the ultimate niche for complement inhibition is not clear given multiple drug options with alternative mechanisms of action.Abbreviations: AAV2, Adeno-associated virus 2; ADCC, antibody-dependent cellular cytotoxicity; ANCA, antineutrophilic cytoplasmic autoantibody; AQP4, aquaporin-4; AQP4-IgG, AQP4-immunoglobulin G; C1-INH, C1-esterase inhibitor; C3aR, C3a receptor; C4BP, C4 binding protein; C5aR, C5a receptor; CDC, complement-dependent cytotoxicity; CFHR1, complement factor H related 1; CNS, central nervous system; EAE, experimental autoimmune encephalomyelitis; EndoS, endoglycosidase S; FHL-1, factor-H-like protein 1; GFAP, glial fibrillary acidic protein; Iba-1, ionized calcium-binding adaptor protein-1; IgG, immunoglobulin G; IVIG, intravenous human immunoglobulin G; MAC, membrane attack complex; MBL, maltose-binding lectin; MBP, myelin basic protein; MOG, myelin oligodendrocyte glycoprotein; NK cell, natural killer cell; NMOSD, neuromyelitis optica spectrum disorder; OAP, orthogonal arrays of particles; PNH, paroxysmal nocturnal hemoglobinuria.
More Related Videos
 09:38
Determining Immune System Suppression versus CNS Protection for Pharmacological Interventions in Autoimmune Demyelination
Published on: September 12, 2016
 10:50
Visualizing Impairment of the Endothelial and Glial Barriers of the Neurovascular Unit during Experimental Autoimmune Encephalomyelitis In Vivo
Published on: March 26, 2019
Related Concept Videos
 01:27
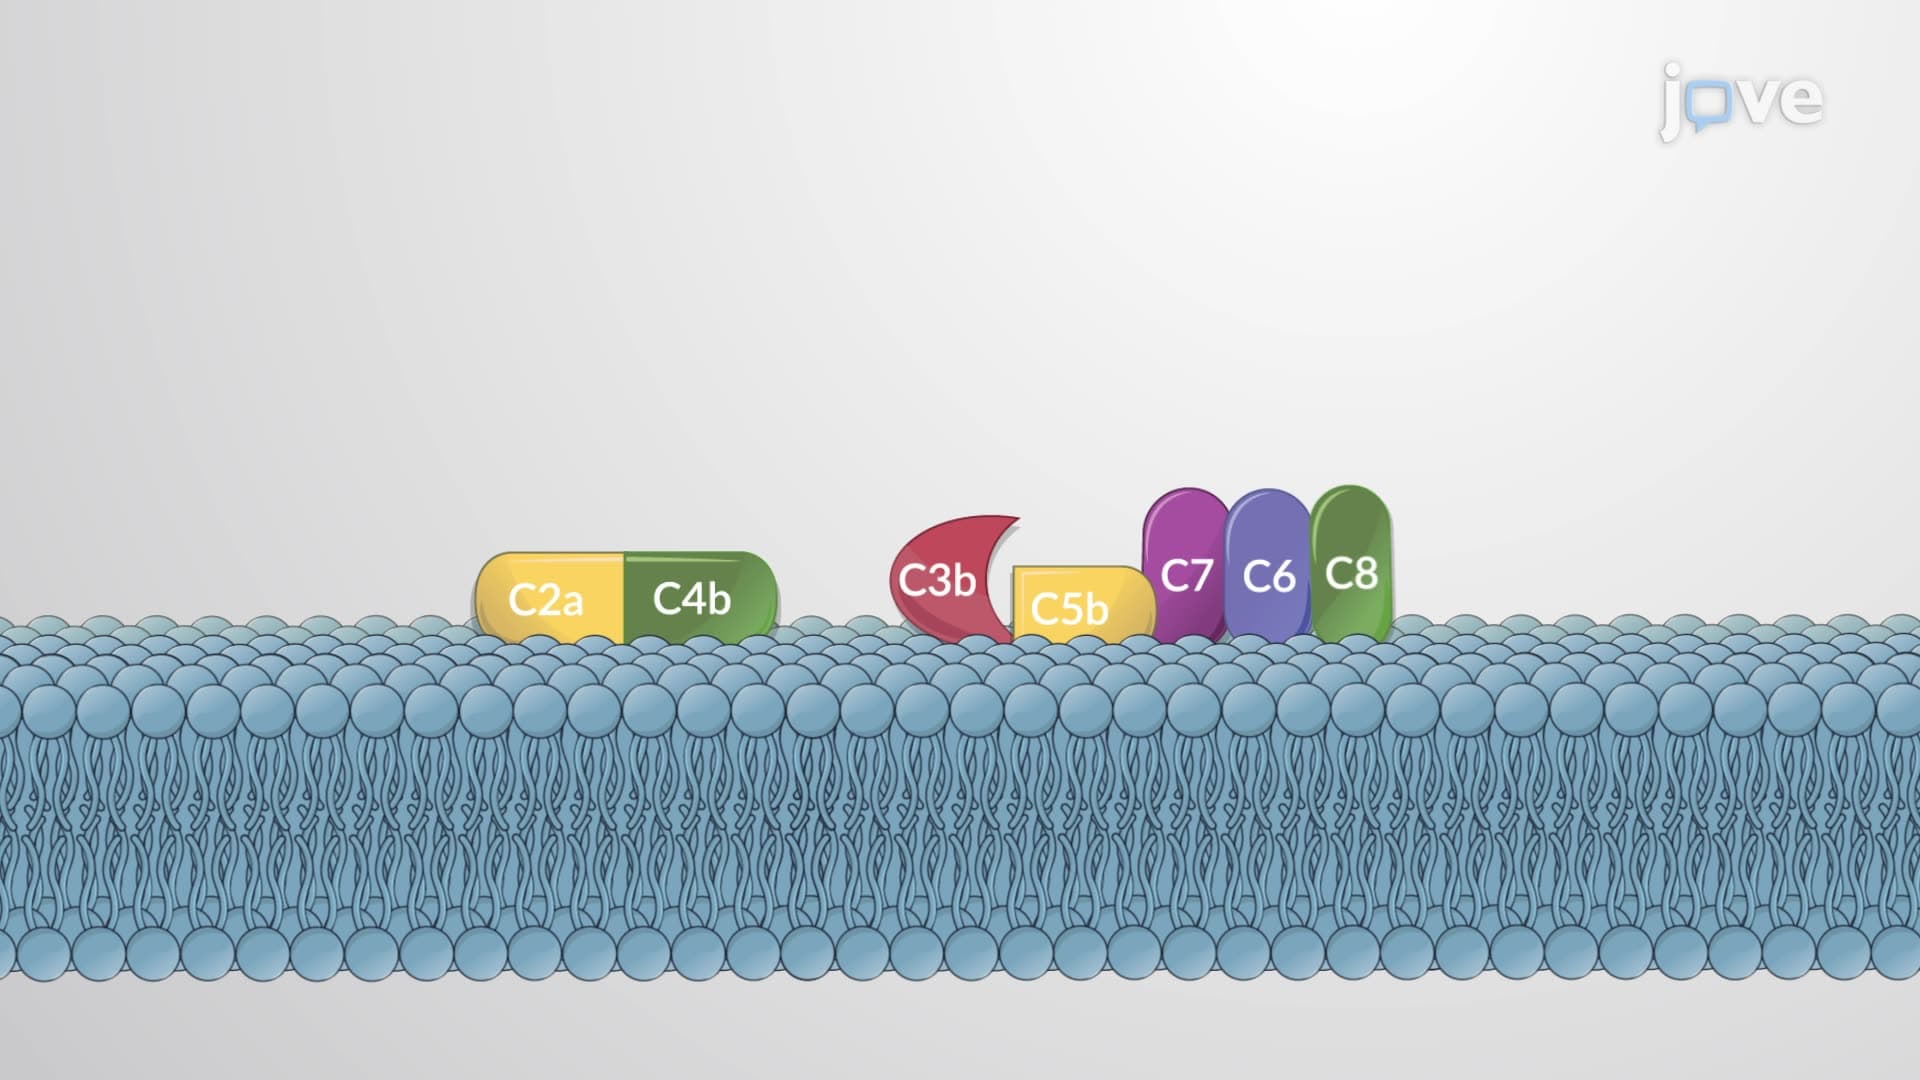
Complement System
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...